

“Idiopathic” peripheral neuropathy does not mean nothing can be found. It means the workup that was done did not find a cause. One chart review looked at 284 patients sent to a neuropathy center with an idiopathic label. After a thorough workup, 93 (32.7%) were still idiopathic. That means about two thirds turned out to have a cause that could be found [1].
That is the whole case for reopening the question. Peripheral nerve disorders affect about 2.4% of the world population and about 8% of older people [2]. The label given at the first visit often just describes how far the workup got.
Key points
- Idiopathic is a statement about the evaluation, not about the nerve.
- Neuropathy is a category, not a diagnosis. The work is finding which cause is active: metabolic, nutritional, autoimmune, toxic or structural.
- Poor sugar handling was the single most common cause found when patients first called idiopathic were checked again [1].
- Nerve conduction studies answer large-fiber questions. A normal study does not rule out small fiber damage.
- Newer testing keeps moving the line. Biallelic RFC1 repeat expansions, a genetic finding, showed up in 2.3% of one large US group with idiopathic neuropathy [3].
What does idiopathic neuropathy mean?
An idiopathic label usually reflects a specific gap. The wrong groups of causes were stressed, the timing of tests was off, or the pattern was never matched to the most useful test. None of those say whether a cause exists.
It is also not a statement about how serious it is. Neuropathy can keep getting worse while the cause goes unmeasured. That is why a stalled workup is worth restarting when symptoms are changing.
How do doctors find the cause of idiopathic neuropathy?
Step one: identify the pattern and the fiber type
Peripheral neuropathy can involve small fibers, large fibers or both. Small fiber damage tends to cause burning pain and changes in temperature or feeling. Large fiber damage more often shows up as numbness, unsteadiness and loss of position sense.
Getting that right early decides which tests are worth running, because the two patterns are answered by different tools.
Step two: connect the pattern to a driver category
A cause is an explanation, in how the body works, for what is going wrong. In practice the work is sorting through overlapping groups. These are metabolic (including poor sugar handling short of diabetes), nutrition and digestion, toxic and environmental, and autoimmune, infectious or structural.
The published recheck data support that focus. Among the 284 patients, poor sugar handling accounted for 72 (25.3%), including 26 with diabetes and 46 with prediabetes. Chronic inflammatory demyelinating polyneuropathy accounted for 57 (20%) and monoclonal gammopathy for 20 (7%). Toxic exposures, Sjögren disease, celiac disease, vitamin B12 deficiency, amyloidosis, vasculitis and inherited causes made up the rest [1]. Those groups are unpacked in the hidden drivers of peripheral neuropathy.
Step three: use testing to answer a question, not to assign a label
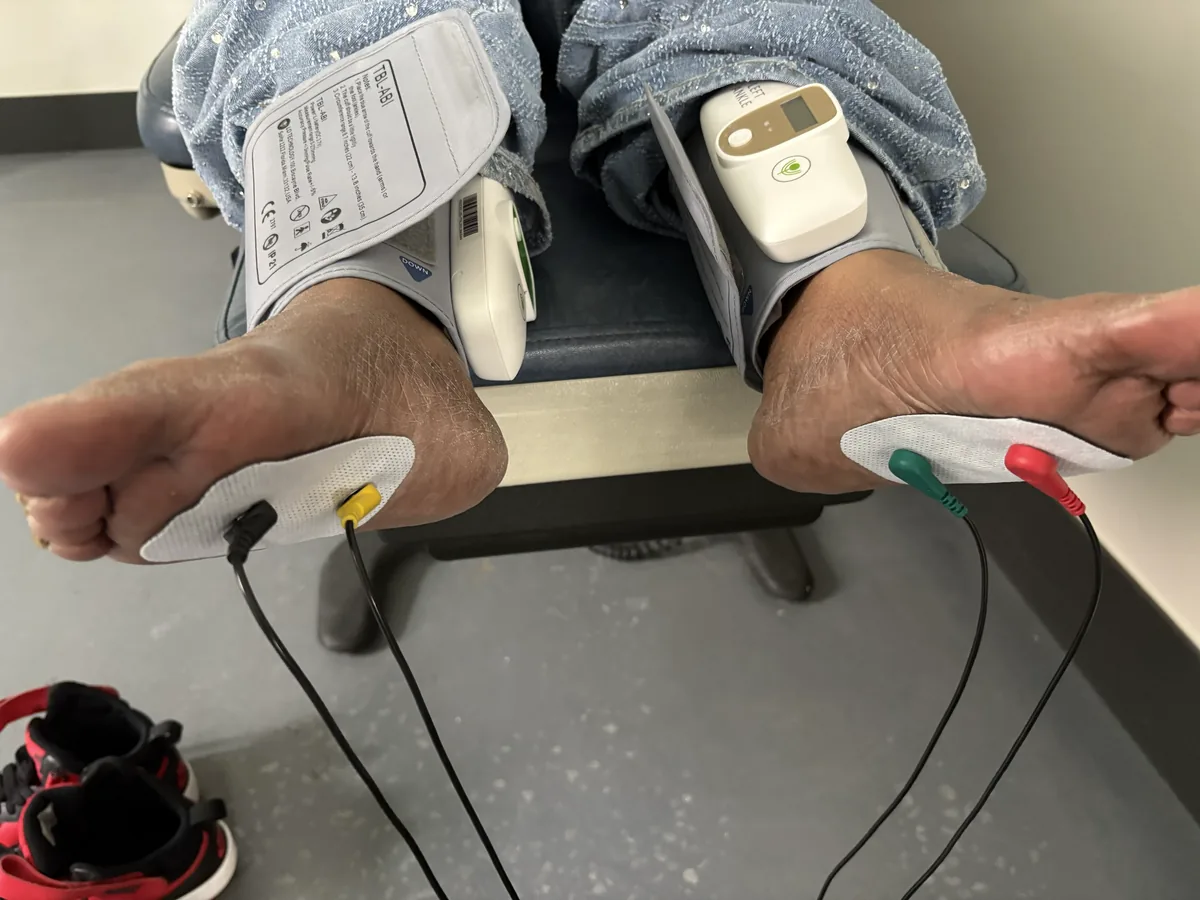
We do electrodiagnostic testing (EMG/NCS) on site. It is the right tool for large-fiber questions and for pinpointing a problem. It is a poor tool for confirming small fiber neuropathy, where studies can be normal.
When unsteadiness is part of the picture, we use videonystagmography (VNG) as a test of inner-ear balance. It separates an inner-ear cause from a nerve cause. It is not a treatment.

What hidden causes does an idiopathic neuropathy workup look for?
Metabolic drivers
Sugar handling is the most rewarding place to look, and the published data reflect that. A workup that stops at a normal fasting glucose can miss the poor-sugar-handling group entirely.
Nutritional and digestive drivers
Vitamin B12 deficiency was among the causes found in the recheck series [1]. Absorption matters as much as intake. That is why digestion is part of the nutrition review, not a separate topic.
Toxic and environmental drivers
Medicines, alcohol, work exposures and, less obviously, supplements belong in the history. Too much vitamin B6 is one example of a supplement that can injure nerves instead of protecting them.
Autoimmune and structural drivers
Immune-driven neuropathies made up more than a quarter of the causes found in that series [1]. These include chronic inflammatory demyelinating polyneuropathy and neuropathies tied to monoclonal gammopathy. Worsening, weakness, a lopsided pattern or whole-body symptoms are reasons to widen the workup sooner.
Genetic drivers that were invisible until recently
What testing can find keeps changing what “idiopathic” covers. A US study looked at 788 patients with idiopathic peripheral neuropathy. Biallelic RFC1 AAGGG repeat expansions were found in 18 patients (2.3%), compared with 1 of 778 controls. The yield was highest, at 6.9%, in the group with purely sensory symptoms [3].
Turning findings into a plan
Once the main cause is found, the plan follows it instead of cycling through options. Correcting a nutrient shortage, treating sugar handling and removing a toxic exposure are all cause-level work.
In-clinic therapies sit alongside that, not in place of it. We offer class 4 photobiomodulation, class 3B cold laser and whole-body infrared. Orthobiologic injections (PRP and BMAC) are offered in selected situations.
Qutenza (capsaicin 8% patch) is FDA-approved in adults for neuropathic pain from postherpetic neuralgia and from diabetic peripheral neuropathy of the feet. It is applied in clinic by a clinician and repeated no more often than every three months.
None of this is a promise of nerve regeneration or reversal. It is a plan matched to what the workup found.
Kidney function is one of the causes a full workup checks. See chronic kidney disease and uremic neuropathy.
Frequently asked questions
Does “idiopathic” mean nothing more can be found?
No. It means the workup that was done did not find a cause. One chart review looked at 284 patients sent to a neuropathy center with an idiopathic label. After a thorough workup, about two thirds were found to have a cause. See small fiber neuropathy symptoms and testing.
Is an EMG and nerve conduction study enough on its own?
It is the right test for large-fiber damage. But nerve conduction studies can be normal when the problem is limited to small fibers. When the symptom pattern points that way, the workup has to go past EMG/NCS instead of stopping at a normal result. We do EMG/NCS on site; see our services and on-site testing.
Which causes are found most often once someone is re-evaluated?
In that same 284-patient review, poor sugar handling was the most common cause. Next came chronic inflammatory demyelinating polyneuropathy and monoclonal gammopathy. Nutrient shortages, including vitamin B12, were among the rest. See functional B12 deficiency and neuropathy.
Can a gut or dietary problem explain nerve symptoms?
It can, in two ways. Poor absorption can lead to nutrient shortages, and the immune system can attack the nerves. Whether it applies to you is an idea to test against your history and labs, not an assumption. See the gluten and neuropathy connection.
Is balance testing a treatment for neuropathy?
No. Videonystagmography (VNG) is a test of inner-ear balance. When someone is unsteady, it helps separate an inner-ear cause from a nerve cause. It does not treat anything. See VNG balance testing.
What is the best treatment for idiopathic neuropathy?
The best treatment is the one aimed at the cause the workup finds. That can mean correcting a nutrient shortage, treating sugar handling, or removing a toxic exposure. In-clinic therapies such as class 4 photobiomodulation, class 3B cold laser, and whole-body infrared sit alongside that work, not in place of it. Qutenza is FDA-approved in adults for nerve pain that lingers after shingles (postherpetic neuralgia) and for diabetic neuropathy of the feet.
Can idiopathic neuropathy be reversed?
No honest clinic promises nerve regeneration or reversal, and Regenerve does not. What matters is that neuropathy can keep getting worse while its cause goes unmeasured. In one review of 284 patients labeled idiopathic, about two thirds turned out to have a cause the workup found. Finding yours gives you something specific to correct. That is the best way to protect the nerves you still have.
What vitamin will repair nerve damage?
No single vitamin repairs nerve damage. Vitamin B12 deficiency is one of the causes found when patients labeled idiopathic are checked again. Absorption matters as much as how much you take in. More is not always better: too much vitamin B6 from supplements can injure nerves instead of protecting them. Bring every supplement you take to your visit so it can be checked as a possible cause.
Next step
If you were told your neuropathy is idiopathic, the next step is a structured look at which cause is doing the most damage right now. Five questions start that map.
Sources
- Farhad K, Traub R, Ruzhansky KM, Brannagan TH 3rd. Causes of neuropathy in patients referred as “idiopathic neuropathy.” Muscle & Nerve. 2016;53(6):856-861. doi:10.1002/mus.24969. https://pubmed.ncbi.nlm.nih.gov/26561790/
- Hammi C, Yeung B. Neuropathy. StatPearls. Treasure Island (FL): StatPearls Publishing; last updated October 15, 2022. https://www.ncbi.nlm.nih.gov/books/NBK542220/
- Tang Z, Ovunc SS, Iwase R, et al. Homozygous RFC1 AAGGG repeat expansions are common in idiopathic peripheral neuropathy. Annals of Neurology. 2026;100(1):95-108. doi:10.1002/ana.78226. https://pubmed.ncbi.nlm.nih.gov/41964406/