
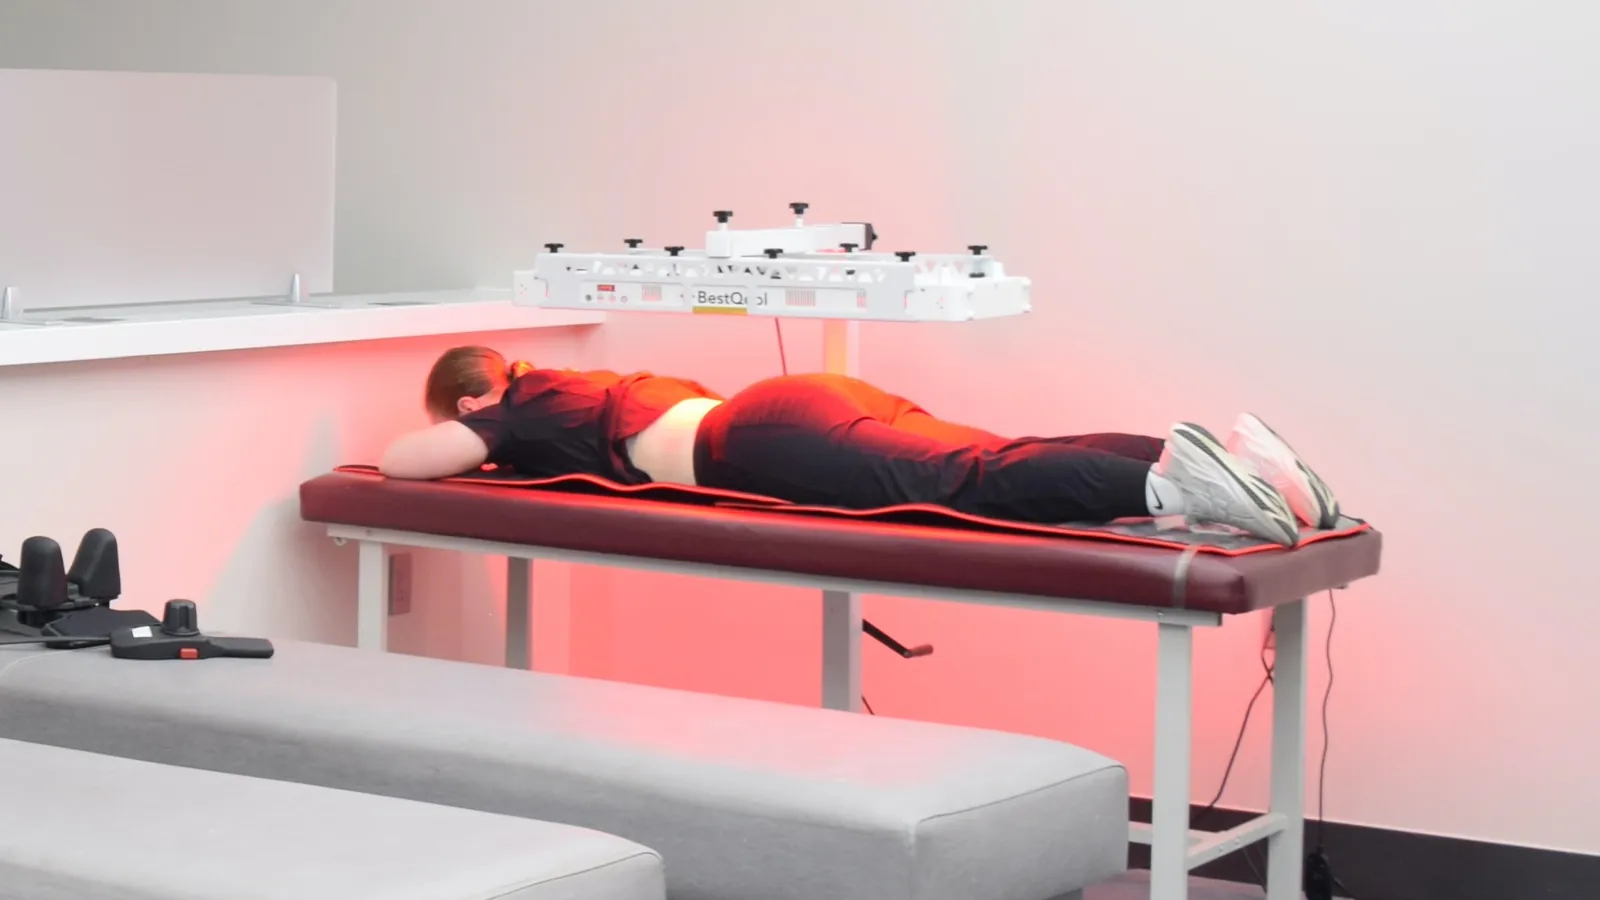
Whole-body infrared delivers infrared light and radiant heat to the entire body, not to one limb or one foot. At Regenerve it is supportive care. It sits inside a plan built around the specific driver of your neuropathy — metabolic, nutritional, autoimmune, toxic or structural. It is never a treatment given on its own.
Two things are true at once, and this page holds both. Medicare does not cover infrared therapy devices for peripheral sensory neuropathy, so you pay for a course out of pocket.2 And the randomized evidence behind that determination studied a different delivery method. It used narrowly selected patients, for a few weeks at a time. Neither fact settles what infrared can do for one specific person. This page explains why.
Does Medicare cover infrared therapy for neuropathy?
Effective October 24, 2006, the Centers for Medicare & Medicaid Services made a ruling on infrared therapy devices and related accessories. It found them not reasonable and necessary under section 1862(a)(1)(A) of the Social Security Act. Infrared and near-infrared light and heat are not covered anywhere in the country for diabetic and non-diabetic peripheral sensory neuropathy. That includes monochromatic infrared energy. The same goes for wounds and ulcers of the skin and the tissue under it (subcutaneous tissues). It also goes for symptoms such as pain from those conditions. The policy is on record as national coverage determination 270.6. It was implemented January 16, 2007.2
Know this before you start anything, because it decides how the service is paid for. Patients sign an advance beneficiary notice for non-covered services. Then they pay out of pocket. Anyone who offers you infrared for neuropathy and implies it will be billed to Medicare is either mistaken or misleading you.
A coverage determination is not a clinical finding about your nerves. It is a program’s decision about what it will buy. It was made under a legal standard, at a fixed point in time, on the evidence available then. That is a real and important decision. But it answers a different question from whether a therapy helps a particular person with a particular driver. The rest of this page deals with that clinical question.
What is the difference between infrared pads and whole-body infrared?
The word covers a wide band, and the difference is not cosmetic. It decides which studies apply to what you are being offered.
Contact pad devices
These are rows of small infrared lights (diodes) set in flexible pads. The pads are strapped against the skin of the foot and lower leg. This is the device the 2006 coverage determination describes and regulates. It falls under the durable medical equipment benefit category.2 With very few exceptions, it is also what the randomized neuropathy studies tested. In this field the technique is usually called monochromatic infrared energy.
Whole-body radiant infrared
This is a cabin or enclosure that raises body temperature with radiant infrared. There is no pad. There is no fixed wavelength aimed at a target tissue. The dose is very different, and so is the amount of tissue it reaches. In regulatory terms, infrared lamps emit across roughly 700 to 50,000 nanometers and are meant to provide topical heating (heating at the skin).3
When you compare what is on offer, ask which of these two you are actually buying. A study of pads at 890 nanometers on the sole of a foot does not automatically describe a warm cabin, in either direction.
What do the infrared therapy trials for neuropathy show?
A 2017 systematic review and meta-analysis in the Brazilian Journal of Physical Therapy pooled six randomized controlled trials. They covered 594 feet in 304 patients with diabetic sensorimotor polyneuropathy (nerve damage from diabetes).4 It is the best single place to see this body of work. Its own rules set the limits of what it can tell you.
The review included randomized trials of light-emitting diodes in the 750 to 1300 nanometer range. By rule, it left out any trial that applied the treatment to a region other than the feet. It also left out any trial with fewer than three days of treatment.4 Every device in it was a pad set placed on the foot and lower leg, at 870 to 890 nanometers. Each delivered 1.30 to 1.95 joules per square centimeter per minute. Follow-up ran from one and a half to twelve weeks, with a median of four weeks.4
The pooled result
Across four trials and 402 feet, infrared did not increase the number of plantar regions (spots on the sole) that could feel the 5.07 monofilament, compared with control. The standardized mean difference was 0.22, 95% confidence interval −0.07 to 0.51.4 A subgroup with follow-up of two weeks or less did show a gain: standardized mean difference 0.41, 95% confidence interval 0.18 to 0.64. That gain was gone beyond two weeks: standardized mean difference −0.12, 95% confidence interval −0.50 to 0.26. The difference between those subgroups was itself statistically significant at p = 0.02.4
For pain, the review set aside one non-blinded trial. After that, pain fell less in the infrared groups than in the sham groups: mean difference 0.40 points, 95% confidence interval 0.30 to 0.68.4 The review’s authors offer a specific reading of that, and it is worth knowing. In a nerve that is losing fibers, restoring some feeling can restore the ability to feel pain. So falling pain scores in this disease are not always good news.4 Using the GRADE system, the authors rated the overall certainty of evidence as low for both outcomes. That means further studies are likely to change the estimate.4
The largest and longest of the trials
A 2008 double-blind, sham-controlled trial in Diabetes Care randomized 69 people with diabetes. Of those, 60 patients and 120 limbs completed it. Units were used at home for 40 minutes a day for 90 days. The investigators measured nerve conduction velocities and vibration perception threshold. They used four grades of Semmes-Weinstein monofilament. They used the Michigan Neuropathy Screening Instrument. They also used a 10 cm visual analog pain scale and a quality of life tool built for neuropathy. There were no significant differences between active and sham on any of them.5
The entry rule that matters here is spelled out in the published report. Entry required a vibration perception threshold between 20 and 45 volts.5 That is a severity band. People with milder loss below that band were not enrolled. Neither were people with the most profound loss above it. We could not obtain the full eligibility list from the publisher. So we do not describe any exclusions beyond the one the report states.
The trial where both groups improved
A 2005 randomized, double-blind, placebo-controlled study in Diabetes Care followed 39 people. All had diabetic peripheral neuropathy. They got 30 minutes of active or placebo infrared three times a week for four weeks. Then they had four weeks with no treatment. The number of sites that could feel the 5.07 monofilament rose significantly in both the active and the placebo groups. There were no significant differences between the groups at any measurement point.6
The Medicare review of this trial recorded the size of that placebo movement. Over the blinded phase it was about +0.37 sites in the active arm and +0.57 sites in the sham arm, roughly 39% and 40% above baseline.3 This is the single most useful thing in the whole literature. It is why a clinic showing you before-and-after numbers with no control group has shown you nothing. And it applies to glowing reports about any modality, not only this one.
The trial that separated symptoms from structure
A 2021 randomized sham-controlled study in Neurology India enrolled 38 people with type 2 diabetes and painful diabetic peripheral neuropathy. Of those, 30 completed it. Treatment was three times a week for 12 weeks. Intraepidermal nerve fiber density (the count of tiny nerve endings in the skin) was measured on a 3 mm skin punch biopsy at baseline and at 12 weeks. Mean age was 59.1 years. Mean diabetes duration was 12.9 years, and mean symptom duration was 3.9 months.7
Nerve fiber density did not increase with treatment. Pain did move. The median visual analog scale score fell 5.1 points with infrared against 3.0 points with sham, intergroup p = 0.01. Quality of life on the Norfolk instrument also differed, at p = 0.021. The authors concluded that infrared does not increase nerve fiber density over short-term use. But they found it does provide symptom benefit and improved quality of life.7
For a patient deciding what to expect, this is the most informative single trial. It is also the clearest example of a narrow population. Mean symptom duration was under four months. People with years of symptoms were not in it. Neither were people with type 1 diabetes, or people whose neuropathy is not diabetic at all.
The smallest of the randomized trials
A 2011 single-blinded randomized controlled trial in the Singapore Medical Journal studied 30 feet from 24 patients. They were randomized to 12 daily infrared or sham treatments. Current perception threshold was measured by neurometer at 2,000 Hz, 250 Hz and 5 Hz, and checked again at six weeks and three months. No significant difference was found between the infrared and sham feet.8 The published report does not state a full exclusion list that we could obtain.
The other side of the argument
A 2023 systematic review in Current Diabetes Reviews took a wider view of photobiomodulation (light therapy aimed at cells) in diabetic peripheral neuropathy. It covered eight studies in people with type 2 diabetes. It reported less nerve pain (neuropathic pain) and better nerve conduction velocity. It also reported lower plantar pressure distribution (pressure across the sole). Its authors concluded that photobiomodulation is an effective, non-invasive option in this condition.9
That conclusion is real, and it belongs on this page. So does its basis. The review deliberately included both randomized and non-randomized studies,9 and uncontrolled designs are exactly where the placebo movement described above does its damage. It is a narrative synthesis, not a pooled estimate. It is limited to type 2 diabetes. A reader has every right to weigh it. A reader has no right to be told it settles the question.
Two independent groups have registered protocols for new systematic reviews in this area. One was published in BMJ Open in 2022 and one in PLOS ONE in 2024. Both call for randomized trials, with pain as a primary outcome. Their secondary outcomes include nerve conduction, sensation, quality of life and adverse events.1,10 Protocols describe what a good answer would look like. They are not answers themselves. But two of them, registered fifteen years after a coverage determination, are a fair signal. Researchers consider the question open, not closed.
What the 2006 decision was actually based on
Coverage decisions are documents, and this one is public. Reading it is more useful than repeating its conclusion.
Before the analysis there was no national ruling on these devices. But local Medicare contractors for durable medical equipment already had the same non-coverage rules. In the peripheral neuropathy literature, the analysis found 14 studies. Of those, 11 had an infrared-only arm. Only three of those were placebo-controlled with a parallel group run at the same time. All three were double-blinded and used sham devices. They enrolled 18, 43 and 50 patients.3
The blinded treatment periods in those three trials were two weeks in one and four weeks in the other two. Between them they tested only two wavelengths, 890 and 905 nanometers. No investigator did dose-ranging (testing a range of doses) for energy density, dosing frequency or dosing length. None varied pulsatility or duty cycle. None checked whether any effect lasted long-term. None used hard clinical endpoints such as ulcer or amputation rates.3 The analysis stated that despite an exhaustive search it found no high-quality randomized phase III trials with hard clinical endpoints. It also stated that a major placebo effect ruled out confident reading of the many studies in which patients served as their own controls.3 It noted that two large trials were then in progress. They could not be reviewed because they were not yet complete or published.3
That is a defensible decision on that record. It is also a decision about three small, short, single-wavelength trials of a contact pad device.
What has changed since
Four of the six trials in the 2017 meta-analysis were published after the determination took effect.4 Trial lengths grew from four weeks to 90 days5 and to 12 weeks.7 Outcome measures widened from monofilament counts to nerve conduction velocity and quality of life.5 Then they widened to intraepidermal nerve fiber density on skin biopsy.7
The overall picture did not reverse. The pooled estimate for sensation is still null, with low certainty. The pain estimate does not favor infrared.4 The real additions on the other side are two. One is a symptom and quality of life signal without a structural change.7 The other is a narrative review reporting benefit from a mixed body of randomized and non-randomized studies.9
What has not changed
The coverage policy itself. The public record for national coverage determination 270.6 shows coding updates for ICD-10 in 2015 and 2017. The policy did not change. It states that the determination was last reviewed in November 2006.2 Anyone who claims Medicare recently shifted its view on infrared for neuropathy is describing something that is not in the record.
Three research gaps also remain exactly where they were. There is still no phase III trial with hard clinical endpoints. There is still no dose-ranging study (one that tests a range of doses). No study has set what energy density, session length or course length would even be the right thing to test. And there is still no randomized trial of whole-body delivery in peripheral neuropathy at all — the pooled review excluded use on any region other than the feet, under its own eligibility rules.4
That last point needs saying carefully, because it is easy to abuse in both directions. A lack of trials of whole-body infrared is not evidence that whole-body infrared works. It is also not what the null pad-device results measured. It is a gap. A gap is a reason for modest expectations and honest conversation. It is not a reason for confidence either way.
The patients these trials did not study
Randomized trials earn their authority by controlling variation. They control it by choosing who gets in. That choice shows in this literature wherever the reports state it.
- A severity band. The 90-day home-use trial required a vibration perception threshold between 20 and 45 volts.5 Milder and more profound loss were both outside it.
- A region rule. The 2017 meta-analysis left out any trial that applied the treatment outside the feet, and any trial shorter than three days.4
- An early-symptom population. The nerve fiber density trial enrolled people with a mean symptom duration of 3.9 months. Their mean diabetes duration was 12.9 years, and all had type 2 diabetes.7
- One form of diabetes. The 2023 light therapy review (photobiomodulation) was limited to type 2 diabetes.9
For several of these trials we could not obtain the full eligibility and exclusion list from the publisher. In those cases we have not guessed at exclusions. This page does not claim any rule a report does not state.
What we can verify is what the designs did not test. None of these trials studied infrared in someone whose insulin resistance was being actively treated. None studied someone whose B12 deficiency had just been corrected, whose autoimmune driver had been found, or whose toxic exposure had been removed. None enrolled a person carrying several drivers at once alongside a long medication list. And every one of them tested infrared alone against a sham, on a fixed schedule, for a few weeks.
So a null result has limits. It came from a selected population, for one modality used by itself, over a short period. It tells you this device, at these settings, in these people, over this interval, did not beat sham on these measures. It does not show what happens in the patients who were screened out. And it does not describe a therapy used as one part of a plan instead of as the plan. That is the ordinary gap between efficacy under trial conditions and effectiveness in practice.
It cuts both ways, and we say so. The same logic that stops a null trial from closing the question also stops it from being a license to assume benefit. Where nobody has measured, nobody knows.
Does infrared heat improve circulation to the nerves?
There is a real reason clinicians care about heat and blood flow. It is separate from the neuropathy trials above.
What the heat therapy evidence shows
A 2021 systematic review and meta-analysis in Experimental Physiology pooled 15 studies of heat therapy. They covered healthy people and patients. Exposures ran 30 to 90 minutes over 10 to 36 sessions. Compared with control, heat therapy cut mean arterial pressure (average blood pressure) by 5.86 mmHg. It cut systolic blood pressure by 3.94 mmHg and diastolic blood pressure by 3.88 mmHg. It improved brachial artery flow-mediated dilatation (how well the arm artery widens) by 1.95%. Resting heart rate was unchanged. Certainty was rated moderate for the blood pressure outcomes. It was rated low for mean arterial pressure and flow-mediated dilatation.11
Those are heart and blood vessel outcomes, from a body of work about heat therapy in general. Not one of them is a nerve measurement. They give a reasonable mechanistic reason to be interested in whole-body heat when neuropathy has a microvascular (small blood vessel) component. They are not evidence of nerve benefit. We do not present them that way, and neither should anyone else.
The vasa nervorum question
Peripheral nerves are fed by very small vessels, the vasa nervorum. The longest nerves in the body depend on the most fragile end of that supply. Oxygen delivery is a real bottleneck in metabolic neuropathy. That is why treatments that change local blood flow attract attention.
Warmth causes vasodilation (widening of blood vessels). That much is not in dispute. Whether raising whole-body temperature on a schedule produces a lasting change in nerve function is a different claim. It has not been shown in a randomized trial in this condition.
Metabolic stress
Infrared is sometimes described as modulating metabolic stress in nerve tissue. We have not found trial evidence testing that claim in people with peripheral neuropathy. So we do not make it. And we do not use it as a reason to delay the metabolic and nutritional work that does have evidence behind it.
Is infrared heat therapy safe if you have neuropathy?
This is not a theoretical concern and it is specific to heat.
Loss of feeling in diabetic peripheral neuropathy raises the risk of burns, injuries and foot ulceration (foot sores).12 The mechanism is simple. The warning system that tells you something is too hot is the same system the disease has damaged. In the infrared studies themselves, the Medicare review noted that two patients in one trial got surface burns (superficial burns) under the device pads.3
That is why heat-based therapy in neuropathy belongs under clinical supervision. Skin is inspected before and after sessions. Session settings are set by someone who has measured how much sensation you have lost. And there is a low bar for stopping. It is also why a home device bought online carries a different risk from a supervised session, when the person using it cannot feel a burn forming.
Where whole-body infrared sits in a plan at Regenerve
Regenerve is directed by Dr. Gurpreet Singh Padda, MD, MBA, MHP. Whole-body infrared is one of the modalities available here. Others are class 4 photobiomodulation, class 3B cold laser, and metabolic and nutritional care. Electrodiagnostic testing (EMG/NCS) is done on site. VNG is a diagnostic test of inner-ear balance function, used when unsteadiness is part of the picture. It is a test, not a treatment.
None of it is prescribed before the driver is mapped. Peripheral neuropathy is a category, not a diagnosis. The order of steps matters more than the equipment list — a point covered in the hidden drivers of peripheral neuropathy.
What we tell patients about infrared specifically
We tell them the coverage status, so there is no billing surprise. We tell them the trial evidence is for a pad device on the feet. It is null on sensation over the lengths of time studied. The one trial measuring nerve fiber density found no structural change, while reporting symptom and quality of life benefit. We tell them no randomized trial has studied the whole-body form at all. We describe what we expect it to add — comfort, warmth, tolerance for the activity and metabolic work that carry the plan. And we say plainly that we are not claiming it repairs nerves.
We set a review point before starting. We agree on what would count as a change, and we stop if nothing changes. We do not promise that nerve damage can be regenerated or reversed. We publish no success rate for any Regenerve protocol.
“My ethos is to treat all of my patients as I would my own family, with the goal of giving them back their quality of life.” — Dr. Gurpreet Singh Padda, MD, MBA, MHP
Questions worth asking before starting a course
- Is this a contact pad device at a stated wavelength and dose, or whole-body radiant heat? The published trials are about the first one.
- How was the driver of my neuropathy found before this was recommended, and what tests were used?
- What outcome will be measured, with what instrument, and at what interval?
- How is my reduced ability to feel heat being accounted for in the protocol, and who inspects my skin?
- Is this being offered as one part of a plan, or as the plan?
- What is the review point, and at what stage do we stop?
- Am I signing an advance beneficiary notice, and what will I owe?
Start with the Nerve Damage Score
The Nerve Damage Score is five questions, and it is free. It points to which driver to chase first. That is the only thing that makes any decision about infrared meaningful.
Regenerve, 4477 Woodson Rd #104, St. Louis, MO 63134. Call (314) 886-5739 or text (314) 886-5902, or email info@regenerve.com. We are minutes from St. Louis Lambert International Airport and see patients from across the St. Louis region, Missouri and Illinois, including Edwardsville, Glen Carbon, Collinsville, Troy and Maryville.
Infrared is one of several in-clinic options. How PRP and BMAC fit for symptom relief is set out in orthobiologic injections for peripheral neuropathy.
Frequently asked questions
Is whole-body infrared therapy proven to treat peripheral neuropathy?
Not in the sense of a proven treatment. The randomized trials in this area studied contact pad devices on the feet and lower legs. A 2017 meta-analysis of six of them found a short-term gain in monofilament sensation that did not last, on low-certainty evidence. No randomized trial has tested whole-body delivery in peripheral neuropathy. So for that specific form there is an evidence gap, not a negative finding. Since 2006, Medicare has not covered infrared therapy devices for peripheral sensory neuropathy. So you pay out of pocket. We use it as supportive care inside a driver-directed plan, never as the treatment. See what we actually provide on site.
Does infrared help if my neuropathy is diabetic?
Diabetic peripheral neuropathy is driven by metabolic and microvascular (small blood vessel) injury. So the work that changes its course is metabolic. One 12-week sham-controlled trial in painful diabetic neuropathy reported symptom and quality of life benefit. It found no increase in nerve fiber density. That is a fair picture of what to expect: infrared may make you more comfortable while the metabolic work does the structural job. It does not replace that work. See diabetic peripheral neuropathy treatment in St. Louis.
Will infrared help if my neuropathy comes from a B12 deficiency?
It will not correct the deficiency, and correcting the deficiency is the point. Heat and light do nothing about absorption, intake, or the medications that interfere with B12. Infrared can sit alongside that correction for comfort. It cannot replace it. See functional B12 deficiency and neuropathy.
What about gluten-related neuropathy?
Same answer, different mechanism. If an immune reaction to gluten is driving the nerve injury, the treatment that matters is dietary and immune-based, not heat. Also note that people with non-diabetic drivers were not enrolled in the infrared trials at all. So there is no trial evidence either way for this group. See the gluten and neuropathy connection.
My nerve conduction study was normal but my feet still burn. Would infrared help?
A normal conduction study with ongoing burning points toward small fiber involvement. Standard nerve conduction testing often misses that. The next step is a workup matched to that pattern, not another modality, because a modality chosen before the driver is found is a guess. See small fiber neuropathy symptoms and testing.
Can infrared therapy reverse nerve damage?
We do not claim it can. The one trial that measured nerve fiber density found no structural change, even though patients reported better symptoms and quality of life. We use whole-body infrared for comfort, warmth and tolerance for the activity and metabolic work that carry the plan. We do not promise that nerve damage can be regenerated or reversed.
Is it safe to use a home infrared device for neuropathy?
It carries a different risk from a supervised session. Neuropathy damages the same warning system that tells you something is too hot, so a burn can form without being felt. In one infrared trial, two patients got superficial burns under the device pads. Under supervision, skin is inspected before and after sessions and settings match how much sensation you have lost.
Is whole-body infrared the same as infrared pads or laser therapy?
No. Whole-body infrared is a cabin that raises body temperature with radiant heat. Contact pad devices strap infrared diodes against the foot and lower leg. Those pads are what most neuropathy trials studied. Class 4 photobiomodulation and class 3B cold laser are separate modalities offered at Regenerve. Ask which one you are being offered, because studies of one do not describe the others.
Sources
- Wang JY, Huang ZQ, Deng HP, Zhao L, Deng HY, Liu JP, Shen XY, Cheng K. Low level light therapy/photobiomodulation for diabetic peripheral neuropathy: protocol of a systematic review and meta-analysis. BMJ Open. 2022;12(9):e059476. pmc.ncbi.nlm.nih.gov
- Centers for Medicare & Medicaid Services. National Coverage Determination 270.6, Infrared Therapy Devices. Effective October 24, 2006; implemented January 16, 2007. Medicare Coverage Database. cms.gov
- Centers for Medicare & Medicaid Services. Decision Memorandum for Infrared Therapy Devices (CAG-00291N). Medicare Coverage Database. October 24, 2006. cms.gov
- Robinson CC, Klahr PDS, Stein C, Falavigna M, Sbruzzi G, Plentz RDM. Effects of monochromatic infrared phototherapy in patients with diabetic peripheral neuropathy: a systematic review and meta-analysis of randomized controlled trials. Brazilian Journal of Physical Therapy. 2017;21(4):233-243. pmc.ncbi.nlm.nih.gov
- Lavery LA, Murdoch DP, Williams J, Lavery DC. Does anodyne light therapy improve peripheral neuropathy in diabetes? A double-blind, sham-controlled, randomized trial to evaluate monochromatic infrared photoenergy. Diabetes Care. 2008;31(2):316-321. pubmed.ncbi.nlm.nih.gov
- Clifft JK, Kasser RJ, Newton TS, Bush AJ. The effect of monochromatic infrared energy on sensation in patients with diabetic peripheral neuropathy: a double-blind, placebo-controlled study. Diabetes Care. 2005;28(12):2896-2900. pubmed.ncbi.nlm.nih.gov
- Rastogi A, Uppula P, Saikia U, Bhansali A. Effect of monochromatic infrared energy on quality of life and intraepidermal nerve fiber density in painful diabetic neuropathy: a randomized, sham control study. Neurology India. 2021;69(5):1331-1337. pubmed.ncbi.nlm.nih.gov
- Nawfar SA, Yacob NB. Effects of monochromatic infrared energy therapy on diabetic feet with peripheral sensory neuropathy: a randomised controlled trial. Singapore Medical Journal. 2011;52(9):669-672. pubmed.ncbi.nlm.nih.gov
- Korada HY, Arora E, Maiya GA, Rao S, Hande M, Shetty S, Gundmi S, Anche P, Amravadi S. Effectiveness of photobiomodulation therapy on neuropathic pain, nerve conduction and plantar pressure distribution in diabetic peripheral neuropathy: a systematic review. Current Diabetes Reviews. 2023;19(9):e290422204244. pubmed.ncbi.nlm.nih.gov
- Fan X, Yan G, Cao J, Zhao Y, Wang Y, Wang X, Mi J. Effectiveness and safety of photobiomodulation therapy in diabetic peripheral neuropathy: protocol for a systematic review and meta-analysis. PLOS ONE. 2024;19(8):e0308537. pmc.ncbi.nlm.nih.gov
- Pizzey FK, Smith EC, Ruediger SL, Keating SE, Askew CD, Coombes JS, Bailey TG. The effect of heat therapy on blood pressure and peripheral vascular function: a systematic review and meta-analysis. Experimental Physiology. 2021;106(6):1317-1334. pubmed.ncbi.nlm.nih.gov
- Tesfaye S, Selvarajah D. Advances in the epidemiology, pathogenesis and management of diabetic peripheral neuropathy. Diabetes/Metabolism Research and Reviews. 2012;28 Suppl 1:8-14. pubmed.ncbi.nlm.nih.gov