

A second opinion on idiopathic neuropathy is worth getting when the label came from a workup that did not match your symptoms. Idiopathic means the tests done so far did not find the cause. It does not mean no cause exists. The second visit should not hand you a new name for the same problem. It should give you a clear answer. What was tested? What was not? What would change the plan?
That question has room to move. Peripheral neuropathy covers a broad range of clinical pathologies (disease processes) that can show up as peripheral nervous system dysfunction [1]. In a group that wide, an incomplete workup can plausibly stop short.
Key takeaways
- Idiopathic describes the state of the workup, not the state of your nerves.
- Bring the timeline, the labs, and the nerve test reports. A second opinion is only as good as the record it starts from.
- Ask which fiber type your symptoms fit. Small-fiber and large-fiber patterns are checked in different ways, so the answer matters.
- Ask what is still untested, what result would change the plan, and when the case will be looked at again.
- Metabolic, nutritional, autoimmune, toxic, and structural drivers can overlap. More than one can be active at once.
- A useful plan ranks the drivers. It does not just list symptoms.
What does idiopathic neuropathy mean?
When neuropathy is called idiopathic, the honest translation is simple. The tests used so far did not find a cause. It says nothing about the state of the nerve fibers. It says nothing about microcirculation (the tiny blood vessels) or metabolic signaling either.
Small fiber neuropathy is a good example. Up to half of small fiber neuropathy cases are idiopathic. Yet the clinical advice is still to search for an identifiable underlying cause amenable to treatment. Autonomic symptoms (problems with automatic body functions) occur in nearly half of patients with small fiber neuropathy. They can be as troublesome as the neuropathic pain itself [2].
Peripheral neuropathy is a category, and the driver decides the plan
Two people with the same numbness can have different causes behind it. That is why a good second opinion looks at the terrain around the nerve. It does not stop at the feeling you report.
It also means the plan can be concrete before the label changes. Address blood flow in the tiny vessels where it is impaired. Cut metabolic injury where it is relevant. Supply the raw materials (substrates) nerve repair depends on.
What should I bring to a neuropathy second opinion?
Arriving organized shortens the visit and makes it more useful. Gather the following before you go.
- A one-page symptom timeline: when it started, where it started, and what has changed since.
- Your past diagnoses, in the exact words used on the reports.
- All lab results. Include glucose metrics, B12-related testing, thyroid studies, and any metabolic or vitamin panels.
- All nerve test reports, including any EMG and nerve conduction studies.
- A full list of drugs and supplements. Add your chemotherapy history and alcohol history.
- Family history of diabetes, autoimmune disease, or neuropathy.
Note whether your symptoms include burning at night or loss of feeling. Note whether they are the same on both sides (symmetric). The pattern tells us where to search for the driver.
What should a second opinion for neuropathy check?
1. Confirm the symptom pattern and the fiber type involved
Some neuropathies mainly hit small fibers, some large fibers, and some both. Symptoms can be real and disabling even when standard nerve conduction studies do not explain them. Small-fiber patterns cause this most often.
Ask which fiber type your symptoms fit and how that was decided. Burning, tingling, numbness, and autonomic features each carry different weight in that call.
2. Review whether the testing matched the clinical features
Some patients have atypical clinical features. Examples are rapid symptom onset, severe neuromotor impairment, or asymmetrically abnormal sensation (one side worse than the other). For them, neurology consultation and specialized testing are indicated. That includes nerve conduction studies and intraepidermal nerve fiber density testing (a count of nerve fibers in a small skin sample) [1]. If you had any of those features, it is fair to ask if the workup reflected that.
3. Map metabolic, nutritional, autoimmune, toxic, and structural drivers
Neuropathy is rarely explained by blood sugar alone. More than one driver can be active at the same time. A real driver search looks at least at the following.
- Gluten-related nerve injury. A negative celiac test does not by itself rule it out.
- B12-related patterns. That includes functional deficiency, when a serum (blood) level looks fine.
- Chemotherapy exposure, and when it happened compared with when symptoms began.
- Alcohol-related nerve injury and the nutrient loss that comes with it.
- Heavy metals and other toxins you were exposed to.
- Autoimmune causes such as lupus or rheumatoid arthritis.
- Malabsorption (poor uptake of nutrients) after stomach or bowel surgery.
- Structural causes, like a pinched nerve, stacked on top of a whole-body process.
For how these are sorted out in practice, read about the hidden drivers of peripheral neuropathy.
How do I choose a doctor for a neuropathy second opinion?
Choose someone who can answer driver questions, not only symptom questions. The difference shows up in the first ten minutes.
Ask about on-site testing and how decisions get made
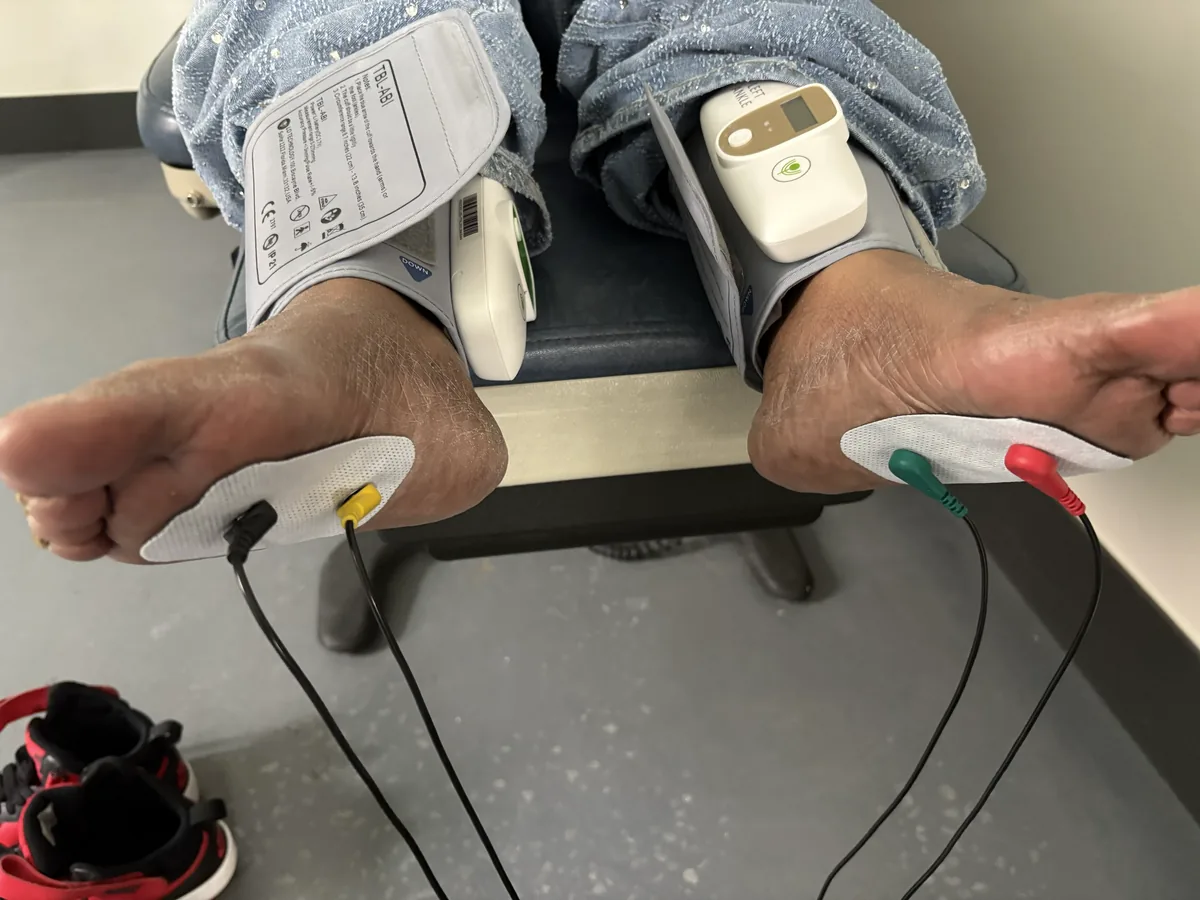
Regenerve does electrodiagnostic testing on site. That means EMG and nerve conduction studies. It sits alongside checks of the blood vessel and metabolic terrain around the nerve. Ask any clinic what they can do in-house. Ask what a given result would change.
For what to look for and what to ask, see choosing a neuropathy specialist in St. Louis.
Ask how they handle idiopathic cases specifically
The useful answer describes a process. What is checked when the standard workup finds nothing? How do they choose between electrodiagnostic testing and another route? When does the case get looked at again?
Say the answer is a prescription and a follow-up in six months, with no re-exam planned. That is worth knowing before you book.
Which neuropathy treatments will I hear about, and how should I judge them?
Neuropathy is a heavily marketed field. Your defense is to ask for a driver-first account of what is being treated and why.
Light-based and infrared therapies
Class 4 photobiomodulation, class 3B cold laser, and whole-body infrared are used at Regenerve. They are part of a physician-directed plan, alongside metabolic and nutritional care. Ask any clinic offering them where they fit next to the driver found by testing. They should not be sold as a standalone package.
Qutenza needs the correct indication and clear expectations
Qutenza, the capsaicin 8% patch, is FDA-approved in adults for neuropathic pain associated with postherpetic neuralgia and with diabetic peripheral neuropathy of the feet.
A clinician applies it in the clinic. It is never sent home with you. It is repeated no more often than every three months.
Orthobiologic injections at Regenerve
Regenerve offers platelet-rich plasma and bone marrow aspirate concentrate injections. Any clinic that sells them as established treatment for nerve damage is overstating what is known.
Frequently asked questions
Is idiopathic neuropathy the same as nothing can be done?
No. Idiopathic describes what the completed workup found. A second opinion can re-map the driver. This matters most when the symptom pattern suggests small-fiber involvement, which standard testing does not catch well. The plan can also work on the terrain around the nerve while the driver search goes on. For what those symptoms look like, see small fiber neuropathy symptoms and testing.
Can a negative celiac test rule out gluten-related nerve injury?
Not on its own. Gluten-related nerve injury can cause nerve symptoms in patients whose standard celiac testing is negative. So a single result should not close the question when the history points that way. Ask which tests were run and what they do and do not rule out. For the fuller picture, see the gluten and neuropathy connection.
My B12 was normal. Can B12 still be part of this?
It can. A serum B12 level in the normal range does not always reflect how B12 is working in the tissues. That is why a normal result alone is not a reason to drop the question. Ask whether functional markers were checked. For how that testing works, see why a normal B12 result can still miss neuropathy.
Diabetes was never confirmed as my cause. Is a second opinion still useful?
Yes, because metabolic injury can contribute without a formal diabetes diagnosis. Glucose handling sits on a spectrum, not a switch. A second opinion can show whether metabolic drivers belong in your plan at all. For how that work is done, see diabetic peripheral neuropathy treatment in St. Louis.
Can you reverse idiopathic neuropathy?
No one can honestly promise that. The label itself does not answer the question. Idiopathic only means the tests done so far did not find a cause. A second opinion looks for the driver behind the nerve damage: metabolic, nutritional, autoimmune, toxic, or structural. Once a driver is named, the plan can target it. That means better blood supply to the nerve, less metabolic injury, and supplying what nerve repair depends on.
What are the symptoms of idiopathic neuropathy in the feet?
They include burning, tingling, and numbness. Some people also have autonomic symptoms. In small fiber neuropathy, autonomic symptoms show up in nearly half of patients. They can be as troublesome as the pain itself. Before your visit, note whether you have burning at night or loss of feeling. Note whether both sides are affected the same way. That pattern tells the doctor where to look for a cause.
What is the newest treatment for neuropathy in your feet?
Newer is not the same as right for you. At Regenerve, options include class 4 photobiomodulation, class 3B cold laser, and whole-body infrared. They are used inside a physician-directed plan with metabolic and nutritional care. Qutenza, the capsaicin 8% patch, is FDA-approved in adults for nerve pain from diabetic neuropathy of the feet. A clinician applies it in the clinic, no more often than every three months. Ask how any treatment fits the cause your testing found.
Take the next step
If idiopathic ended your last conversation instead of starting the next one, a structured driver search is the way forward. Begin with the free five-question Nerve Damage Score. Regenerve is at 4477 Woodson Rd #104, St. Louis, MO 63134, minutes from St. Louis Lambert International Airport. We serve the St. Louis region, Missouri and Illinois. Call (314) 886-5739 or text (314) 886-5902, or email info@regenerve.com.
Sources
- Bodman MA, Dreyer MA, Varacallo MA. “Diabetic Peripheral Neuropathy.” StatPearls. StatPearls Publishing; last updated February 25, 2024. https://www.ncbi.nlm.nih.gov/books/NBK442009/ (referenced for: peripheral neuropathy encompasses a broad range of clinical pathologies presenting with peripheral nervous system dysfunction; neurology consultation and specialized testing including nerve conduction studies and intraepidermal nerve fiber density testing are indicated for atypical clinical features such as rapid symptom onset, severe neuromotor impairment, and asymmetrically abnormal sensation).
- Tavee JO. “Office approach to small fiber neuropathy.” Cleveland Clinic Journal of Medicine. 2018;85(10):801–812. https://www.ccjm.org/content/85/10/801 (referenced for: up to half of small fiber neuropathy cases are idiopathic and a search for a treatable underlying cause is still indicated; autonomic symptoms occur in nearly half of patients with small fiber neuropathy and can be as troublesome as neuropathic pain).
- Averitas Pharma Inc. “QUTENZA (capsaicin) 8% topical system — prescribing information.” U.S. National Library of Medicine, DailyMed; label revised July 2024. https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=3ffbbcb0-ad93-4f15-bb38-5da76a71c735 (referenced for: indicated in adults for neuropathic pain associated with postherpetic neuralgia and for neuropathic pain associated with diabetic peripheral neuropathy of the feet; only physicians or health care professionals are to administer it; may be repeated not more frequently than every three months).