
The early signs are sensory, and they start in the toes: burning at night, tingling, and numbness that spreads upward on both feet at once. Diabetic peripheral neuropathy occurs in up to 50% of patients with diabetes mellitus. It commonly shows up as distal symmetric polyneuropathy with a stocking-and-glove pattern, starting in the toes and moving up the leg.1 Spotting the pattern early matters, because the same paper links it to loss of protective feeling and a chain that leads to foot ulcers, wounds and infections.1
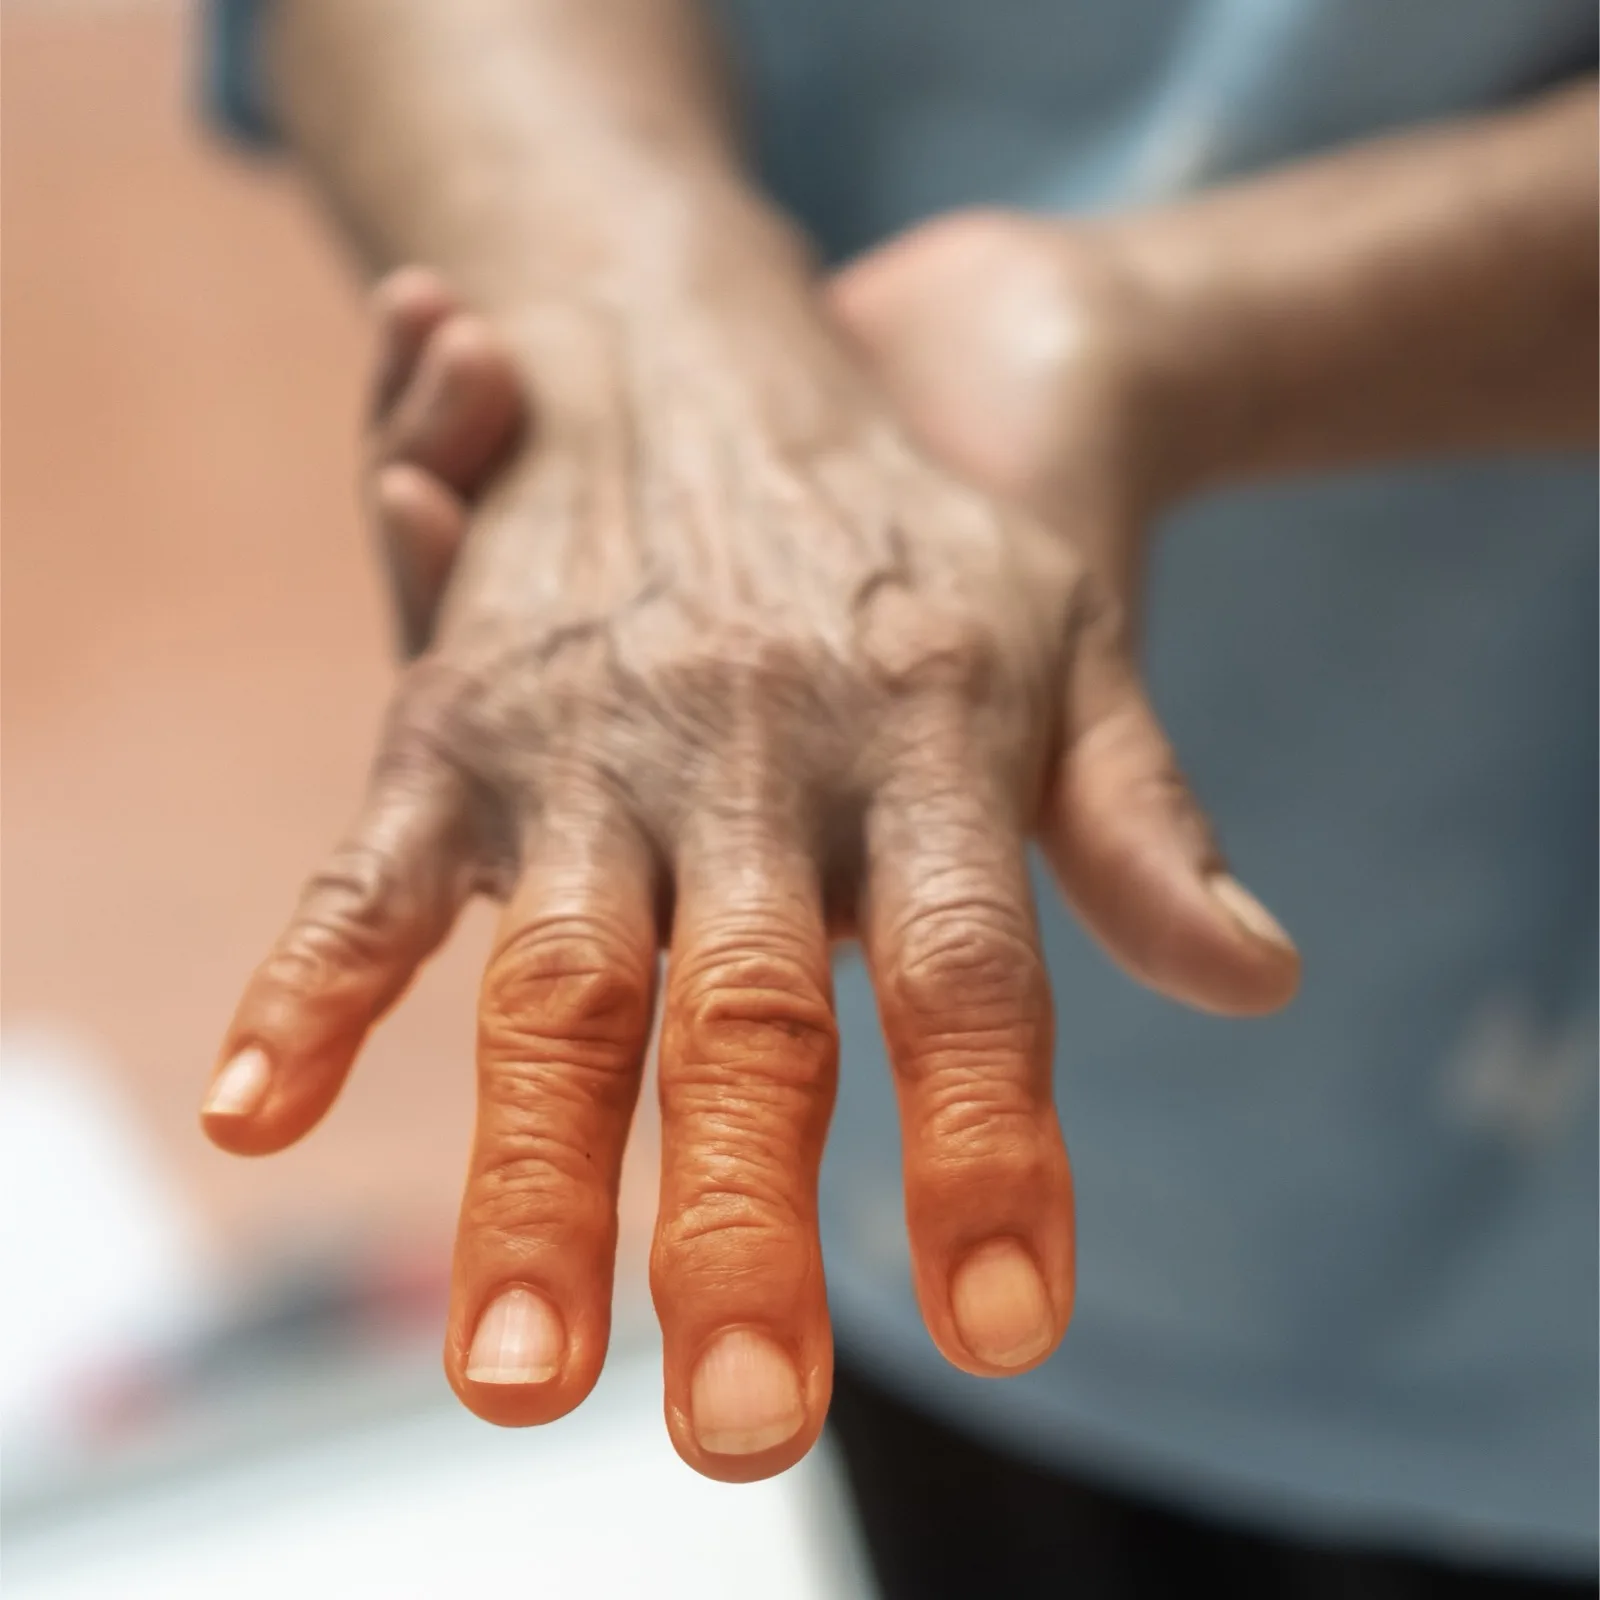
What does early diabetic neuropathy feel like?
These changes rarely feel like an emergency at first. People describe them as being in the socks, on the skin, or in the floor underfoot.
- Burning in the feet that is worse at night or after lying down
- Tingling or pins-and-needles in the toes or forefoot
- Numbness that starts small and spreads upward
- Brief electric or stabbing pains
- Unsteadiness on uneven ground or in the dark
The match on both sides is the key clue. A problem in one foot alone points somewhere else. The same change in both feet, worst at the toes, fits a process that hits the longest nerves first.
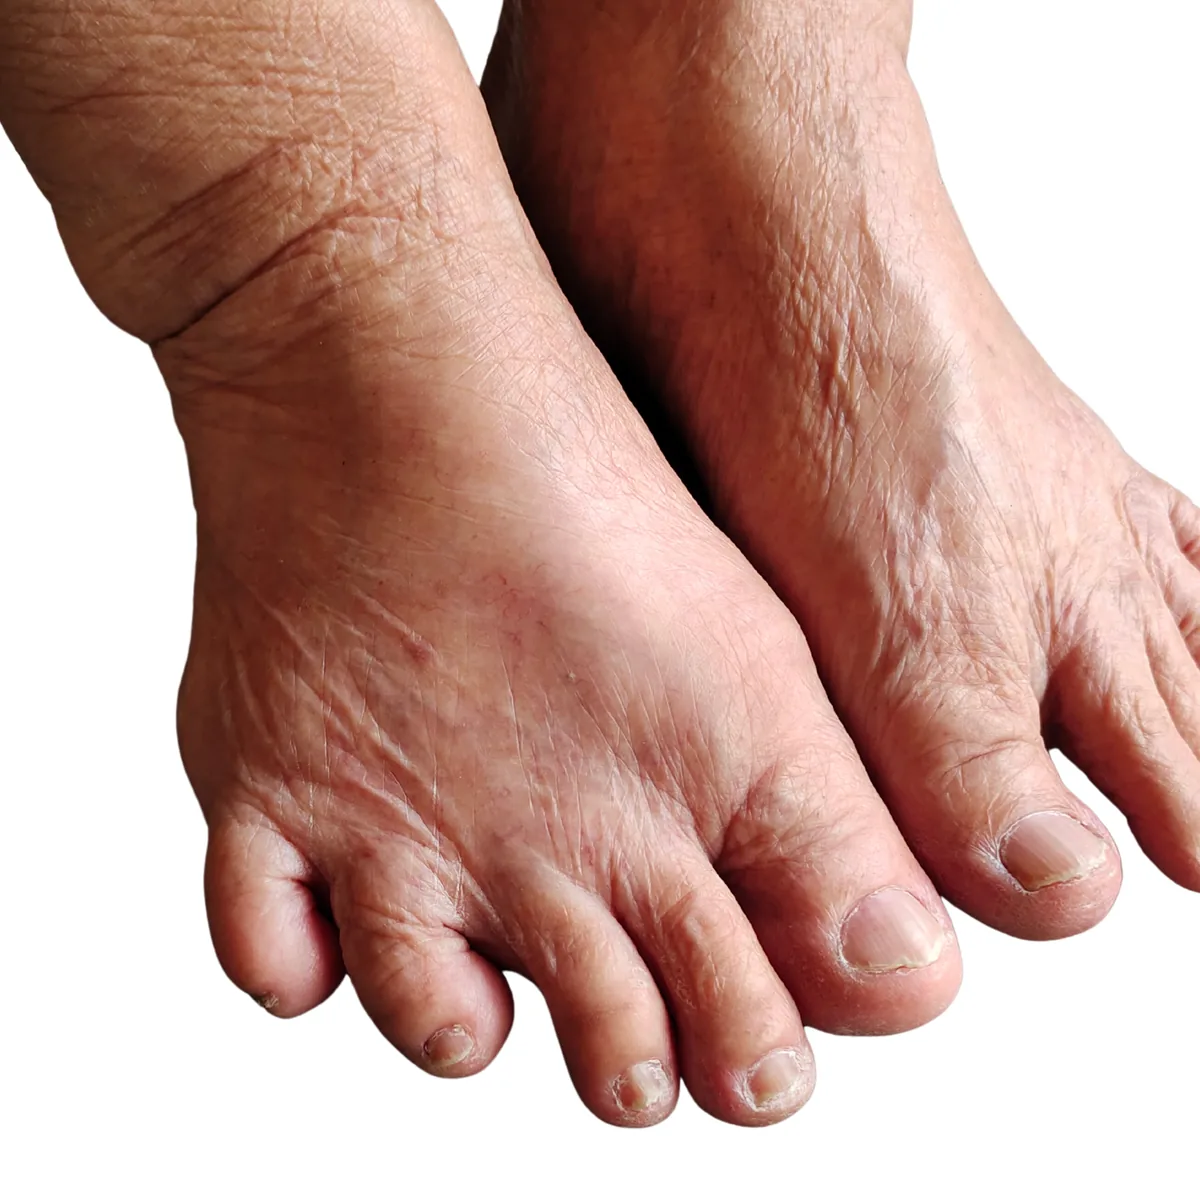
Why is numbness more dangerous than pain?
Pain gets attention. Numbness does not, and that is exactly the problem. American Family Physician notes that diabetic peripheral neuropathy may lead to a loss of protective feeling. That can set off a chain of foot ulcers, wounds, infections and tissue death (necrosis).1
Once protective feeling fades, a blister or a stone in the shoe no longer makes itself known. That is the point where daily foot checks stop being optional.

Can you have neuropathy with a normal A1C?
Fasting glucose and A1C describe blood sugar at a point in time. They do not directly measure the metabolic state around the nerve. A result inside the normal range does not by itself rule out early nerve damage.
In our clinic we look at insulin resistance and the wider metabolic picture, not A1C alone. The reasoning is in blood sugar and nerve damage, and why normal labs miss it.
When blood sugar stays high for a long time, glycation is one of the ways sugar damages nerve tissue over time. We explain it in how glycation damages nerves.
Can something besides diabetes cause the same foot symptoms?
Neuropathy is a category, not a diagnosis. A diabetes diagnosis does not rule out a second cause. American Family Physician directs physicians to address underlying risk factors, including vitamin B12 deficiency, alongside blood sugar control.1
Nutrition, autoimmune, toxic and structural causes all produce foot symptoms. Treating only the one you assumed is how a plan stalls. Finding which cause is doing the most damage is the first job of the workup.
How is diabetic neuropathy tested and treated at Regenerve?
We do electrodiagnostic testing (EMG/NCS) on site. We sort between metabolic, nutritional, autoimmune, toxic and structural causes before building a plan. When balance is involved, VNG is used as a test of inner-ear balance, not as a treatment.
Care options include physician-directed metabolic and nutritional care, class 4 photobiomodulation, class 3B cold laser and whole-body infrared. Orthobiologic injections (PRP and BMAC) are offered in selected situations. Qutenza (capsaicin 8% patch) is FDA-approved in adults only for neuropathic pain from postherpetic neuralgia and from diabetic peripheral neuropathy of the feet; it is applied in clinic by a clinician and repeated no more often than every three months.
We do not promise nerve regeneration, reversal or cure. We do not publish a success rate for our protocol. We are at 4477 Woodson Rd #104, St. Louis, MO 63134, and we see patients from the St. Louis region, Missouri and Illinois.
What to do this week
- Check both feet daily, soles included, using a mirror if you cannot see them.
- Write down when the burning is worst and whether it is spreading.
- Wear shoes that do not create pressure points, and check inside them before putting them on.
- Ask for a workup that looks past A1C, including B12 status.
- Get checked instead of waiting for the pain to make the decision for you.
Start with your Nerve Damage Score
If you see the pattern, do not wait for it to spread. The Nerve Damage Score is a free five-question screen. It helps find which cause to test for first.
If burning at night is your main symptom, burning feet at night: causes and evaluation walks through the other causes to rule out.
Frequently asked questions
What are the earliest signs of diabetic peripheral neuropathy?
Changes in feeling in the toes come first: burning at night, tingling, and numbness that spreads upward, the same on both sides. American Family Physician describes it as distal symmetric polyneuropathy with a stocking-and-glove pattern, starting in the toes and moving up the leg. See peripheral neuropathy of the feet symptoms.
My nerve testing was normal but my feet burn at night. What now?
Standard nerve conduction studies mostly test the large, coated nerve fibers. So a small-fiber problem can hide under a normal result. Burning, temperature changes and changes in sweating are the pattern worth raising. See small fiber neuropathy symptoms and testing.
Can I have nerve symptoms from something other than blood sugar?
Yes, and more than one cause can be present at the same time. Nutrition, autoimmune, toxic and structural causes all produce foot symptoms. That is why the workup looks past the diabetes label. See why a normal B12 result can still miss neuropathy.
Is numbness better than pain?
No. Loss of protective feeling is what lets an injury go unnoticed. American Family Physician links it to foot ulcers, wounds and infections. Numbness is a reason to start daily foot checks, not to relax. See exercises for peripheral neuropathy in the feet.
Can diabetic peripheral neuropathy be reversed?
We do not promise nerve regeneration, reversal or cure, and we do not publish a success rate for our protocol. What we do is find the causes behind your symptoms, whether metabolic, nutritional, autoimmune, toxic or structural, and build a plan around them. Catching the pattern early matters, because loss of protective feeling is what leads to foot ulcers, wounds and infections.
How do you test for diabetic neuropathy in the feet?
We do electrodiagnostic testing (EMG and nerve conduction studies) on site. The workup also looks past A1C to insulin resistance and the wider metabolic picture. It checks B12 status too, because a normal A1C does not by itself rule out early nerve damage. If balance is a problem, VNG tests inner-ear balance. It is a test, not a treatment.
Does vitamin B12 matter in diabetic neuropathy?
Yes. A diabetes diagnosis does not rule out a second cause. American Family Physician directs physicians to address vitamin B12 deficiency alongside blood sugar control. That is why we ask for a workup that includes B12 status. Treating only the cause you assumed is how a plan stalls. So the workup sorts out which cause is doing the most damage.
What is the treatment for diabetic neuropathy in the feet?
At Regenerve, care options include physician-directed metabolic and nutritional care, class 4 photobiomodulation, class 3B cold laser and whole-body infrared. PRP and BMAC injections are offered in selected situations. Qutenza, a capsaicin 8% patch, is FDA-approved in adults for diabetic nerve pain in the feet; a clinician applies it in the clinic, no more often than every three months.
Sources
- Bragg S, Marrison ST, Haley S. “Diabetic Peripheral Neuropathy: Prevention and Treatment.” American Family Physician. 2024;109(3):226. https://www.aafp.org/afp/2024/0300/diabetic-peripheral-neuropathy
- Hicks CW, Selvin E. “Epidemiology of Peripheral Neuropathy and Lower Extremity Disease in Diabetes.” Current Diabetes Reports. 2019;19(10):86. https://pmc.ncbi.nlm.nih.gov/articles/PMC6755905/