
Peripheral neuropathy symptoms in the feet usually begin in the toes of both feet as burning, tingling or numbness. They are often worse at night, and they spread upward over time. Later come unsteadiness in the dark, weakness, lost temperature sense and injuries you do not feel.
Peripheral neuropathy in the feet does not announce itself. It shows up as something easy to explain away. Socks feel bunched when they are not. The floor feels slightly wrong underfoot. Toes burn at night and are fine by morning. By the time most people describe it to a doctor, the process has usually been running for years.
The symptoms are worth reading carefully. Their pattern tells you a great deal about what is damaging the nerve and how far it has gone.
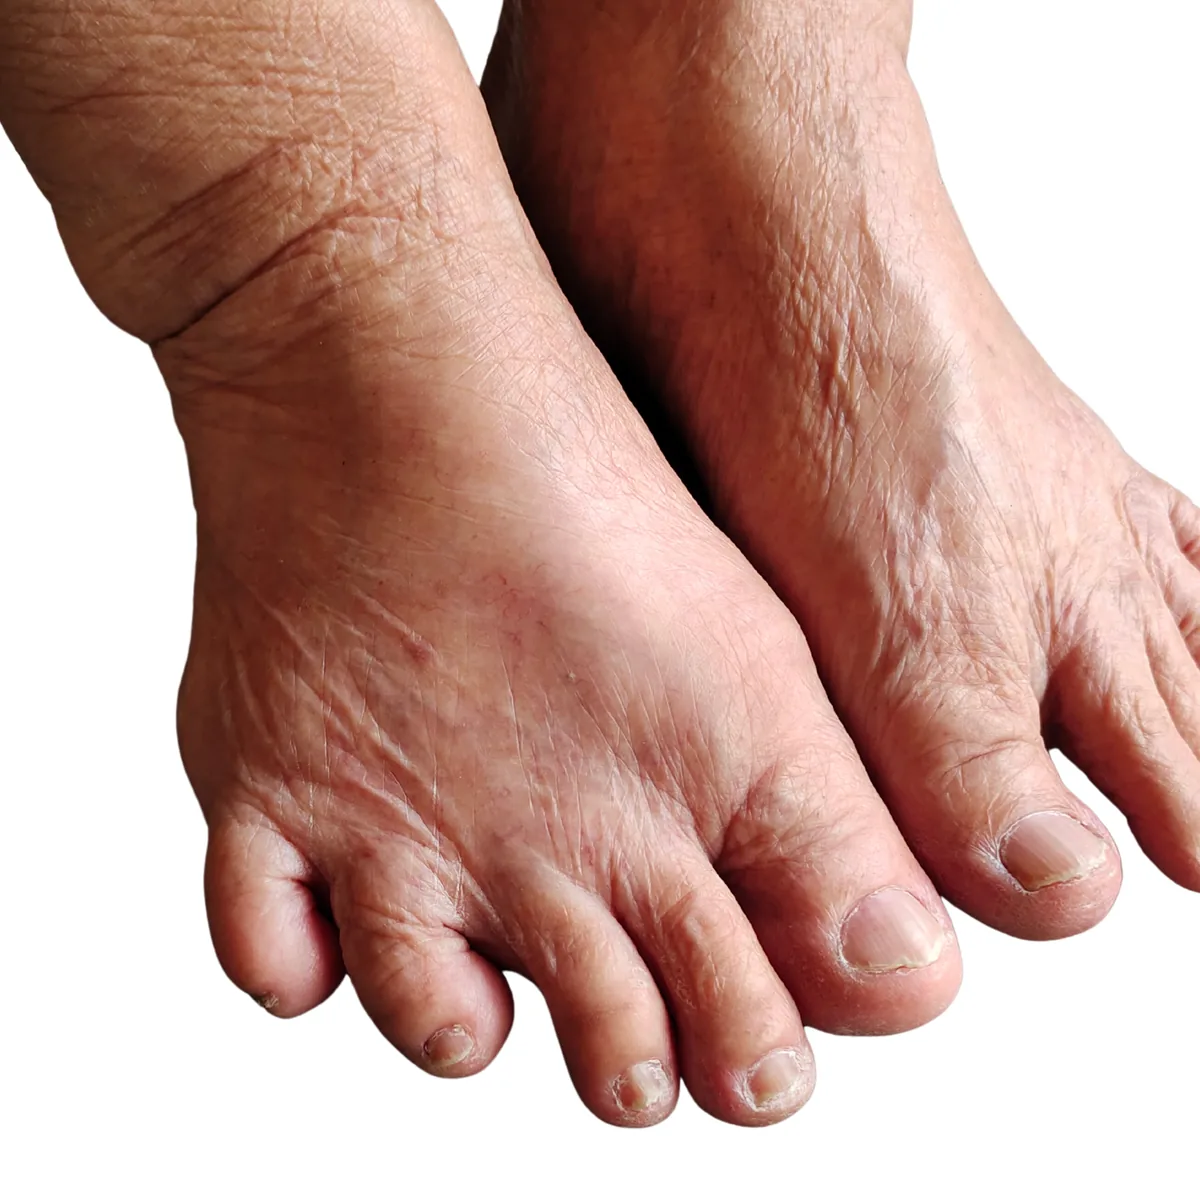
Does neuropathy start in the toes and spread upward?
Metabolic neuropathy is length-dependent. It hits the longest nerve fibers first. So it starts at the toes and spreads upward evenly on both sides. It only reaches the fingertips once it has climbed to about knee height. Clinicians call this a stocking-glove distribution. It is the signature of a body-wide process that affects every nerve at once, not an injury to one nerve.1
Two features of that pattern carry real diagnostic weight. It is symmetrical: both feet, roughly equally. And it ascends. Symptoms in one foot only point somewhere else. So do symptoms that skip from a foot to a hand without covering the ground between. They often point toward nerve compression or a double-crush pattern.
What does neuropathy pain in the feet feel like?
Damaged sensory nerves misfire. They send signals with no real trigger behind them. Patients describe these in strikingly similar words:
- Burning, often described as the feet being on fire. It is often worst at night, when nothing else competes for attention
- Tingling or pins and needles that does not go away when you move the foot
- Electric or shooting pain arriving in bursts, sometimes without any trigger
- Allodynia: pain from something that should not hurt. The classic example is the weight of a bedsheet on the toes
- Deep aching in the arches or across the ball of the foot
- Crawling, itching or wetness where nothing is touching the skin
These are the symptoms that bring people in. They are also the ones most likely to be treated on their own. Relief matters. But a burning foot is a report on the nerve’s condition. Turning down the volume does not change what caused it.
What happens when your feet go numb?
The quieter half of the picture is loss. It is the more dangerous half:
- Numbness, or a sense that the feet are wrapped in a layer of something
- Reduced ability to feel temperature. This is why burns from hot water and heating pads are a real risk
- Loss of position sense, so you no longer know where your feet are without looking at them
- Unsteadiness, especially in the dark or on uneven ground. This is a very common first complaint
- Weakness in the foot and ankle. It sometimes shows up as tripping on curbs or scuffing a toe
- Not noticing injury: the blister, the stone in the shoe, the crack in the heel
That last item is the one that raises the stakes. When protective feeling is gone, the foot stops reporting damage. A minor injury can then get worse without ever hurting. A 10-gram monofilament test finds loss of protective sensation. Anyone who has that loss needs daily visual foot checks and well-fitted shoes as a standing routine.2
Small fibers and large fibers give different symptoms
Sensory nerves come in two sizes, and they fail in different ways. Small unmyelinated and thinly myelinated fibers have little or no insulating coat. They carry pain, temperature and autonomic (automatic body function) signals. Large myelinated fibers carry vibration, light touch and position sense.
Small-fiber symptoms come first in most metabolic neuropathy. They include burning, pinprick pain, and changed temperature sense. They also include autonomic changes. The feet may stop sweating. The skin may turn dry and shiny, or change color. Large-fiber symptoms come later. They include numbness, lost vibration sense, poor balance, and reduced or absent ankle reflexes.3
This difference has a practical result that catches a lot of patients. Standard nerve conduction studies measure large fibers. Your neuropathy may still be mostly small-fiber. Then those studies can come back normal while your feet burn every night. A normal result then gets misread as “nothing is wrong.” It means the test looked at the wrong fibers. We cover this in detail in small fiber peripheral neuropathy symptoms and testing.
Autonomic symptoms people rarely connect to their feet
The same small fibers that carry pain also control sweating, blood vessel tone and internal organ function. When they are damaged, symptoms show up well beyond the feet. You may get lightheaded when you stand. Sweating may change for no clear reason. You may feel full early after meals. You may have constipation or diarrhea, bladder changes, or erectile dysfunction. These are often reported to different specialists as separate problems. They frequently belong to one process.
What the symptoms are usually telling you
Peripheral neuropathy is not rare. It is not limited to people with diabetes. One national sample looked at U.S. adults aged 40 and older. Of them, 13.5% had peripheral neuropathy. That was 27.0% of those with diabetes, and 11.6% of those without. People were followed for a median of 13 years. In both groups, neuropathy was independently associated with mortality (death).4 See diabetic peripheral neuropathy treatment in St. Louis.
The metabolic link runs deeper than a diabetes diagnosis. One study looked at patients whose neuropathy had been labeled idiopathic (no known cause). Of them, 34% turned out to have impaired glucose tolerance. That is about three times the rate in age-matched controls. In many of them, the fasting glucose and HbA1c were normal. Only a two-hour glucose tolerance test revealed the problem.5 A separate series looked at idiopathic neuropathy patients with normal blood sugar (normoglycemic). Even they carried a heavy load of metabolic syndrome features. Lipid (blood fat) problems were especially common.6
So when the feet start burning, the useful question is not only “how bad is the nerve damage” but “what is the metabolic environment that produced it.” Those symptoms are often the first visible sign of a body-wide problem. That problem has not been named yet. The mechanism is covered in how sugar damages nerves.
When should you see a doctor for neuropathy in your feet?
Most feet-first neuropathy develops over years. Some cases should not wait:
- Rapid progression over days or weeks
- Marked weakness, rather than mostly sensory symptoms
- Symptoms that are clearly uneven between sides, or limited to one nerve’s territory
- Symptoms beginning in the hands and feet at the same time
- Any open wound, ulcer, unexplained swelling, redness or warmth in a numb foot
- New bladder or bowel changes alongside the foot symptoms
The last of these can signal a problem above the peripheral nerve entirely. It needs a prompt evaluation.
How is peripheral neuropathy in the feet diagnosed?
“You have neuropathy” is a restatement of your symptoms, not an answer. A useful evaluation pins down three things. Which fibers are affected? How far has the damage gone? What is driving it? That takes a proper neurologic exam. It takes electrodiagnostic testing (electrical nerve testing) when the large fibers are in question. And it takes a real search for the driver. The driver can be metabolic, nutritional, autoimmune, toxic, drug-related (pharmacologic) or structural. At Regenerve, electrodiagnostic testing is performed on site. The full range of drivers worth ruling out is in the 11 hidden drivers of peripheral neuropathy. What treatment follows is in peripheral neuropathy treatments for the feet. The non-drug options are graded in alternative medicine for peripheral neuropathy.
Being evaluated in St. Louis
Regenerve is at 4477 Woodson Rd #104, St. Louis, MO 63134, minutes from St. Louis Lambert International Airport, and is led by Dr. Gurpreet Singh Padda, MD, MBA, MHP. The practice serves the St. Louis region, Missouri and Illinois.
Call (314) 886-5739 or text (314) 886-5902, or email info@regenerve.com. Office hours are Monday through Thursday 9:00 to 16:00 and Friday 9:00 to 13:30. Details are on the contact page and the locations page.
If you recognize your feet in this article, try the Nerve Damage Score. It is a five-question assessment that produces a large-print report you can bring to any doctor.
Frequently asked questions
What are the first symptoms of peripheral neuropathy in the feet?
Usually tingling, burning or numbness starting in the toes of both feet. It is often worse at night. It often comes with a vague sense of unsteadiness on uneven ground. See the hidden drivers of peripheral neuropathy.
Why are my neuropathy symptoms worse at night?
At rest, fewer other sensations compete, so nerve firing on its own (spontaneous firing) stands out more. Skin temperature changes at night can also amplify small-fiber symptoms. See small fiber neuropathy symptoms and testing.
Does peripheral neuropathy always affect both feet?
Metabolic neuropathy is typically symmetrical. It affects both feet. Symptoms in one foot only suggest a different mechanism, such as nerve compression. See carpal tunnel, sciatica and double crush.
My nerve test was normal but my feet still burn. Is that possible?
Yes. Standard nerve conduction studies measure large fibers. A small-fiber neuropathy can cause severe burning while those studies read normal. See small fiber neuropathy symptoms and testing.
Is numbness in the feet more serious than pain?
In terms of risk, yes. Numbness means the foot has stopped reporting injury. That is how minor wounds get worse unnoticed. Daily visual foot checks become essential. See peripheral neuropathy treatments for the feet.
Can I have neuropathy symptoms without diabetes?
Yes. In a national U.S. sample, 11.6% of adults aged 40 and older without diabetes had peripheral neuropathy. Many idiopathic (no known cause) cases have impaired glucose tolerance or other metabolic syndrome features that routine testing missed. See how sugar damages nerves.
What is the first stage of peripheral neuropathy?
In most metabolic neuropathy, the small nerve fibers fail first. That stage brings burning, pinprick pain, and changed temperature sense. Sometimes the feet stop sweating or the skin turns dry and shiny. Numbness, lost vibration sense, poor balance and weak ankle reflexes come later. That is when the large fibers are involved. Standard nerve tests measure large fibers, so this early stage can be missed.
Is it safe to walk barefoot with neuropathy in your feet?
Not when the feeling in your feet is reduced. Numb feet stop reporting damage, so a stone, a blister or a crack in the heel can go unnoticed. It can then get worse without hurting. Reduced temperature sense also makes burns from hot water or heating pads a real risk. Anyone who fails the 10-gram monofilament test needs well-fitted footwear and a daily look at both feet.
Can neuropathy in the feet affect other parts of the body?
Yes. The same small fibers that carry pain also control sweating, blood vessel tone and organ function. When they are damaged, people can notice lightheadedness on standing and sweating changes. They can feel full early after meals, or have constipation or diarrhea. Bladder changes and erectile dysfunction can show up too. These often get reported to different specialists as separate problems. But they frequently come from one process.
Sources
- Tesfaye S, et al. Diabetic neuropathies: update on definitions, diagnostic criteria, estimation of severity, and treatments. Diabetes Care. 2010. PMID 20876709
- Boulton AJM, et al. Comprehensive foot examination and risk assessment: a report of the task force of the foot care interest group of the American Diabetes Association. Diabetes Care. 2008. PMID 18663232
- Terkelsen AJ, et al. The diagnostic challenge of small fibre neuropathy: clinical presentations, evaluations, and causes. The Lancet Neurology. 2017. PMID 29029847
- Hicks CW, Wang D, Matsushita K, Windham BG, Selvin E. Peripheral Neuropathy and All-Cause and Cardiovascular Mortality in U.S. Adults: A Prospective Cohort Study. Annals of Internal Medicine. 2021. PMID 33284680
- Singleton JR, Smith AG, Bromberg MB. Increased prevalence of impaired glucose tolerance in patients with painful sensory neuropathy. Diabetes Care. 2001. PMID 11473085
- Smith AG, Rose K, Singleton JR. Idiopathic neuropathy patients are at high risk for metabolic syndrome. Journal of the Neurological Sciences. 2008. PMID 18606421