
Peripheral neuropathy treatments for the feet come in two kinds. Some treat the sensation. Others treat whatever is damaging the nerve. Both have a place, but only the second one changes where you end up in five years.
Say the burning, numbness or electric pain sits in both feet. The first question almost everyone asks is what can be done about it.
Most feet-first neuropathy starts with metabolism. Metabolic damage responds to being addressed at the source, not just muffled. That is the core idea behind everything below.
Why does neuropathy start in the feet?
The nerves running to your toes are the longest cells in the body. A single sensory axon (the long wire of a nerve cell) runs from the base of the spine to the sole of the foot on one unbroken supply line. It is fed by the smallest blood vessels in the peripheral nervous system, the vasa nervorum. That combination — the longest distance, the highest fuel demand, the most fragile blood supply — makes the far end of the nerve the first thing to fail when fuel and oxygen delivery falters.
This is why the pattern is so consistent. Symptoms begin in the toes and work upward on both sides evenly. They reach the fingers only later, once the damage has climbed to about knee height. Clinicians call it a length-dependent or “stocking-glove” distribution. It is the fingerprint of a whole-body process, not a local injury.1 We break that pattern down in peripheral neuropathy of the feet symptoms.
Want to learn more about nerve pain and the treatments we use? Get our neuropathy video series by email.
Can you have neuropathy in your feet without diabetes?
One national sample covered 7,116 U.S. adults aged 40 and older. Peripheral neuropathy was present in 13.5% of them. That was 27.0% of adults with diabetes, but also 11.6% of adults without it. Over a median 13 years of follow-up, neuropathy was independently associated with death from any cause in both groups.2
Read that second figure again. More than one in ten adults with no diabetes diagnosis had measurable loss of feeling in the foot. Losing feeling in your feet is not a harmless nuisance of aging. It is a signal about the state of the blood vessels and metabolism that supply them.
The metabolic terrain, not just the glucose number
Here is the finding that should change how neuropathy is worked up. Researchers properly tested 107 patients in a row with so-called idiopathic neuropathy (neuropathy with no known cause). Of those, 36 — 34% — had impaired glucose tolerance. That is nearly three times the rate in controls of the same age. In many of those patients the fasting glucose and the HbA1c were normal. Only the two-hour oral glucose tolerance test was abnormal.3
A normal A1c does not rule out a glucose-driven neuropathy. It rules out one way of measuring glucose handling.
And glucose is only one lever. Another study looked at 219 patients with idiopathic neuropathy. Some had fully normal blood sugar. They carried just as heavy a load of metabolic syndrome features as those with impaired glucose tolerance. Lipid (blood fat) problems were especially common. The patients had higher total and LDL cholesterol and more abnormal HDL and triglycerides than a comparison group of people who had diabetes but no neuropathy.4
Nerves are damaged by the whole metabolic environment acting together. That means glucose, insulin resistance, triglycerides, blood pressure, oxidative stress and the tiny blood vessel supply. That is what we mean by nerve terrain. It is the reason a treatment plan that only adjusts one number tends to stall.
The fibers that fail first in this process are the small ones. That is also why a standard nerve conduction study can read normal while the feet burn every night. That situation is common enough to deserve its own article: small fiber peripheral neuropathy symptoms and testing.
It also fits what we see in our own patients. Fewer than 3% of the people who come to the Padda Institute practice are metabolically healthy by standard criteria. Among those with chronic pain, it is fewer than 1%. Those are practice-reported figures from our own population, not trial outcomes, and individual results vary. But they tell you which direction to look first.
What medications help neuropathy pain in the feet?
Medication for nerve pain is legitimate and often necessary. It should also be described accurately. It changes what you feel, not what is happening to the nerve.
The 2022 American Academy of Neurology guideline pooled the trial evidence for painful diabetic polyneuropathy. It found the major drug classes taken by mouth bunched tightly together. Gabapentinoids showed a standardized mean difference of 0.44. SNRIs showed 0.47, and sodium channel blockers 0.56. SNRI/opioid dual-mechanism agents showed 0.62. All of them sit just above or just below the line for a medium effect size. Tricyclic antidepressants showed a large effect size, but with low confidence in the estimate.5
Two practical conclusions follow. First, no oral drug is dramatically better than the others. So the choice should be driven by your other conditions, your sleep, your mood and the side effects you can tolerate. If one class fails, trying a different class is a reasonable next step. Second, the same guideline states that clinicians should not use opioids for painful diabetic neuropathy. That is a formal recommendation, not a preference.
High-concentration topical capsaicin is the one symptom treatment that can plausibly claim to do more than muffle. The 8% patch works by switching off overactive pain fibers (nociceptive fibers) in the skin. There is published evidence of nerve fiber regeneration afterward, alongside the pain relief.6 We use it at Regenerve. It is covered in more depth in our article on the high-concentration capsaicin protocol.
Treatments aimed at the cause
Glucose control — necessary, and by itself not sufficient
A Cochrane review of 17 randomized studies found that tighter glucose control clearly prevents clinical neuropathy in type 1 diabetes. The yearly risk difference was −1.84%. In type 2 diabetes the same approach cut new cases of clinical neuropathy. But that did not reach formal statistical significance. It did significantly improve nerve conduction and vibration thresholds (the smallest buzz the feet can feel). Tight control also significantly raised the risk of severe hypoglycemia (dangerously low blood sugar).7
This is one of the most useful and least-quoted findings in the field. Most of our patients have type 2 diabetes. In that group, chasing the glucose number alone does not do the job. The lipid, blood pressure, weight and insulin-resistance parts of the terrain have to be treated as part of the neuropathy plan. They are not separate problems that belong to a different doctor.
Diet and exercise, measured at the nerve
Thirty-two patients with impaired glucose tolerance and neuropathy got individualized diet and exercise counseling for one year. They had skin biopsies before and after. Intraepidermal nerve fiber density went up. That is the count of tiny nerve endings in the skin. It rose by 1.4 fibers per millimeter at the proximal site, the spot closer to the trunk. The improvement correlated with reduced nerve pain.8
Nerve fibers grew back. Not in an animal model — in people, measured on biopsy, after a year of changing what they ate and how much they moved. This is still one of the strongest arguments for treating the metabolic terrain as the main intervention. It is not the lifestyle advice you give on the way out the door. We cover the training side of this in exercises for peripheral neuropathy in the feet.
Finding the driver that is not metabolic
Not every neuropathy is metabolic, and some of the non-metabolic causes are correctable. Here are the ones worth ruling in or out. One is functional B12 deficiency, which can be present despite a normal B12 level. Another is gluten-related nerve injury, including cases with a negative celiac test. Then there is autoimmune disease, and medications including statins and long-term metformin. There are heavy metals, mold and mycotoxins and alcohol. There is malabsorption after surgery. And there is nerve compression, which can exist alongside a metabolic neuropathy and make it worse. The full account is in the 11 hidden drivers of peripheral neuropathy.
The therapies we add on top
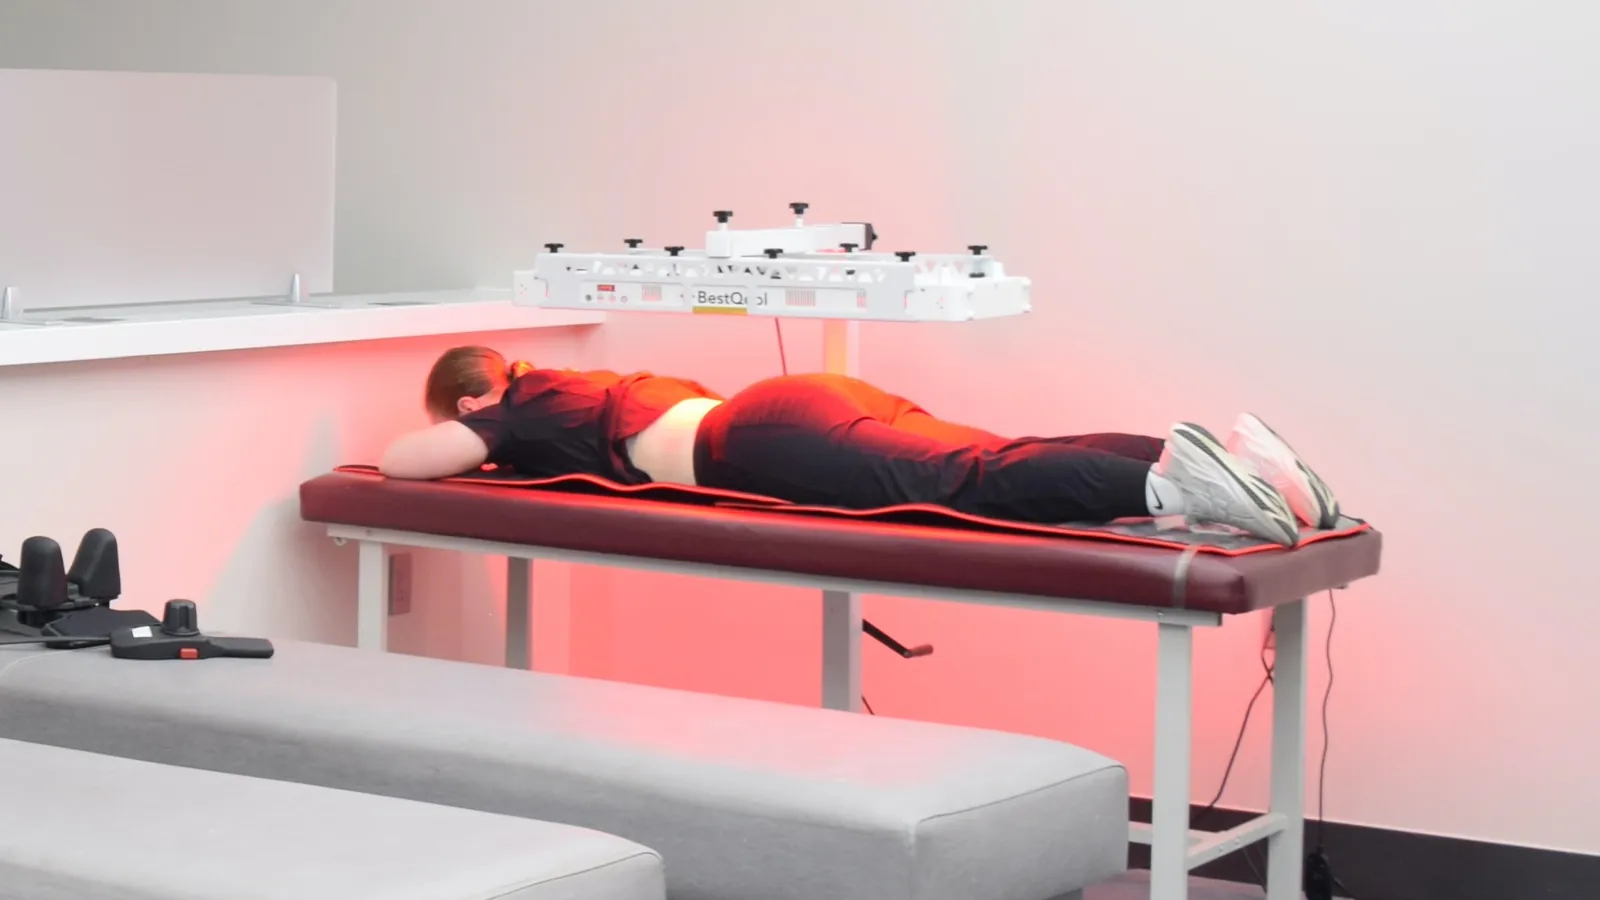
Once the driver is identified, treatment can be aimed at it. At our St. Louis clinic that toolkit includes class 4 photobiomodulation, class 3B cold laser and whole-body infrared. It also includes peripheral and vagal nerve stimulation, nutritional counseling, and balance and gait training. Where protective sensation has been lost, it includes wound care. Orthobiologic injections including PRP and BMAC are also offered. They are used as add-ons inside a plan — never as a substitute for finding the cause. The full list is on our services page, and the reasoning behind the order is in the Regenerve Protocol.
Supplements and complementary approaches
Some have real randomized evidence. Alpha-lipoic acid, acetyl-L-carnitine, palmitoylethanolamide and acupuncture are among them. Some widely sold products have failed when tested properly. We grade them one by one in alternative medicine for peripheral neuropathy.

How do you protect numb feet while you treat them?
When feeling drops below a certain threshold, the foot stops reporting injury. That is what makes neuropathy dangerous, not merely uncomfortable. A 10-gram monofilament test finds loss of protective sensation. Anyone who has it needs daily visual foot checks and properly fitted footwear. They need prompt care for any blister, crack or callus — because the usual warning signal is gone.9 Never soak numb feet in water you have not tested with your hand or a thermometer.
Honest expectations
Nerve tissue repairs slowly, and not all damage can be reversed. Progress is measured in less pain, better sleep, steadier balance and better function. That usually takes months, not weeks. Anyone promising a cure for peripheral neuropathy is telling you something that cannot be supported. What can often be changed is the trajectory, especially when an active driver is found and treated.
Being evaluated in St. Louis
Regenerve is at 4477 Woodson Rd #104, St. Louis, MO 63134, minutes from St. Louis Lambert International Airport. It is led by Dr. Gurpreet Singh Padda, MD, MBA, MHP. The practice serves the St. Louis region, Missouri and Illinois. Electrodiagnostic testing is done on site, so the evaluation and the results happen in the same place.
Call (314) 886-5739 or text (314) 886-5902, or email info@regenerve.com. Office hours are Monday through Thursday 9:00 to 16:00 and Friday 9:00 to 13:30. Details are on the contact page and the locations page.
The clearest place to begin is the Nerve Damage Score. It is a five-question assessment that produces a large-print report you can bring to any physician.
Frequently asked questions
What is the best treatment for peripheral neuropathy in the feet?
There is no single best treatment, because the right one depends on what is damaging the nerve. Pain medication, topical capsaicin, metabolic correction and nerve-directed therapies all have a place. The plan should follow the diagnosis, not come before it. See the Regenerve Protocol.
What is the best treatment for diabetic neuropathy in the feet?
There is no single drug that fixes it. In diabetes the nerve damage is driven by the metabolic terrain. So the treatment that changes the nerve is the treatment aimed at that terrain. In studies, nerve fiber density on skin biopsy has risen with that kind of treatment. But that work is measured in months, and no one can promise a cure.
Pain medication is worth having in the meantime, but do not confuse the two. Gabapentinoids, SNRIs and tricyclics treat the pain, not the nerve damage. And the major oral classes bunch tightly together in effect.
The reason the plan cannot stop at glucose is the evidence itself. A Cochrane review of 17 randomized studies found that tighter glucose control clearly prevents clinical neuropathy in type 1 diabetes. In type 2 — the group most of our patients belong to — it reduced new cases without reaching statistical significance. It also significantly raised the risk of severe hypoglycemia. Glucose is one lever, not the whole plan. Lipids, blood pressure, weight and insulin resistance belong in the neuropathy plan. They do not belong to a different doctor. See diabetic peripheral neuropathy treatment in St. Louis.
Can peripheral neuropathy in the feet be reversed?
Not reliably. In one study, diet and exercise counseling in patients with impaired glucose tolerance produced measurable regrowth of nerve fibers on skin biopsy after one year. Not all damage is reversible, and no one can promise a cure. See how sugar damages nerves.
My A1c is normal. Can my neuropathy still be metabolic?
Yes. In one study of patients with idiopathic neuropathy, 34% had impaired glucose tolerance. A normal fasting glucose and normal HbA1c had missed it. Only the two-hour glucose tolerance test revealed it. See how sugar damages nerves.
Should I be taking gabapentin or pregabalin?
They are reasonable options with a modest average effect, close to SNRIs, tricyclics and sodium channel blockers. They treat the pain, not the nerve damage. So they work best alongside treatment aimed at the cause. See the hidden drivers of peripheral neuropathy.
Are opioids used for neuropathy in the feet?
The American Academy of Neurology says not to use opioids for painful diabetic polyneuropathy. Our practice cuts opioid burden instead of adding to it. See which specialist you should see.
How long before treatment helps?
Symptom treatments can work within weeks. Treatment aimed at the underlying metabolic driver takes months, because nerves recover slowly, if they recover at all. See the Regenerve Protocol.
Is it good to walk with neuropathy in your feet?
Movement is part of treating the cause, not just the pain. In one study, people with neuropathy and impaired glucose tolerance got a year of diet and exercise counseling. It regrew nerve fibers in the skin, and their pain dropped as the fibers came back. If your feet are numb, wear properly fitted shoes. Check your feet every day for blisters or cracks. See exercises for peripheral neuropathy in the feet.
Can you die from peripheral neuropathy?
Treat it as a warning sign, not a nuisance. A national study looked at 7,116 U.S. adults aged 40 and older. People with neuropathy were more likely to die of any cause over a median of 13 years, whether or not they had diabetes. Numb feet also stop reporting injuries, so a small blister or crack can go unnoticed. That is why the cause needs to be found, not just the pain muffled.
Do vitamins or natural remedies help neuropathy in the feet?
Some do and some do not. Alpha-lipoic acid, acetyl-L-carnitine, palmitoylethanolamide (PEA) and acupuncture have real randomized evidence. Some widely sold products failed when tested properly. A vitamin can also matter in another way. Functional B12 deficiency is a correctable cause of neuropathy. It can be present even when the B12 blood level looks normal. See alternative medicine for peripheral neuropathy.
Sources
- Tesfaye S, et al. Diabetic neuropathies: update on definitions, diagnostic criteria, estimation of severity, and treatments. Diabetes Care. 2010. PMID 20876709
- Hicks CW, Wang D, Matsushita K, Windham BG, Selvin E. Peripheral Neuropathy and All-Cause and Cardiovascular Mortality in U.S. Adults: A Prospective Cohort Study. Annals of Internal Medicine. 2021. PMID 33284680
- Singleton JR, Smith AG, Bromberg MB. Increased prevalence of impaired glucose tolerance in patients with painful sensory neuropathy. Diabetes Care. 2001. PMID 11473085
- Smith AG, Rose K, Singleton JR. Idiopathic neuropathy patients are at high risk for metabolic syndrome. Journal of the Neurological Sciences. 2008. PMID 18606421
- Price R, et al. Oral and Topical Treatment of Painful Diabetic Polyneuropathy: Practice Guideline Update Summary. Neurology. 2022. PMID 34965987
- Anand P, et al. Reversing painful and non-painful diabetic neuropathy with the capsaicin 8% patch: clinical evidence for pain relief and restoration of function via nerve fiber regeneration. Frontiers in Neurology. 2022. PMID 36388188
- Callaghan BC, Little AA, Feldman EL, Hughes RA. Enhanced glucose control for preventing and treating diabetic neuropathy. Cochrane Database of Systematic Reviews. 2012. PMID 22696371
- Smith AG, et al. Lifestyle intervention for pre-diabetic neuropathy. Diabetes Care. 2006. PMID 16732011
- Boulton AJM, et al. Comprehensive foot examination and risk assessment: a report of the task force of the foot care interest group of the American Diabetes Association. Diabetes Care. 2008. PMID 18663232