

A skin punch biopsy counts the nerve fibers inside the epidermis (the top layer of skin). It reports that count as intraepidermal nerve fiber density, or IENFD. A low count is objective evidence that the small sensory fibers are damaged. These are the fibers that carry pain and temperature. They are the ones that cause burning feet while a standard nerve conduction study reads normal.
What the biopsy does not tell you is why those fibers are failing. That is the part that decides treatment. It comes from the rest of the workup, not from the number.
The test is used well beyond classic neuropathy cases. About 40% to 60% of patients with a fibromyalgia diagnosis show signs of small fiber neuropathy on skin punch biopsy.1
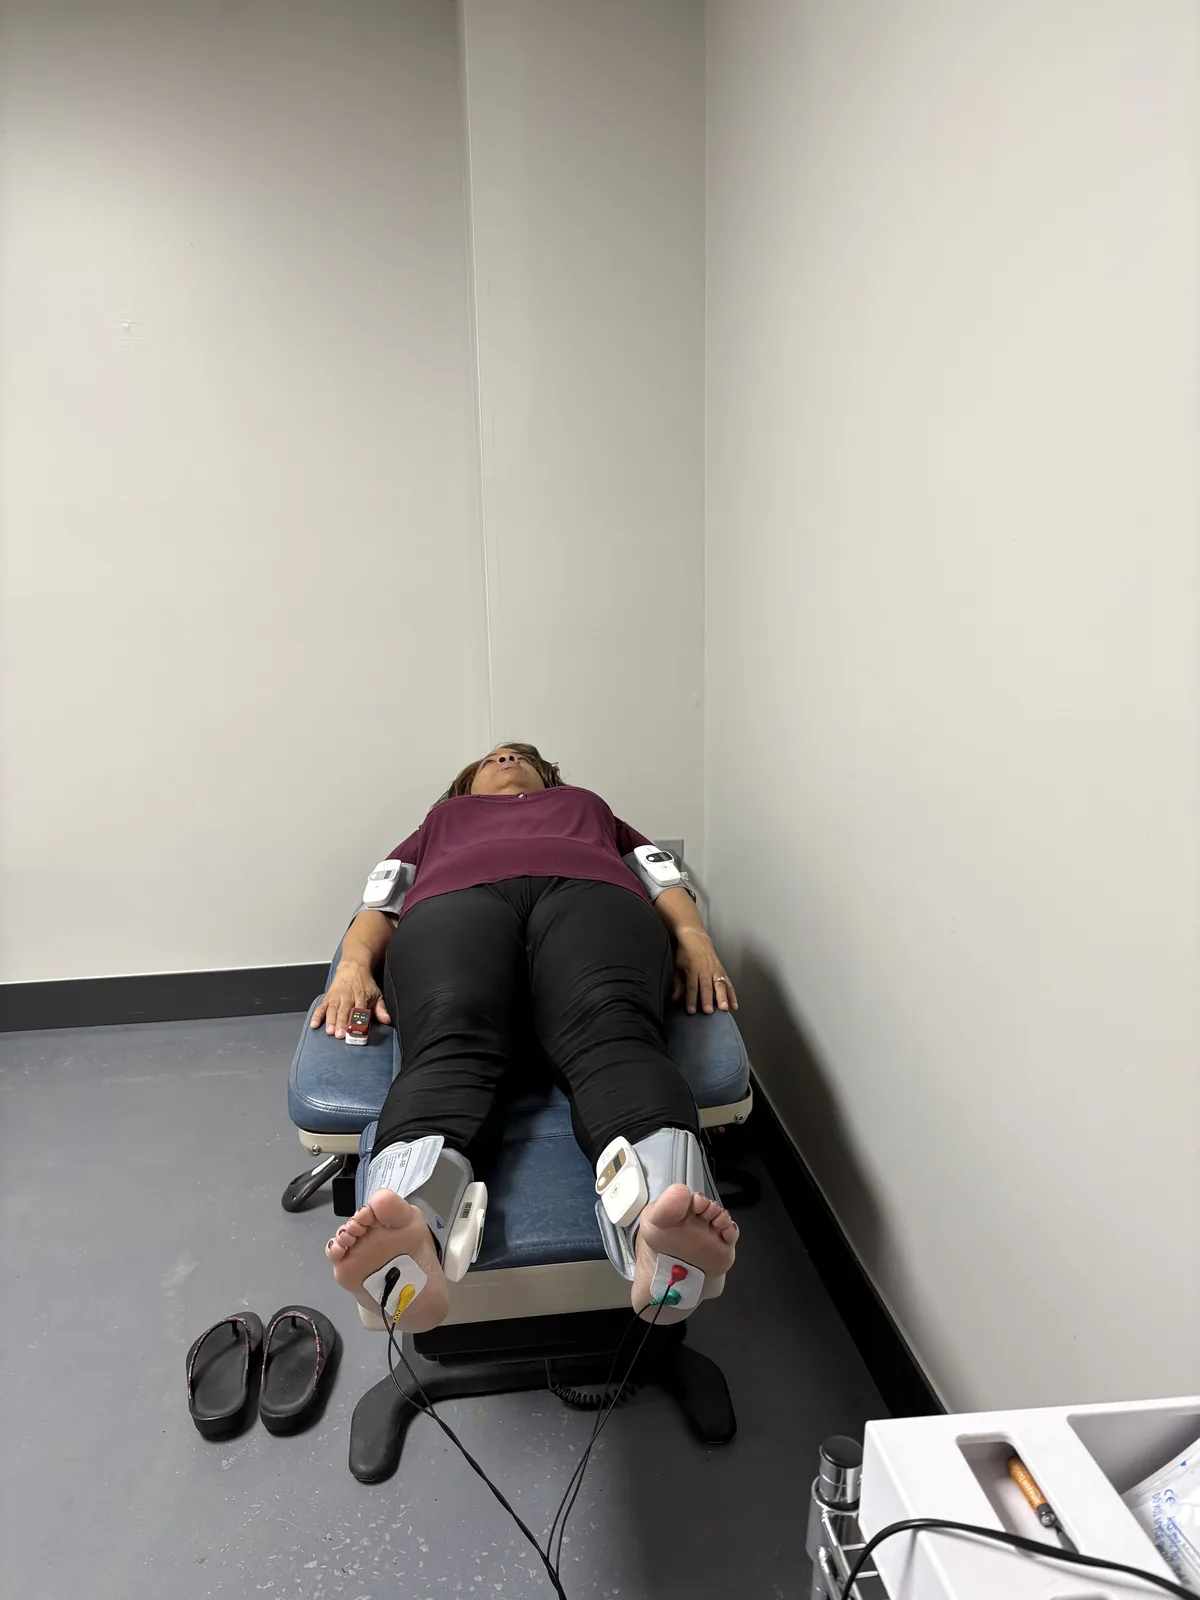
Regenerve does the punch skin biopsy on site. The sample is taken during a clinic visit instead of being sent out.
How is a skin biopsy for small fiber neuropathy done?
A 3 mm punch is pressed into the biopsy site to take a small cylinder of skin, usually from the lower leg.1 The sample goes to a lab. The lab stains the nerve fibers and counts how many cross into the epidermis per millimeter of tissue. That count is compared with normal values matched to site, age and sex.
It is a minor office procedure, not surgery. It samples the fibers directly instead of inferring (working out) their state from an electrical signal.
Want to learn more about nerve pain and the treatments we use? Get our neuropathy video series by email.
Why is my nerve conduction study normal if my feet burn?
Nerve conduction studies measure large myelinated fibers (fibers with a thick insulating coat). Small fibers have no coat or only a thin one. They do not add to that signal. So they can be badly damaged while the study reads normal.
Peripheral neuropathy is mainly diagnosed in the exam room. The doctor takes your history and checks your nerves. Small fiber sensation is tested with temperature or pinprick. Large fiber sensation is tested with vibration. Ulcer risk is tested with 10 g monofilament pressure testing.2 Nerve conduction studies and intraepidermal nerve fiber density testing are called for when the case is unusual (atypical). Examples are fast symptom onset, severe nerve-and-muscle weakness (neuromotor impairment), or feeling that is abnormal on one side more than the other.2
Regenerve does electrodiagnostic testing (EMG/NCS) on site. We read it against the whole clinical picture instead of treating it as a verdict. A normal study in someone with burning feet is a reason to look at the small fibers, not a reason to stop looking.
How accurate is a skin biopsy for small fiber neuropathy?
By current normal values, the nerve fiber count in the skin (epidermal nerve fiber density) is abnormally low in only about two-thirds of patients thought to have small fiber neuropathy.3 That means roughly one in three patients with a convincing clinical picture will have a biopsy that reads normal.
Normal ranges, the sampling site and lab methods all shift where the line between normal and abnormal falls. A single number on its own is not a diagnosis. If your symptoms fit and the result is normal, that is a reason to widen the search, not to stop.
What each result changes
- Low IENFD. Small fiber damage is confirmed. The question moves entirely to which driver is producing it.
- Normal IENFD with fitting symptoms. The clinical picture still stands. Other or overlapping mechanisms get evaluated. The biopsy result is recorded, not used to dismiss the complaint.
- Normal IENFD with an atypical picture. The list of possible causes widens beyond small fiber involvement.
What causes small fiber neuropathy?
Neuropathy is a category, not a diagnosis. Small fiber damage can come from metabolic, nutritional, autoimmune, toxic or structural drivers. It is common for more than one to be active at the same time.
That is where the real work of the evaluation lives — finding which mechanism is doing the damage, then aiming treatment at it. Our discussion of the causes that most often get missed is in the hidden drivers of peripheral neuropathy.
Driver categories we work through
- Metabolic. How the body handles sugar, insulin resistance, and injury from glycation (sugar sticking to proteins).
- Nutritional. Trouble absorbing nutrients, and nutrient status. This includes after belly or weight-loss (bariatric) surgery.
- Autoimmune. Inflammation through the whole body, and the immune system attacking the body.
- Toxic. Medications, alcohol, chemo drugs and toxins in the world around you.
- Structural. Pinched nerves and mechanical causes that can sit on top of any of the above.
How is small fiber neuropathy treated at Regenerve?
At Regenerve the biopsy result feeds into a plan built around the cause we find. That plan can include class 4 photobiomodulation, class 3B cold laser, whole-body infrared, and metabolic and nutritional care.
Orthobiologic injections (PRP and BMAC) are offered. When balance complaints are part of the picture, VNG (videonystagmography) may be used as a diagnostic test of inner-ear balance function. It is not a treatment. Nothing offered here reverses or regenerates nerve damage, and no outcome is promised.
Questions worth asking before a biopsy
- What in my history makes small fiber damage the top suspect?
- Which site will be sampled, and which lab and normal values will be used?
- What will change in my evaluation if the result is low?
- What is the next step if the result comes back normal but my symptoms do not?
Being evaluated in St. Louis
Regenerve is at 4477 Woodson Rd #104, St. Louis, MO 63134, minutes from St. Louis Lambert International Airport, and is led by Dr. Gurpreet Singh Padda, MD, MBA, MHP. The practice serves the St. Louis region, Missouri and Illinois.
Call (314) 886-5739 or text (314) 886-5902, or email info@regenerve.com. Office hours are Monday through Thursday 9 a.m. to 4 p.m. and Friday 9 a.m. to 1:30 p.m.
If a nerve test came back normal and your feet still burn, start with the Nerve Damage Score. It is a free five-question assessment that produces a large-print report you can bring to any physician.
Frequently asked questions
What does a skin biopsy for small fiber neuropathy involve?
A 3 mm punch takes a small cylinder of skin, usually from the lower leg. A lab counts how many nerve fibers cross into the epidermis per millimeter. It is an office procedure, not surgery. See the testing and services we provide.
How is it different from an EMG and nerve conduction study?
Nerve conduction studies measure large myelinated fibers. The biopsy counts the small fibers directly. That is why you can have burning feet and a nerve conduction study that reads normal. See burning feet and nerve pain.
Can I have small fiber neuropathy if my biopsy is normal?
Yes. By current normal values, epidermal nerve fiber density is abnormally low in only about two-thirds of patients thought to have small fiber neuropathy. So a normal result does not rule out the diagnosis. See how to choose a neuropathy specialist.
If my biopsy is abnormal, what happens next?
The work shifts to finding which driver is damaging the fibers — metabolic, nutritional, autoimmune, toxic or structural. That is what decides treatment, not the density number itself. See how sugar damages nerves.
Is this test only relevant to diabetes?
No. Small fiber damage shows up with nutritional, autoimmune and toxic drivers as well. And roughly 40% to 60% of patients with a fibromyalgia diagnosis show signs of it on skin punch biopsy. See functional B12 deficiency and neuropathy.
What does IENFD mean on a biopsy report?
IENFD stands for intraepidermal nerve fiber density. The lab stains the skin sample. It counts how many small nerve fibers cross into the epidermis per millimeter of tissue. That number is compared with normal values matched to the biopsy site, your age and your sex. A low count is objective evidence that the small fibers carrying pain and temperature are damaged.
Who does skin biopsies for small fiber neuropathy in St. Louis?
Regenerve does the punch skin biopsy on site at 4477 Woodson Rd #104, St. Louis, MO 63134. The sample is taken during a clinic visit instead of being sent out. EMG/NCS nerve testing is also done in the same office. That lets us read both results against your history together.
What is the best treatment for small fiber neuropathy?
The one aimed at whatever is damaging the fibers. The biopsy confirms the damage but not the cause. So the driver comes first: metabolic, nutritional, autoimmune, toxic or structural. At Regenerve the plan can include class 4 photobiomodulation, class 3B cold laser, whole-body infrared, and metabolic and nutritional care. Nothing offered here reverses or regenerates nerve damage.
Sources
- Kelley MA, Hackshaw KV. Intraepidermal Nerve Fiber Density as Measured by Skin Punch Biopsy as a Marker for Small Fiber Neuropathy: Application in Patients with Fibromyalgia. Diagnostics (Basel). 2021;11(3):536. PMID 33802768
- Bodman MA, Dreyer MA, Varacallo MA. Diabetic Peripheral Neuropathy. StatPearls. StatPearls Publishing. 2024. NCBI Bookshelf NBK442009
- Levine TD, Saperstein DS. Diagnosing Small Fiber Neuropathy Through the Use of Skin Biopsy. Practical Neurology. October 2009. practicalneurology.com