Category: Toxic & Environmental Drivers

  • Chemotherapy-Induced Peripheral Neuropathy (CIPN): Causes and Management

    Chemotherapy-Induced Peripheral Neuropathy (CIPN): Causes and Management

    Chemotherapy-induced peripheral neuropathy is nerve injury caused by cancer drugs that harm nerves. It is common. About 30 to 40% of patients treated with nerve-toxic chemotherapy will develop CIPN, and how bad it gets varies a lot from person to person.1 It mostly affects feeling and often comes with pain. It can cause long-term problems.1 That is why care has to look at more than the pain score.

    The real question is not whether you have neuropathy. It is which causes are adding to it in your case, and which of them can still be cut back.

    Key takeaways

    • CIPN is usually sensory-predominant. Burning, numbness and electric feelings are more typical than weakness.1
    • The chemotherapy is rarely the only factor. Nutrition and metabolic weak spots can sit underneath it.
    • Testing narrows the question. We do electrodiagnostic testing (EMG and nerve conduction studies) on site.
    • Symptom control is not nerve repair. Medicine that turns down the signal has a role, but it is not the whole plan.
    • Nothing here is promised as regeneration or cure. The goals are fewer misfires, better function and safer walking.

    What causes chemotherapy-induced peripheral neuropathy?

    Nerve-toxic chemotherapy drugs can injure nerve fibers directly. The damage usually shows up far from the center of the body and hits feeling first. The feet and hands go first, and feeling goes before strength.1 That is the main cause, and it is the one people already know about.

    What gets less attention is the terrain the injury lands on. Nerve fibers depend on working tiny blood vessels and on enough nutrients. When either is weak before treatment starts, the same dose of the same drug lands on a weaker nerve.

    Where the overlapping contributors show up

    • Metabolic stress, such as insulin resistance or diabetes that was never diagnosed
    • Nutritional deficiency, such as B12 deficiency and functional B12 deficiency
    • Reduced microvascular perfusion, meaning less blood flow in the small vessels that feed nerve tissue
    • Pre-existing neuropathy from a cause that was never found

    None of these replaces the chemotherapy as the trigger. They change how much injury a given dose causes, and how much room there is to recover afterward. Our overview of the hidden drivers of peripheral neuropathy covers the ones that most often go unchecked.

    How is chemo-induced neuropathy diagnosed?

    The workup has one job: turn “I have neuropathy” into a clear picture of which fibers are hurt and what else is adding to it. Without that, treatment aims at a category instead of a cause.

    What the evaluation includes

    • Electrodiagnostic testing (EMG and nerve conduction studies), done on site, to map large-fiber damage and where it is
    • Metabolic and nutritional review, to find problems that can be fixed
    • VNG balance testing when balance is affected. VNG is a test of inner-ear balance, not a treatment.
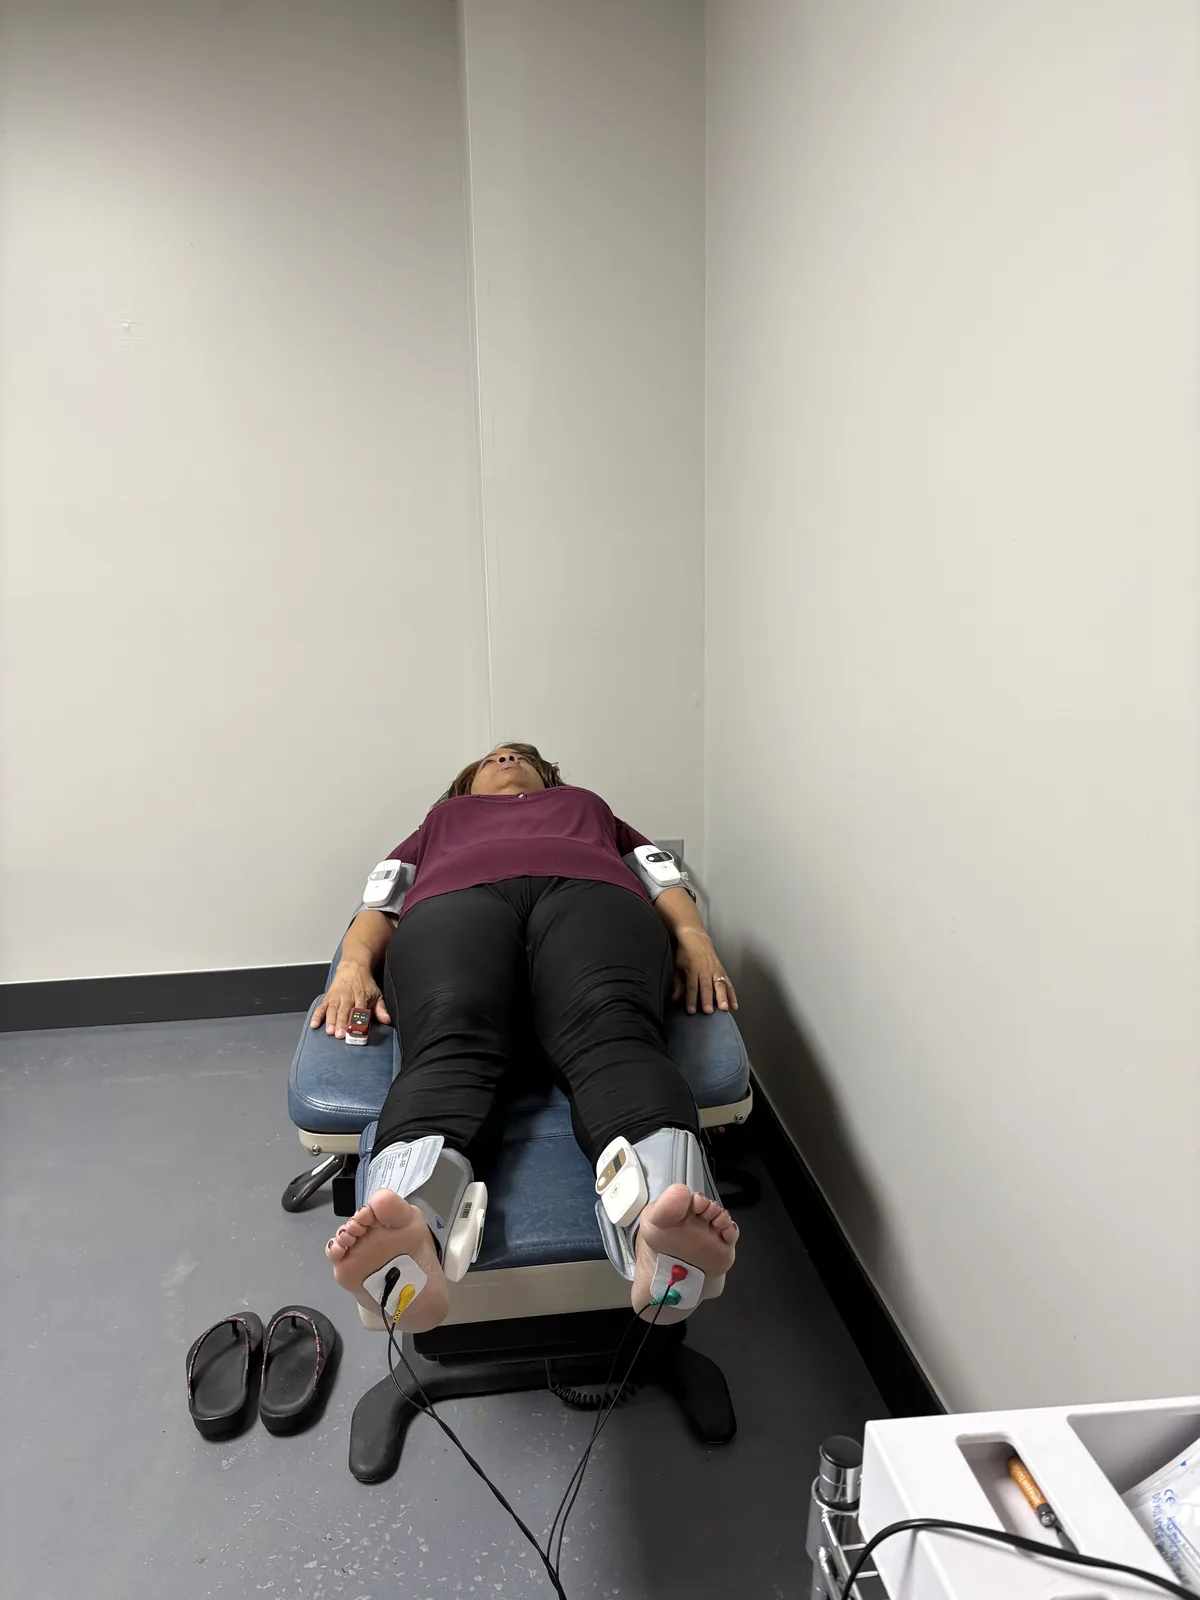
    Patient reclined for small-fiber and autonomic nerve testing, with sensor cuffs on both ankles and wrists, at Regenerve, 4477 Woodson Rd, St. Louis, MO 63134

    Why the exam matters as much as the test

    Small nerve fibers carry burning, temperature and pins-and-needles feelings. They can be badly injured while routine nerve conduction testing still reads close to normal. A normal study does not mean nothing is wrong. It means the test looked at the fibers it was built to look at.

    How is chemotherapy-induced neuropathy treated?

    CIPN care works in layers, because the nerve is under pressure from more than one side at once. Each layer has a clear job. None of them is the whole answer.

    Symptom control

    Cutting pain matters for sleep, safety and staying active. We treat it as volume control, not repair. And we are clear that a lower pain score is not proof the nerve has healed.

    Light-based and energy-based therapy

    At Regenerve, class 4 photobiomodulation, class 3B cold laser and whole-body infrared are part of a wider plan aimed at the nerve’s environment. We choose them when your symptoms and workup support them. We do not apply them to everyone the same way.
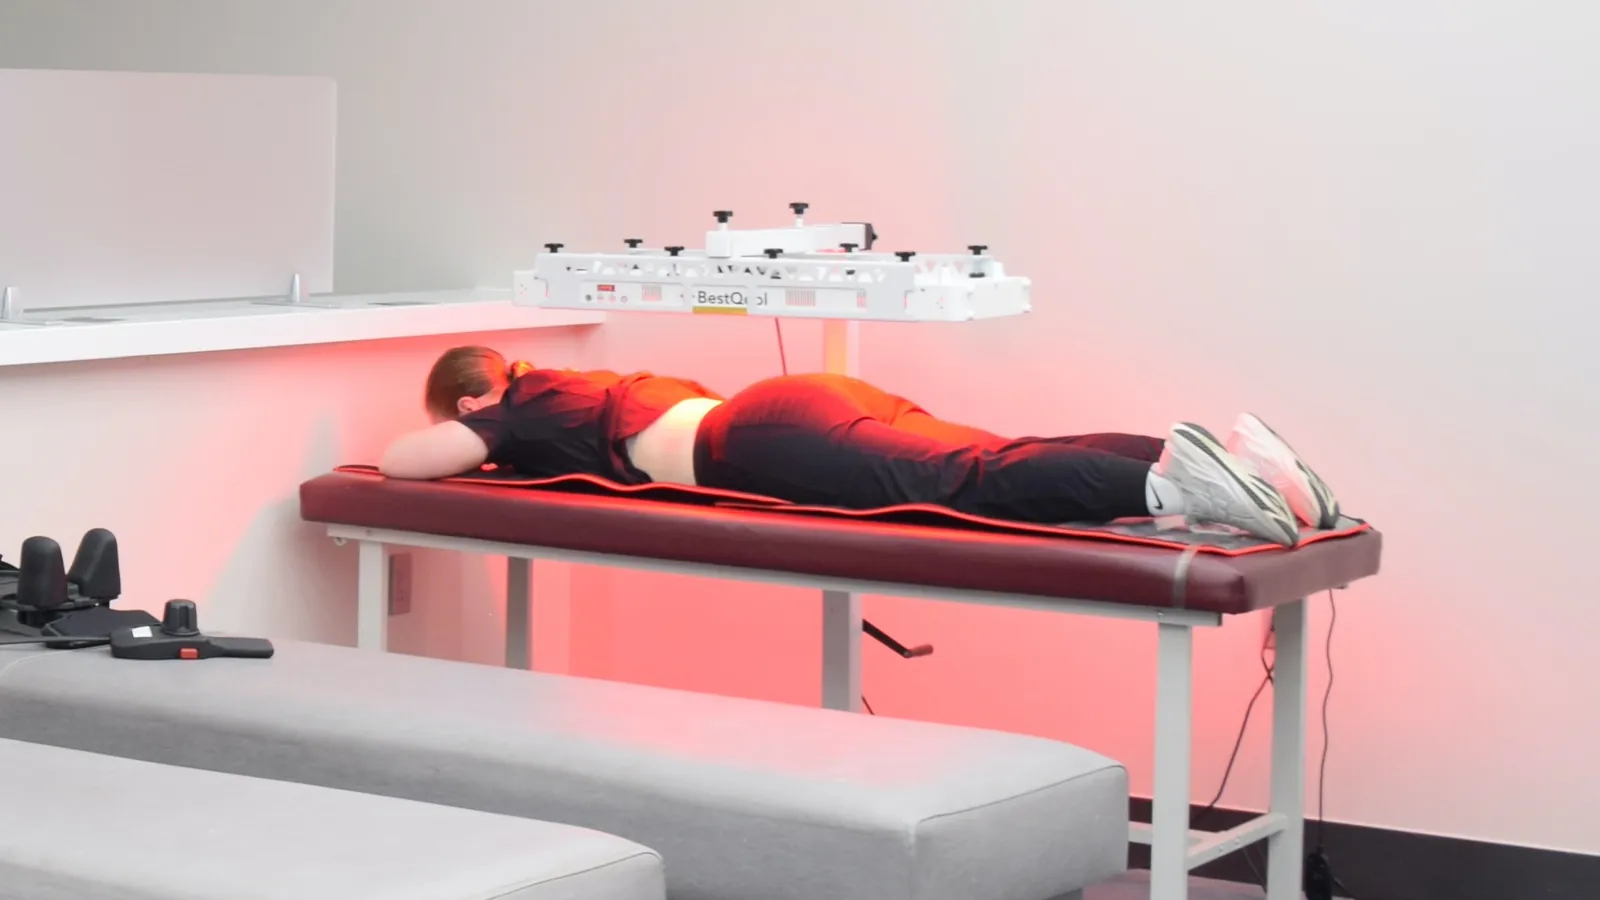
    Patient lying face down under a red-light photobiomodulation panel on a treatment table at Regenerve, 4477 Woodson Rd, St. Louis, MO 63134

    Metabolic and nutritional care

    When we find a nutrition or metabolic problem, fixing it is part of the plan, not an afterthought. This is also the area with the most consumer marketing. That is why we work from your workup, not from a supplement label.

    Orthobiologic injections

    Orthobiologic injections (PRP and BMAC) are offered in selected situations. We do not present them as a treatment for CIPN.

    Safety and function

    Dulled protective feeling changes your risk in ways that have nothing to do with pain. Daily foot checks, shoes that fit, and care on stairs and behind the wheel are part of the plan from the first visit.

    Where Qutenza fits, and where it does not

    Qutenza (capsaicin 8% patch) is indicated in adults for neuropathic pain associated with postherpetic neuralgia and for neuropathic pain associated with diabetic peripheral neuropathy of the feet.2 Chemotherapy-induced neuropathy is not on that list.

    Where it is used, it is applied in clinic by a clinician, never dispensed for home use, and repeated no more often than every three months. You can read more on our page about the Qutenza capsaicin 8% patch.

    When should you see a doctor for chemo neuropathy?

    • Numbness that gets worse fast, or new weakness
    • New falls or a sudden change in balance
    • A foot wound, skin breakdown, or an injury you did not feel happen
    • Pain bad enough to stop sleep or basic daily tasks

    Regenerve in the St. Louis region

    Regenerve treats peripheral neuropathy for patients across the St. Louis region, Missouri and Illinois, including Edwardsville, Glen Carbon, Collinsville, Troy and Maryville. The clinic is at 4477 Woodson Rd #104, St. Louis, MO 63134, minutes from St. Louis Lambert International Airport. Call (314) 886-5739 or text (314) 886-5902, or email info@regenerve.com.

    Your next step

    Maybe chemotherapy is behind your symptoms, but you suspect something else is adding to it. The free five-question Nerve Damage Score shows which group of causes most likely applies to you. Your answers guide what we check first.

    Frequently asked questions

    How common is chemotherapy-induced peripheral neuropathy?

    About 30 to 40% of patients treated with nerve-toxic chemotherapy will develop CIPN. How bad it gets varies a lot from patient to patient.1 Our workup for nerve symptoms, including on-site electrodiagnostic testing, is on the neuropathy services page.

    Why does my burning feel worse than my test results look?

    CIPN mostly affects feeling and often comes with pain.1 Routine nerve conduction testing does not pick up damage well in the small nerve fibers that carry burning and temperature. See small fiber neuropathy symptoms and testing.

    Can a vitamin deficiency make chemotherapy nerve symptoms worse?

    A nutrient shortage can sit underneath a chemotherapy injury and add to it. That is why the workup looks past the obvious trigger. See functional B12 deficiency and neuropathy.

    Does Qutenza [Capsaicin 8% Patch] treat CIPN?

    Qutenza [Capsaicin 8% Patch] is indicated in adults for neuropathic pain associated with postherpetic neuralgia and for neuropathic pain associated with diabetic peripheral neuropathy of the feet.2 Chemotherapy-induced neuropathy is not one of them. One of the two approved indications is covered in our article on postherpetic neuralgia and shingles nerve pain.

    What are the symptoms of chemotherapy-induced neuropathy?

    CIPN is usually sensory-predominant, often with pain.1 Burning, numbness and electric feelings are more typical than weakness. They tend to show up far from the center of the body: the feet and hands first, feeling before strength.1 Dulled protective feeling can also affect balance and your ability to notice a foot injury. That is why falls and unfelt wounds matter as much as the pain.

    Does neuropathy from chemo ever go away?

    It varies. How bad it gets differs a lot from one patient to the next, and CIPN can lead to long-term problems.1 How much room there is to recover depends partly on the terrain the injury landed on. That means blood sugar, nutrition, blood flow to the nerve, and any neuropathy that was already there. We do not promise regeneration or cure. The goals are fewer misfires, better function and safer walking.

    What is the best medication for chemo-induced neuropathy?

    No single pill is the whole plan. Medicine that turns down the pain signal has a role for sleep, safety and staying active. But we treat it as volume control, not repair. A lower pain score is not proof the nerve has healed. The Qutenza capsaicin 8% patch is labeled for postherpetic neuralgia and diabetic neuropathy of the feet.2

    Who is more likely to have severe chemo neuropathy?

    The chemotherapy is the trigger. But the terrain it lands on changes how much injury a given dose causes. Several things can mean the same dose hits a weaker nerve. These include undiagnosed insulin resistance or diabetes, and B12 deficiency or functional B12 deficiency. They also include less blood flow in the small vessels that feed nerve tissue, and an earlier neuropathy from a cause nobody found.

    Sources

    1. Staff NP, Grisold A, Grisold W, Windebank AJ, “Chemotherapy-induced peripheral neuropathy: A current review,” Annals of Neurology, 2017;81(6):772-781, https://pmc.ncbi.nlm.nih.gov/articles/PMC5656281/
    2. U.S. Food and Drug Administration, “QUTENZA (capsaicin) 8% topical system — prescribing information,” label effective July 7, 2026, via DailyMed, https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=3ffbbcb0-ad93-4f15-bb38-5da76a71c735
    3. Rahman N, Sukumar J, Lustberg MB, “Chronic chemotherapy-induced peripheral neuropathy: living with neuropathy during and after cancer treatments,” Annals of Palliative Medicine, 2025, https://apm.amegroups.org/article/view/136218/html
    4. Batash R, Asna N, Ali SH, Charkovsky T, Asali M, Pelles S, Schaffer M, “Management of Chemotherapy-Induced Peripheral Neuropathy (CIPN) in Oncologic Patients — A New Promise? Preliminary Results,” 2025, https://pmc.ncbi.nlm.nih.gov/articles/PMC12562927/

  • Chronic Kidney Disease and Uremic Neuropathy: Finding the Driver

    Chronic Kidney Disease and Uremic Neuropathy: Finding the Driver

    Uremic neuropathy is nerve injury that develops with advanced kidney disease. Its most important feature is how often it is there before it is obvious. A Tunisian cohort study looked at 31 children with stage G5 chronic kidney disease. Nerve conduction testing found uremic neuropathy in 45% of them. That included 13% who had silent neuropathy with no symptoms.3 Adults show the same gap. In 200 patients with predialysis CKD studied in India, prevalence was 45% based on symptoms and 90% on electrophysiological testing.1

    That gap between what patients feel and what testing finds is the practical case for looking early. Do not wait for symptoms to become convincing.

    Key takeaways

    • Symptoms lag behind nerve dysfunction. Silent neuropathy is well known in advanced CKD.3
    • Severity tracks with kidney function. In one adult cohort, prevalence rose from 55% in Stage 3 to 84.8% in Stage 5.2
    • Uremia is a driver, not the only driver. Nutrition, medicine, autoimmune and structural causes can overlap.
    • Testing separates fiber types. We do electrodiagnostic testing on site. It tells large-fiber patterns apart from what small fibers are doing.
    • No regeneration or cure is promised. The goals are less ongoing injury, better function and safer walking.

    What is uremic neuropathy?

    Uremic neuropathy means nerve injury that happens alongside advanced kidney disease. Patients describe burning, numbness, electric-shock feelings or less feeling. It usually starts in the feet and usually on both sides.

    Those descriptions alone do not show which nerve fibers are involved or what is causing the injury. In the Tunisian cohort of children, axonal neuropathy (damage to the nerve fiber itself) was the main pattern. No demyelinating cases (damage to the nerve’s coating) were found.3

    Small fiber and large fiber involvement look different

    Small fiber damage tends to cause burning, hot-coal feelings and pain at night. Large fiber damage tends toward numbness, less vibration sense and weaker protective feeling. That is what affects balance and safe walking.

    This matters because it changes what we watch and what counts as a real change over time.

    Patient reclined during peripheral vascular and nerve testing (CMAT) at Regenerve, St. Louis

    What else can cause neuropathy in kidney disease?

    When kidney disease is advanced, it is easy to stop looking there. But a nerve can be under pressure from several sides at once. The causes that can actually be cut back are often not the kidney disease itself.

    The overlaps that most often matter

    • Diabetes. Many patients with CKD also have diabetes. Diabetic nerve injury can worsen or mimic uremic nerve injury.
    • Nutritional deficiency. Diet limits, poor absorption and medicine effects all raise the risk in this group.
    • Medications. The medicine list deserves as much attention as the kidney stage.
    • Toxic and environmental exposures, including alcohol.
    • Autoimmune processes and structural compression, which can add a second, separate weak point.

    Finding which of these is adding to the damage is what turns a diagnosis into a plan. Our overview of the hidden drivers of peripheral neuropathy covers the ones most often left unchecked.

    How is uremic neuropathy diagnosed?

    The workup answers two separate questions. Which nerves are affected? And what is affecting them? Testing answers the first. History, the exam and a metabolic review answer the second.

    What it includes

    • Electrodiagnostic testing (EMG and nerve conduction studies), performed on site
    • Metabolic and nutritional review, aimed at causes that can be fixed
    • VNG balance testing when balance is affected. VNG is a test of inner-ear balance, not a treatment.
    Ankle blood pressure cuffs and sensors placed on a patient's feet during ankle-brachial index testing at Regenerve, 4477 Woodson Rd #104, St. Louis, MO 63134

    What testing does not settle

    A nerve conduction study describes the injury. It does not name the cause. And a study that reads close to normal does not rule out small fiber damage. That is why we read the result alongside the rest of the workup, not on its own.

    How is uremic neuropathy treated?

    Surgery is not part of the treatment plan for uremic neuropathy. Care focuses on the workup, mapping the damage and non-surgical treatment. The aim is to cut ongoing nerve injury and support function.

    The therapies used

    • Class 4 photobiomodulation and class 3B cold laser, chosen when the symptom pattern and workup support them
    • Whole-body infrared, used as part of the overall plan
    • Metabolic and nutritional care, when we have found a cause that can be fixed

    Kidney disease adds a limit we respect the whole way through. In this group, nutrition and metabolic changes are made together with the kidney team, not on their own.

    Orthobiologic injections

    Orthobiologic injections (PRP and BMAC) are offered in selected situations.

    What we do not promise

    We do not promise nerve regeneration, reversal or a cure. Nerve injury may have built up over years of advanced kidney disease. If so, the honest goals are less ongoing injury, better day-to-day function and safer walking.

    Qutenza in this setting

    Qutenza (capsaicin 8% patch) is indicated in adults for neuropathic pain associated with postherpetic neuralgia and for neuropathic pain associated with diabetic peripheral neuropathy of the feet.4

    Where it is used, it is applied in clinic by a clinician, never dispensed for home use, and repeated no more often than every three months. More detail is on our page about the Qutenza capsaicin 8% patch.

    Practical steps while you are being evaluated

    • Check both feet daily if feeling is dulled. Use a mirror for the soles.
    • Look for skin breakdown, calluses and pressure spots, and act on them early.
    • Bring a current, complete medicine list to every visit.
    • Report new weakness, new falls or a fast change right away. Do not wait for the next scheduled visit.

    Regenerve in the St. Louis region

    Regenerve treats peripheral neuropathy for patients across the St. Louis region, Missouri and Illinois, including Edwardsville, Glen Carbon, Collinsville, Troy and Maryville. The clinic is at 4477 Woodson Rd #104, St. Louis, MO 63134, minutes from St. Louis Lambert International Airport. Call (314) 886-5739 or text (314) 886-5902, or email info@regenerve.com.

    Your next step

    If you have kidney disease and nerve symptoms, take the free five-question Nerve Damage Score. It shows which group of causes most likely applies to you. Your answers guide what we check first.

    Frequently asked questions

    How often does neuropathy occur in chronic kidney disease?

    It depends a lot on whether you count symptoms or nerve testing. One Indian hospital study looked at 200 adults with predialysis CKD. Prevalence was 45% based on symptoms and 90% on electrophysiological testing.1 Part of that gap is small-fiber injury that routine testing under-counts. See small fiber neuropathy symptoms and testing.

    Does it get worse as kidney function declines?

    That is the pattern reported. A cross-sectional study looked at 105 adults with CKD in Amritsar. Neuropathy prevalence rose from 55% in Stage 3 to 84.8% in Stage 5.2 Our workup, including on-site electrodiagnostic testing, is on the neuropathy services page.

    Why do my feet burn at night if the problem is my kidneys?

    Burning at night usually points to small-fiber damage. Small fibers can be affected while routine nerve conduction testing still looks close to normal. See burning feet and nerve pain.

    Could something other than my kidney disease be causing this?

    Often, yes. A nutrient shortage is one of the most common added causes in this group, and it can be fixed once it is found. See functional B12 deficiency and neuropathy.

    What are the symptoms of uremic neuropathy?

    People describe burning, numbness, electric-shock feelings or less feeling. It usually starts in the feet and usually on both sides. Burning and pain at night point to small nerve fibers. Numbness, less vibration sense and weaker protective feeling point to large fibers, and that is what affects balance. Many people show nerve changes on testing before they notice any symptoms at all.3

    Can kidney disease cause tingling in the feet?

    Yes. Nerve injury from advanced kidney disease usually starts in the feet, on both sides. It is also often there before it is felt. One study looked at 200 adults with predialysis CKD. By symptoms, 45% had neuropathy. But 90% showed it on nerve testing.1 Diabetes, low nutrients and medicines often overlap in this group. So tingling deserves a full search for every cause.

    Is there a test for uremic neuropathy?

    Yes. EMG and nerve conduction studies, done on site, show which nerves are affected. They often find neuropathy before symptoms do. In one cohort of children with stage G5 CKD, testing found neuropathy in 45%, including 13% with no symptoms.3 A near-normal study does not rule out small fiber injury and does not name the cause. So we read results alongside your history, exam and metabolic review.

    Can uremic neuropathy be reversed?

    We do not promise nerve regeneration, reversal or a cure. When nerve injury has built up over years of advanced kidney disease, the honest goals are less ongoing injury, better day-to-day function and safer walking. That is why the workup hunts for causes that can still be fixed, such as a nutrient shortage. It is also why any nutrition or metabolic change is planned with your kidney team.

    Sources

    1. Jasti DB, Mallipeddi S, Apparao A, Vengamma B, Sivakumar V, Kolli S, “A Clinical and Electrophysiological Study of Peripheral Neuropathies in Predialysis Chronic Kidney Disease Patients and Relation of Severity of Peripheral Neuropathy with Degree of Renal Failure,” Journal of Neurosciences in Rural Practice, 2017;8(4):516-524, doi:10.4103/jnrp.jnrp_186_17, https://ruralneuropractice.com/a-clinical-and-electrophysiological-study-of-peripheral-neuropathies-in-predialysis-chronic-kidney-disease-patients-and-relation-of-severity-of-peripheral-neuropathy-with-degree-of-renal-failure/
    2. Singh P, et al., “Electrophysiological Characterization and Stage-Dependent Progression of Uremic Neuropathy in Chronic Kidney Disease,” Annals of Medicine and Medical Sciences, published May 21, 2026, Vol. 05 (2026), pages 707-711, https://ammspub.com/index.php/amms/article/view/579
    3. Yahyaoui A, Gammoudi N, Nouir S, Mabrouk S, Ghali H, Abroug S, Sakly G, “Prevalence of uremic neuropathy and the effect of dialysis in children with end-stage renal disease: A cohort study,” PLOS One, November 25, 2025, doi:10.1371/journal.pone.0337696, https://journals.plos.org/plosone/article?id=10.1371/journal.pone.0337696
    4. U.S. Food and Drug Administration, “QUTENZA (capsaicin) 8% topical system — prescribing information,” label effective July 7, 2026, via DailyMed, https://dailymed.nlm.nih.gov/dailymed/drugInfo.cfm?setid=3ffbbcb0-ad93-4f15-bb38-5da76a71c735
  • The Slow Poison in Your Bloodstream: How Heavy Metals Damage Your Nervous System

    The Slow Poison in Your Bloodstream: How Heavy Metals Damage Your Nervous System

    Lead, arsenic and mercury damage nerves in three ways. They jam the sulfur sites enzymes need, drain glutathione, and choke the cell’s energy production. Suspect them when an unexplained neuropathy keeps getting worse and there is a possible exposure from work, water, old plumbing or an imported product.

    Some causes of neuropathy make themselves known. Heavy-metal poisoning does the opposite. It builds up quietly, often over years, from sources a person may never link to their symptoms. These include old plumbing, tainted water, some jobs, and some imported products. By the time nerve damage shows up, the exposure may have gone on a long time. This article explains how metals like lead, arsenic, and mercury injure the nervous system and when to suspect them. Just as important, it explains why the popular world of aggressive “detox” can do more harm than the metals themselves.

    How do heavy metals damage nerves?

    Heavy metals damage nerves in a few overlapping ways. They disrupt essential enzymes by latching onto the sulfur sites the enzymes need to work. That jams the cell’s machinery. They deplete glutathione, the body’s master antioxidant, leaving nerves defenseless against oxidative stress. And they interfere with mitochondrial energy production, starving the energy-hungry nerve of the fuel it needs. The nervous system uses a lot of energy and has long, exposed fibers. So it is among the tissues most sensitive to this harm.

    Which heavy metals cause neuropathy?

    Lead. Lead is a classic cause of peripheral neuropathy. It has long been tied to a pattern that hits strength most (weakness, sometimes wrist drop). Exposure can come from old lead paint and pipes, and from some jobs (battery work, smelting, construction, radiator repair). It can also come from tainted soil and some traditional remedies and imported goods.

    Arsenic. Arsenic causes a painful sensory neuropathy that can look like other neuropathies that hit the longest nerves first. It often comes with telltale skin changes. Sources include tainted groundwater (a significant issue in some regions), some pesticides, and industrial processes.

    Mercury. Mercury affects both the nerves of the limbs and the brain and spinal cord. Sources include certain fish (methylmercury), some industrial exposures, and older dental or medical materials.

    Thallium and others. These are less common but notable causes of severe neuropathy. Hair loss is sometimes a clue.

    When should you suspect heavy metal poisoning?

    Heavy-metal neuropathy is worth considering when there is a possible exposure history. That means a job, hobby, water source, or product that could carry the metal. It matters most when the neuropathy is otherwise unexplained, is getting worse, or comes with whole-body clues (stomach symptoms, anemia, skin or nail changes, memory or thinking complaints). The history is the single most important guide. Without a reason to suspect exposure, scattershot testing tends to create more confusion than clarity.

    How do you test for heavy metals in neuropathy?

    When exposure is possible, testing should be targeted and appropriate to the specific metal. Different metals need different samples and timing. For instance, some are best checked in blood for recent exposure. Others are checked in urine, or with provoked testing under careful supervision. Here a clinician who knows toxicology should read the results. Normal ranges, sample types, and the meaning of results all depend on the metal and the exposure timeline.

    Is heavy metal detox or chelation safe?

    This part deserves a blunt warning. The internet is full of “heavy-metal detox” plans: supplements, cleanses, and chelation regimens sold for everything from fatigue to neuropathy. Many are unproven, some are useless, and a few are truly dangerous. Aggressive or poorly supervised chelation can push metals into sensitive tissues. It can cause serious salt-balance and kidney problems, and it has been linked to harm. Chelation therapy has real, specific medical uses for confirmed significant poisoning. But it is a medical treatment with real risks, not a wellness product. It should only ever be done under qualified medical supervision, after proper testing confirms a treatable load.

    The responsible approach is the opposite of a generic cleanse. Find and remove the source of exposure. Confirm the specific metal with proper testing. Support the body’s own clearing pathways (including glutathione levels) sensibly. And save chelation for the specific, confirmed cases where medical evidence supports it.

    Where this fits in the bigger picture

    Heavy metals are one of the toxic causes checked in a full root-cause neuropathy workup, along with medicines, alcohol, and mold. As with the others, the value of finding a metal link is that removing the exposure can stop ongoing damage. But it has to be identified correctly first. That is why a history-guided, targeted workup matters so much here.

    Frequently asked questions

    Could heavy metals be causing my neuropathy without my knowing?

    It is possible if you have a real exposure source. Buildup is slow and silent, so the link is easy to miss. That is why exposure history is key.

    Should I get a heavy-metal panel just to check?

    Testing is most useful when guided by a possible exposure. Untargeted “panels,” especially provoked urine tests sold online, are easy to misread. Discuss the right testing with a clinician.

    Are detox supplements or cleanses a good idea?

    Generally no. Many are unproven, and aggressive chelation carries real risks. Real treatment for confirmed poisoning is a supervised medical process, not a store-bought cleanse.

    What’s the most important first step?

    Finding and removing the source of exposure. No treatment works while the exposure goes on.

    What are the symptoms of heavy metal neuropathy?

    It depends on the metal. Lead tends to cause weakness, sometimes a wrist drop. Arsenic causes a painful sensory neuropathy, often with skin changes. Mercury hits both the nerves of the limbs and the brain. Thallium can cause severe neuropathy with hair loss. Watch for whole-body clues too: stomach symptoms, anemia, skin or nail changes, and trouble with memory or thinking.

    Where does heavy metal exposure come from?

    Lead comes from old paint and pipes, tainted soil, some traditional remedies and imported goods. It also comes from jobs like battery work, smelting, construction, and radiator repair. Arsenic comes from tainted groundwater, some pesticides, and industrial processes. Mercury comes from certain fish, some industrial work, and older dental or medical materials. The exposure is usually slow and easy to miss.

    Can heavy metal nerve damage be stopped?

    Yes, if the right metal is found. Once the metal is correctly identified and the source of exposure is removed, the ongoing damage can stop. That is why the workup starts with your exposure history and targeted testing, not a generic cleanse or an untargeted panel.

    Key takeaways

    • Heavy metals injure nerves by disrupting enzymes, draining glutathione, and hurting the mitochondria.
    • Lead, arsenic, and mercury are the main offenders. Each has its own telltale patterns and sources.
    • Suspicion should come from a real exposure history. Testing must be targeted and read by an expert.
    • Removing the source is the essential first step.
    • Unproven “detox” and unsupervised chelation can be harmful. Chelation is a supervised medical treatment for confirmed poisoning only.

    This article is educational and is not a substitute for evaluation, diagnosis, or treatment by a physician. Individual results vary. Do not attempt detoxification or chelation without qualified medical supervision. Take the free Nerve Damage Score or call (314) 886-5739 or text (314) 886-5902.

    References

    1. Agency for Toxic Substances and Disease Registry (ATSDR). Toxicological Profiles: Lead, Arsenic, Mercury.
    2. Thomson RM, Parry GJ. Neuropathies associated with excessive exposure to lead. Muscle Nerve. 2006.
    3. Rao DG, et al. Arsenic-induced peripheral neuropathy. Pract Neurol / review.
    4. Kern JK, et al. Cautions regarding chelation and unproven detoxification; glutathione and heavy-metal toxicity (review).

    Find out what is driving your nerve pain

    The free, five-question Nerve Damage Score takes about two minutes and tells you which terrain failure is most likely behind your symptoms.

    Get My Free Nerve Damage Score Get Info

    Or call or text us.

  • Alcohol and Nerve Damage: Why Your Feet Burn — and How Recovery Actually Works

    Alcohol and Nerve Damage: Why Your Feet Burn — and How Recovery Actually Works

    Alcohol burns the feet two ways at once. Acetaldehyde poisons the longest nerves first. Heavy drinking also strips out thiamine (vitamin B1), the fuel nerves need for energy and repair. Both causes can be reversed. Recovery comes from cutting alcohol safely and putting back thiamine and the other B vitamins.

    Alcohol nerve damage is common and often missed. The good news is that it is one of the neuropathies most likely to get better when it is treated the right way. It also calls for straight talk, not judgment. This article covers the two ways alcohol hurts nerves, why the feet burn, and what real recovery takes. It also has a key safety note on how not to quit.

    How does alcohol damage your nerves?

    Alcohol hits the nerves in the arms and legs in two ways at the same time. That is part of why the damage can be serious.

    Direct toxicity. Alcohol and its main breakdown product, acetaldehyde, are poison to nerve tissue. Acetaldehyde is a harsh chemical that damages cell parts and proteins. Over time it injures the nerve fibers and the machinery that keeps them healthy. This poison is thought to help cause a length-dependent axonal neuropathy. That means damage that starts at the ends of the longest nerves and works inward. The result is the classic burning, tingling, and numbness in the feet.

    Nutritional depletion. Heavy drinking drains the body of key nutrients, above all thiamine (vitamin B1). Alcohol gets in the way of how the body absorbs, stores, and uses thiamine. Heavy drinking also often replaces real food. Nerves need thiamine to make energy, so a shortage causes neuropathy on its own. Low thiamine can also cause Wernicke’s encephalopathy, a brain emergency. Other B vitamins and nutrients often run low too.

    So alcohol neuropathy with burning feet is usually both at once: nerves poisoned directly and starved of the nutrients they need to work and repair.

    Why is alcoholic neuropathy often missed?

    Alcohol neuropathy can creep in slowly. It gets blamed on aging or on diabetes (which often comes with it), or it gets brushed off. People may not want to say how much they drink, and doctors may not ask. So a treatable, partly reversible neuropathy goes untreated. An honest talk about drinking is a key part of any workup for unexplained neuropathy. The point is not blame. The point is to find a cause you can act on.

    Will neuropathy get better if you stop drinking?

    The good news is that alcohol neuropathy has real room to improve, because both of its causes can be reversed. Recovery rests on three pillars.

    1. Reducing alcohol exposure. This is the foundation. The poison damage cannot heal while drinking goes on. But how you cut back matters a great deal (see the safety note below).

    2. Repleting nutrients, especially thiamine. Putting back thiamine and the other missing B vitamins gives nerves the helpers they need for energy and repair. With a big shortage or heavy drinking, thiamine often comes first. In some medical settings it is given before glucose to avoid causing harm. That detail shows why a doctor should guide this step.

    3. Repairing the terrain. Stopping the damage and replacing nutrients is not the whole job. The injured nerve also needs the same support any healing nerve needs: care for mitochondrial function (the cell’s power plants), inflammation, and overall metabolic health. Nerve tissue repairs slowly, so improvement comes over months.

    Is it dangerous to stop drinking suddenly?

    Here is a key warning every honest article must include. If your body depends on alcohol, stopping abruptly can be dangerous. Alcohol withdrawal can cause seizures and a deadly condition called delirium tremens. If you are dependent, cut back or stop with medical support. That makes it safer and more likely to work. This is not a reason to keep drinking. It is a reason to get help doing it safely. If you drink a lot, the first step is to talk with a doctor about a plan. Do not quit cold turkey alone.

    Help is out there, and asking for it is a sign of strength, not weakness. You can truly recover from both the dependence and the neuropathy.

    Where this fits

    Alcohol is one of the toxic causes checked in a full neuropathy workup. It often overlaps with poor nutrition and with diabetes, so finding it helps complete the picture. It is also one of the more rewarding causes to treat, because real recovery is often possible.

    Frequently asked questions

    Can alcoholic neuropathy be reversed?

    It has real room to improve when you cut alcohol and replace nutrients, especially thiamine. Recovery is slow, though, and may be partial when the damage is advanced.

    How much alcohol causes neuropathy?

    There is no single cutoff. Risk rises with how much and how long you drink heavily, and poor nutrition makes it worse. Having diabetes too lowers your margin further.

    Should I just quit cold turkey?

    If you drink heavily or are dependent, no. Stopping all at once can set off dangerous withdrawal. Cut back or stop with medical support so you do it safely.

    Which nutrient matters most?

    Thiamine (B1) is central. But other B vitamins and nutrients often run low too, so the refill usually covers more than thiamine alone.

    What are the first symptoms of alcoholic neuropathy?

    Burning, tingling and numbness in the feet usually come first. Alcohol and its breakdown product, acetaldehyde, damage the longest nerves at their far ends. The injury then works inward. The change can be slow enough to be blamed on aging or diabetes, so tell your clinician honestly how much you drink.

    How long does alcoholic neuropathy take to heal?

    Months, not weeks. Nerve tissue repairs slowly. Improvement comes over months once you drink less and replace thiamine and the other B vitamins. Acting early saves more function, and recovery may be partial when the damage is advanced. The healing nerve also needs support for mitochondrial function, inflammation and overall metabolic health.

    Can alcohol damage the brain as well as the nerves?

    Yes. The same thiamine shortage that starves the nerves in your feet can cause Wernicke’s encephalopathy, a medical emergency in the brain. That is one reason thiamine often comes first in heavy drinkers. In some medical settings it is given before glucose to avoid causing harm. Take this step under a doctor’s care, not on your own.

    Is it alcoholic neuropathy or diabetic neuropathy?

    It can be both. Diabetes often comes with heavy drinking. Alcohol nerve damage often gets blamed fully on diabetes or on age. The two can look alike in the feet, so an honest talk about drinking belongs in every workup for unexplained neuropathy. Finding alcohol as a cause matters, because it is one of the causes most likely to get better.

    Key takeaways

    • Alcohol hurts nerves two ways at once: direct toxicity (acetaldehyde) and low thiamine and other nutrients.
    • The result is usually a length-dependent neuropathy with burning, tingling, and numb feet.
    • Recovery rests on drinking less, putting back thiamine and other nutrients, and supporting nerve repair.
    • Improvement is real but slow. Acting early saves more function.
    • If you are dependent, never stop all at once. Withdrawal can be dangerous. Stop with medical support.

    This article is educational and is not a substitute for evaluation, diagnosis, or treatment by a physician. Individual results vary. If you drink heavily, do not stop abruptly without medical guidance. Take the free Nerve Damage Score or call (314) 886-5739 or text (314) 886-5902. If you need support for alcohol use, help is available — talk with a physician or call the SAMHSA National Helpline at 1-800-662-4357.

    References

    1. Chopra K, Tiwari V. Alcoholic neuropathy: possible mechanisms and future treatment possibilities. Br J Clin Pharmacol. 2012;73(3):348–362.
    2. Koike H, et al. Alcoholic neuropathy. Curr Opin Neurol / Muscle Nerve.
    3. Sechi G, Serra A. Wernicke’s encephalopathy: new clinical settings and recent advances. Lancet Neurol. 2007;6:442–455.

    Find out what is driving your nerve pain

    The free, five-question Nerve Damage Score takes about two minutes and tells you which terrain failure is most likely behind your symptoms.

    Get My Free Nerve Damage Score Get Info

    Or call or text us.

  • Mystery Neuropathy and Exhaustion? The Mold and Mycotoxin Question

    Mystery Neuropathy and Exhaustion? The Mold and Mycotoxin Question

    Mycotoxins from water-damaged buildings have three plausible routes to your nerves and your energy: damage to the mitochondria (the cell’s power plants), inflammation in the nervous system, and oxidative stress. Plausible is not proven. So the workup rules out the common, treatable causes of neuropathy first. Then it weighs a believable mold exposure with proven tools.

    This topic calls for both openness and honesty. Some patients with unexplained neuropathy and deep fatigue trace their symptoms to time in a water-damaged building. Mold and its toxins are a real area of scientific and medical interest. At the same time, “mold illness” is one of the more disputed subjects in medicine. It gets dismissed on one side and overdiagnosed on the other. This article aims for the middle. It covers what mycotoxins are and the plausible ways they could affect nerves and energy. And it shows how to approach a workup carefully, without swallowing every claim.

    What are mycotoxins?

    Mold is a type of fungus. Some molds make mycotoxins, toxic compounds that can taint the environment. This is most common in water-damaged buildings, where mold grows on damp materials. Mycotoxins are well known to be harmful in certain settings. Tainted food is a known cause of illness in people and animals, and exposures at work are studied. The debate is not whether mycotoxins can be toxic. They can. The debate is how often, and how much, indoor mold exposure causes the specific many-symptom syndromes some patients and practitioners blame on it.

    How could mold affect your nerves and energy?

    The ways mycotoxins could affect the nervous system make biological sense. That is part of why the topic is taken seriously, even amid the dispute.

    Mitochondrial toxicity. Some mycotoxins can impair mitochondria in lab settings. Nerves depend heavily on energy. So anything that undercuts mitochondrial energy could, in principle, add to nerve problems. It could also add to the deep fatigue that often comes with these cases, the “drained energy” theme.

    Neuroinflammation. Mycotoxins and mold exposure can trigger immune and inflammatory responses. Long-term inflammation in the nervous system is a known contributor to nerve problems. That offers another plausible route from exposure to symptoms.

    Oxidative stress. Like other toxins, mycotoxins can raise oxidative stress and drain antioxidant defenses. That adds to the strain on cells in vulnerable tissues.

    These are reasons it is plausible. They are not proof that a given patient’s neuropathy is caused by mold. That is an important line to keep in view.

    Is chronic mold illness proven?

    Honesty matters here. The idea of a long-term, many-system illness from indoor mold exposure (sometimes called “chronic inflammatory response syndrome”) is not universally accepted in mainstream medicine. Some of the testing and treatment sold for it is unproven or driven by sales. Then again, dismissing every patient with real symptoms and a real water-damaged-building exposure does them a disservice. The sound medical stance is to take the exposure history and symptoms seriously. Evaluate carefully with proven tools. Rule in or out the well-known causes of neuropathy first. And avoid both knee-jerk dismissal and unproven, costly protocols.

    How is mold exposure evaluated in someone with neuropathy?

    Take someone with unexplained neuropathy, marked fatigue, and a believable exposure to a water-damaged place. A sensible, careful approach has several parts. First, a thorough standard neuropathy workup to find or rule out the common, well-known causes: metabolic, nutritional, toxic, autoimmune, and mechanical. These are more common and more clearly treatable, and blaming mold should never cut that search short. Second, an honest environmental assessment. Is there documented water damage and mold in the home or workplace? Removing or cleaning up a truly tainted space makes sense no matter how the diagnostic debate turns out. Third, supporting cellular energy and reducing oxidative stress through sound, evidence-based steps: good nutrition, mitochondrial helper nutrients, sleep, and managing inflammation. These are low-risk and broadly helpful. And all along, skepticism toward unvalidated tests and proprietary “detox” protocols that promise to diagnose and cure mold illness. Many of them lack solid support.

    Where this fits

    Mold and mycotoxins sit in the toxic group of neuropathy causes, along with heavy metals, medicines, and alcohol. The guiding rule mirrors the heavy-metals discussion. Find and remove real environmental exposure, evaluate carefully, and support the body’s resilience. Keep a clear eye on the difference between a plausible mechanism and proven cause. And steer away from the unproven commercial fringe.

    Frequently asked questions

    Can mold really cause neuropathy?

    Mycotoxins are truly toxic and can affect mitochondria and inflammation, so a role is biologically plausible. But indoor-mold illness is a debated area. Other, better-proven causes should be checked first.

    For the better-established causes to rule out first, read Peripheral Neuropathy: The 11 Hidden Drivers Your Doctor Missed.

    Should I get mycotoxin testing?

    Be cautious. Much of the testing sold is unproven and easy to misread. Focus first on a thorough standard workup and, where it fits, a real environmental check of the building.

    Is remediating my home worthwhile?

    If there is documented water damage and mold, dealing with it makes sense for general health, no matter how the diagnostic debate turns out. Removing a real exposure is low-risk and reasonable.

    What about mold “detox” protocols?

    Many are unproven and driven by sales. Put evidence-based support first (nutrition, sleep, mitochondrial helper nutrients, managing inflammation). Avoid costly, unproven regimens.

    Can mold exposure cause fatigue?

    It is plausible. Some mycotoxins impair mitochondria in lab settings, and mitochondria make the energy that nerves and the rest of the body run on. That could add to the deep fatigue that often comes with these symptoms. Plausible is not proven for any one person, so the common, treatable causes get checked first.

    Where does toxic mold exposure come from?

    Most often from water-damaged buildings, where mold grows on damp materials and some species release mycotoxins into the building. Tainted food is a separate, known cause of mycotoxin illness, and some jobs carry exposure. The first practical question is whether there is documented water damage and mold in your home or workplace.

    What should be ruled out before blaming mold for neuropathy?

    The well-known causes: metabolic, nutritional, toxic, autoimmune and mechanical. They are more common and more clearly treatable. So a standard neuropathy workup comes first, and blaming mold should never cut that search short. Mold and mycotoxins then sit in the toxic group, along with heavy metals, medicines and alcohol.

    Key takeaways

    • Some molds make mycotoxins that are truly toxic. Indoor-mold illness syndromes, however, are disputed in medicine.
    • Plausible routes include damage to the mitochondria, inflammation in the nervous system, and oxidative stress.
    • The evidence for long-term, many-system mold illness is not settled. Avoid both dismissal and overdiagnosis.
    • Check the well-known neuropathy causes first, and look at the environment realistically.
    • Be skeptical of unproven testing and proprietary “detox” protocols. Favor low-risk, evidence-based support.

    This article is educational and is not a substitute for evaluation, diagnosis, or treatment by a physician. Individual results vary. Take the free Nerve Damage Score or call (314) 886-5739 or text (314) 886-5902.

    References

    1. World Health Organization. WHO Guidelines for Indoor Air Quality: Dampness and Mould. 2009.
    2. Institute of Medicine (US). Damp Indoor Spaces and Health. National Academies Press; 2004.
    3. Empting LD. Neurologic and neuropsychiatric syndrome features of mold and mycotoxin exposure. Toxicol Ind Health. 2009. (Note: represents one side of a contested literature.)
    4. Bennett JW, Klich M. Mycotoxins. Clin Microbiol Rev. 2003;16:497–516.

    Find out what is driving your nerve pain

    The free, five-question Nerve Damage Score takes about two minutes and tells you which terrain failure is most likely behind your symptoms.

    Get My Free Nerve Damage Score Get Info

    Or call or text us.