Category: Nutritional & Digestive Drivers

  • B12 Deficiency and Burning Feet: When Your Stomach Is the Cause

    B12 Deficiency and Burning Feet: When Your Stomach Is the Cause

    B12 deficiency can cause burning, tingling and numb feet. One of the most overlooked reasons is a stomach that has quietly stopped absorbing the vitamin. If your feet burn and no one has found a cause, ask for more than one B12 level. Ask for methylmalonic acid, both stomach antibodies, iron studies and a medication review.

    People with burning feet get sent to look at their spine, their blood sugar or their shoes. Almost nobody gets sent to look at their stomach. Yet the vitamin your longest nerves need cannot enter the body without a protein the stomach lining makes. That chain is the subject of Chapter 6 of The Angry Gut, the new book from Dr. Gurpreet Singh Padda, MD, MBA, MHP, and coauthor Ami Michelle Grimes (announced here).

    How can a stomach problem make my feet burn?

    Think of B12 as a package that needs an escort. Stomach acid frees it from food. Intrinsic factor, made by the parietal cells of the stomach lining, grabs it and carries it the full length of the small bowel to a receptor at the very end. No escort, no delivery. Only about 1% of the vitamin slips in without that help.1

    The nerves that run to your toes are the longest in the body. They sit at the far end of the longest supply line. So they are the first to fail when supply runs short. That is why a B12 problem so often starts in both feet as numbness, pins and needles or burning. Then it climbs toward the calves.

    Two things destroy that lining. One is an immune attack on the parietal cells. The other is a long-running H. pylori infection. Either one causes atrophic gastritis. When the autoimmune form causes B12 deficiency, it is called pernicious anemia.

    Why was I never told my stomach could be involved?

    Because the name points everyone at the wrong test. “Pernicious anemia” suggests a blood-count problem. A 2025 perspective on the English national guideline notes that anemia is present in only 15% to 20% of pernicious anemia diagnoses.2

    In the chapter, I walked past the four years before this diagnosis. Those were the years when the lab work kept coming back fine. That was the wrong place to stop. The stomach fails in an order, and B12 is near the end of it.

    • Iron usually goes first. Sometimes the damage sits in the upper, acid-making part of the stomach. Then up to half of patients run low on iron, often well before B12 drops.3
    • It is rarely one nutrient. One center tracked 122 patients diagnosed by biopsy. Of those, 76 were short on at least one of B12, iron, vitamin D or folate, and 52 were short on more than one.4
    • The wait is long. The median delay to diagnosis in the autoimmune gastritis literature is 14 months.4
    • The lining does not wait with you. A prospective study followed 270 patients. The stomach tissue of every one of them got worse over time, usually within three years. None got better on its own.4

    Who is most likely to have a stomach-driven B12 problem?

    The people already at risk for nerve damage carry the highest odds.

    • Type 1 diabetes. The risk of autoimmune gastritis runs about three to five times that of the general public.4
    • Thyroid disease. Autoimmune thyroiditis shows up in 36% to 44% of people with autoimmune gastritis. Turned around, about 40% of people with autoimmune thyroid disease have this kind of stomach atrophy.4 If you have Hashimoto’s and burning feet, both belong in the same talk. See how thyroid function affects your nerves.
    • Long-term metformin. In the Diabetes Prevention Program, adults at high risk for type 2 diabetes were randomized to metformin (1,073 people) or placebo (1,082). At five years, low or borderline-low B12 (at or below 298 pg/mL) showed up in 19.1% on metformin. On placebo it was 9.5%. The extra neuropathy on metformin showed up only in the people whose B12 had fallen low.5 Never stop metformin on your own. Ask for the B12 workup instead. More in how statins and metformin can affect nerve health.
    • Daily acid blockers. A large study compared patients with and without B12 deficiency. People taking more than 1.5 proton pump inhibitor pills a day had nearly double the odds of B12 deficiency (odds ratio 1.95).6
    • Weight-loss surgery. A Portuguese hospital tracked 505 patients in a row. At twelve months, B12 deficiency ran 16.74% after gastric bypass. After sleeve gastrectomy it was 0.93%.7 See nerve damage after stomach or bowel surgery.

    Follow the money and the list stops looking random. We subsidize cheap calories. The calories cause the diabetes. The diabetes earns the metformin. And the metformin drains the vitamin while one blood test keeps saying all is fine. None of that is the patient’s failure.

    What should I have measured if my feet burn?

    A single B12 level tells you how much vitamin is in the blood. It does not tell you whether your nerves are getting it (see why a normal B12 can miss a deficiency). Bring this fuller list to your visit.

    1. Serum B12, read against the right lines. In American primary care, below 180 pg/mL is diagnostic and 180 to 350 pg/mL is borderline.8
    2. Methylmalonic acid if you land in that borderline band. It rises when B12 fails inside the cell. Kidney problems, dehydration, low thyroid and bacterial overgrowth in the small bowel can also raise it. So it has to be read with those in mind.9
    3. Both stomach antibodies, together. Anti-parietal cell and anti-intrinsic factor antibodies each miss cases on their own. Run as a pair, they reached 90% sensitivity and 95.7% specificity in a 2025 comparison of assays in autoimmune gastritis.10 A negative intrinsic factor antibody alone does not rule the problem out. It tends to turn positive later in the disease.3
    4. Ferritin and iron studies, including the oldest ones in your chart. A low iron years ago may have been the first clue.
    5. A medication history that counts years of metformin and daily dose, and years of acid blockers.
    6. Gastrin only after an acid blocker is stopped. A proton pump inhibitor can raise gastrin three to five times. That makes the result useless.2

    Do not wait for large red blood cells either. They are a late sign, and other problems can cause them too. Some patients low on B12 show nothing wrong on the blood count at all.9

    Does it change treatment if my stomach is the cause?

    Yes. When the absorption machinery is gone, a supplement bottle is a gamble on that 1% side door. England’s 2024 national guideline offers lifelong B12 shots when autoimmune gastritis is the cause or suspected cause, or after total gastrectomy.11 In the chapter’s case, a man whose stomach had almost no parietal cells left went on shots, not tablets. Eleven months later his walking was steadier. Some of what he lost did not come back. That is the cost of finding it late.

    A burning foot is a symptom. The cause may be hiding in the stomach, the medication list or the iron history. You can ask about all of them this week. You do not have to accept “idiopathic” while those questions are still open. The chapter’s free technical supplement is at theangrygut.com/chapter-6.

    Questions patients ask about B12 and burning feet

    Can low B12 cause burning feet even if I am not anemic?

    Yes. Anemia shows up in only a minority of pernicious anemia diagnoses. So a normal blood count does not rule out a B12 problem reaching the nerves. See what causes burning, numb or painful feet.

    I have diabetes. How do I know if it is B12 and not my blood sugar?

    You often cannot tell from symptoms alone, and both can be present. Metformin use, type 1 diabetes and thyroid disease all raise the odds of a B12 problem. That is why a diabetic patient with burning feet deserves B12 testing too. See diabetic peripheral neuropathy treatment in St. Louis.

    Should I just start taking a B12 supplement?

    Get tested first. If the stomach can no longer absorb the vitamin, a tablet depends on that 1% side door. England’s national guideline recommends shots instead when autoimmune gastritis is the cause. The form and dose are a medical decision. See nutritional deficiencies beyond B12.

    Sources

    1. Chan CQH, Low LL, Lee KH. Oral vitamin B12 replacement for the treatment of pernicious anemia. Frontiers in Medicine. 2016;3:38. doi.org
    2. Thain A, Hart K, Ahmadi KR. Addressing the gaps in the vitamin B12 deficiency 2024 NICE guidelines: highlighting the need for better recognition, diagnosis, and management of pernicious anaemia. European Journal of Clinical Nutrition. 2025;79(7):607–610. doi.org
    3. Shah SC, Piazuelo MB, Kuipers EJ, Li D. AGA clinical practice update on the diagnosis and management of atrophic gastritis: expert review. Gastroenterology. 2021;161(4):1325–1332. doi.org
    4. Rustgi SD, Bijlani P, Shah SC. Autoimmune gastritis, with or without pernicious anemia: epidemiology, risk factors, and clinical management. Therapeutic Advances in Gastroenterology. 2021;14:17562848211038771. doi.org
    5. Aroda VR, Edelstein SL, Goldberg RB, et al. Long-term metformin use and vitamin B12 deficiency in the Diabetes Prevention Program Outcomes Study. Journal of Clinical Endocrinology and Metabolism. 2016;101(4):1754–1761. doi.org
    6. Lam JR, Schneider JL, Zhao W, Corley DA. Proton pump inhibitor and histamine 2 receptor antagonist use and vitamin B12 deficiency. JAMA. 2013;310(22):2435–2442. doi.org
    7. Vieira de Sousa JP, Santos-Sousa H, Vieira S, et al. Assessing nutritional deficiencies in bariatric surgery patients: a comparative study of Roux-en-Y gastric bypass versus sleeve gastrectomy. Journal of Personalized Medicine. 2024;14(6):650. doi.org
    8. Patel H, McGuirk R. Vitamin B12 deficiency: common questions and answers. American Family Physician. 2025;112(3):294–300. pubmed.ncbi.nlm.nih.gov
    9. Harrington DJ, Stevenson E, Sobczyńska-Malefora A. The application and interpretation of laboratory biomarkers for the evaluation of vitamin B12 status. Annals of Clinical Biochemistry. 2024;62(1):22–33. doi.org
    10. Osmola M, Hémont C, Romańczyk M, et al. A comparative study of different assays for autoantibodies detection in patients with autoimmune gastritis. Journal of Translational Autoimmunity. 2025;10:100294. doi.org
    11. National Institute for Health and Care Excellence. Vitamin B12 deficiency in over 16s: diagnosis and management (NG239). 2024. nice.org.uk

    Find out what is driving your burning feet

    The free, five-question Nerve Damage Score takes about two minutes and points to the driver most likely behind your symptoms.

    Get My Free Nerve Damage Score Get Info

    Or schedule, call or text us.
  • Vitamin B6 toxicity as a cause of peripheral neuropathy

    Vitamin B6 toxicity as a cause of peripheral neuropathy

    Too much vitamin B6 can injure peripheral nerves, and the dose it takes is lower than most people assume. Health Canada’s safety review found a possible link between vitamin B6-containing non-prescription natural health products and peripheral neuropathy at daily doses of 10 mg or higher [1]. The catch is that no blood level settles the question, so this is found through your exposure history and symptom timeline, not a single lab result.

    It is also one of the drivers most easily missed, because patients do not describe it as a supplement problem. They describe burning, numbness or electric feelings in the feet. Every other neuropathy driver uses those same words.

    Key points

    • Pyridoxine toxicity causes a length-dependent, sensory-predominant axonal polyneuropathy [2]. In plain terms, it hits the longest nerves first and mostly affects feeling.
    • Health Canada found a possible risk signal at daily doses of 10 mg or higher. This was in non-prescription natural health products [1].
    • In a 261-patient cohort, plasma B6 level did not correlate with how bad the neuropathy was, so the number alone does not confirm or rule out the cause [2].
    • Toxic effects have been reported at normal multivitamin doses taken for years [3].
    • Neuropathy is a category, not a diagnosis. B6 excess can be one driver among several in the same person.

    How much vitamin B6 is too much?

    Health Canada reviewed vitamin B6-containing health products for a possible link to peripheral neuropathy. Published international cases at daily doses under 100 mg prompted the review. So did assessments from foreign regulators [1].

    The review found 17 cases of peripheral neuropathy (15 Canadian and 2 international). These patients were taking vitamin B6-containing non-prescription health products (14 cases) or vitamin B6-containing prescription drugs (3 cases) [1]. Fifteen of those 17 did not meet the criteria for further assessment. In the two that did, confounders (other possible causes) and missing clinical information limited the analysis, so a link could not be excluded rather than confirmed [1].

    Health Canada’s conclusion separates product types. It found a possible link for the non-prescription natural health products at daily doses of 10 mg or higher. It did not find enough evidence to establish a link for vitamin B6-containing prescription drugs [1]. Nine supporting articles in the scientific literature were reviewed alongside the case data [1].

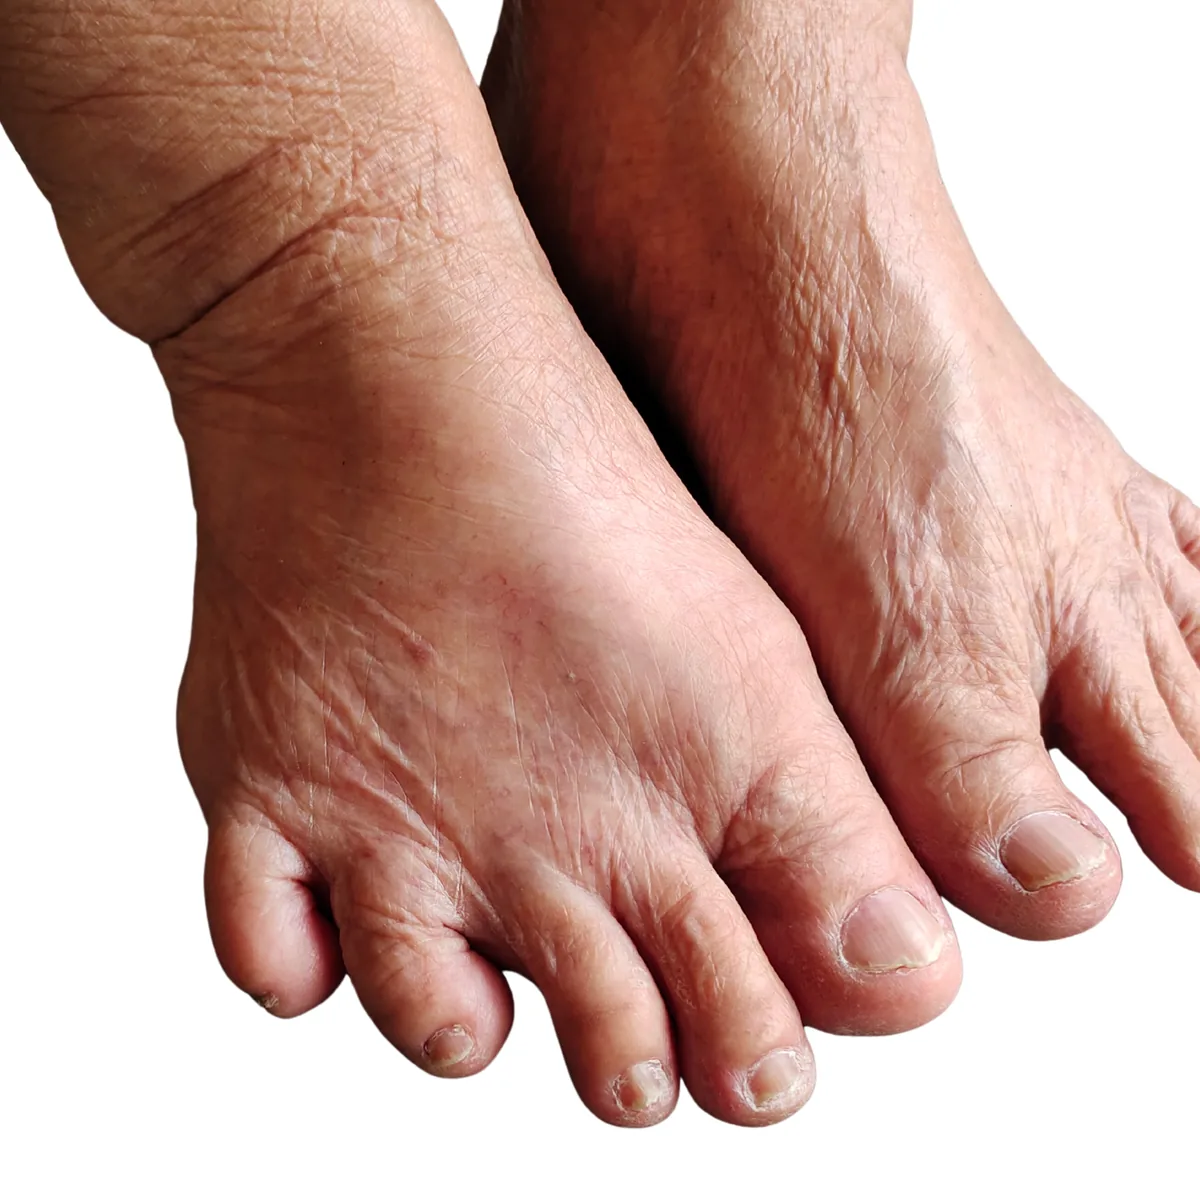
    Bare feet of an older adult showing dry skin, thickened toenails and bunion deformity, the appearance often seen alongside peripheral neuropathy of the feet

    Why a blood level does not settle it

    This is the part that surprises people. The Peripheral Neuropathy Research Registry enrolled 261 patients with chronic idiopathic axonal polyneuropathy. In them, plasma vitamin B6 level was not related to how severe the neuropathy was [2].

    A high plasma B6 level showed no link to nerve conduction study results. It showed no link to exam findings, including toe strength, vibration sense and deep tendon reflexes. It showed no link to patient-reported numbness or pain intensity [2]. The authors concluded that moderately elevated levels, even in the 100 to 200 µg/L range, were not associated with significantly worse signs or symptoms. Very few patients in the study were above 300 µg/L [2].

    So a mildly high number is not proof. A normal number does not rule it out. The exposure history and the timeline do more work than the lab test.

    Ordinary doses, taken long enough

    A published case report describes a 73-year-old man with three years of numbness and tingling in both legs that kept getting worse. He also had new lightheadedness and dizziness. He was taking a standard daily multivitamin supplying 6 mg of vitamin B6 [3].

    His serum B6 was 259.9 nmol/L against a reference range of 20 to 125 nmol/L. One month after stopping the multivitamin, he reported that the dizziness had resolved. The numbness and tingling had improved slightly [3]. One case is not a rule. But it is a reason to read the label and not assume a common product is harmless.

    How is vitamin B6 toxicity diagnosed?

    Exposure mapping

    We ask about every daily multivitamin, B-complex, energy formula and anything else that lists pyridoxine. We record the milligram amount and how long it has been taken. Then we line that up against when the symptoms started and how they progressed.

    Supplements are the category patients most often leave out of a medication history, because they do not think of them as drugs.

    Pattern mapping

    Small fiber involvement causes burning and changes in feeling. Large fiber involvement shows up as numbness, unsteadiness and lost position sense. Which pattern leads decides which testing is worth running.

    We do electrodiagnostic testing (EMG/NCS) on site. It measures large-fiber involvement. It can be normal in small fiber neuropathy, so a normal study does not close the file.

    The other drivers in the same room

    Excess B6 rarely comes alone. Metabolic injury, vitamin B12 deficiency, gluten-related mechanisms, chemo, alcohol and heavy metals all cause overlapping symptoms. Two drivers in one person is common. The full set is laid out in the hidden drivers of peripheral neuropathy.

    Videonystagmography (VNG) is a diagnostic test of inner-ear balance. We use it when unsteadiness is part of the picture. It is a test, not a treatment.

    When should B6 neuropathy symptoms be checked right away?

    Fast-worsening numbness, significant balance loss or new weakness should be checked promptly, not watched. So should changes in feeling that are starting to get in the way of walking.

    Waiting to see if it settles on its own is the most common reason people arrive later than they should have.

    How is vitamin B6 neuropathy treated?

    The first move is to cut back or stop the exposure and confirm whether anything else is adding to it. That is driver-level work. Nothing else in the plan takes its place.

    After that, the work is the terrain the nerve depends on. That means blood flow (perfusion) so oxygen reaches the nerve. It means the metabolic pathways that keep causing injury. It means the raw materials (substrates) repair needs. Class 4 photobiomodulation, class 3B cold laser and whole-body infrared are used as supporting parts matched to the clinical picture. They are not stand-alone answers.

    Orthobiologic injections (PRP and BMAC) are offered in selected situations. Qutenza (capsaicin 8% patch) is FDA-approved in adults for neuropathic pain from postherpetic neuralgia and from diabetic peripheral neuropathy of the feet. A clinician applies it in the clinic. It is repeated no more often than every three months.

    None of this is a promise of nerve regeneration or reversal. Recovery after a toxic exposure is variable and often partial.

    Frequently asked questions

    Can a daily multivitamin cause vitamin B6 toxicity?

    It has been reported. In a published case report, a 73-year-old man developed numbness and tingling in both legs that worsened over three years. He was taking a standard daily multivitamin. His serum B6 was 259.9 nmol/L against a normal range of 20 to 125 nmol/L. What matters is the pyridoxine amount on the label and how long it has been taken. We do the testing that sorts this out on site; see our services and on-site testing.

    Will a blood level tell me whether B6 is the cause?

    Not by itself. In 261 patients with chronic idiopathic axonal polyneuropathy, plasma B6 level was not related to how severe the neuropathy was. It was not related to exam findings or nerve conduction results either. Exposure history and symptom timeline carry more weight than a single number. See functional B12 deficiency and neuropathy.

    What do the symptoms look like?

    Pyridoxine toxicity is known to cause a length-dependent, sensory-predominant axonal polyneuropathy (damage that starts in the longest nerves and mostly hits feeling), so numbness, burning and changes in feeling that start in the feet are the usual picture. That pattern overlaps with several other drivers, which is why the exposure history matters. See small fiber neuropathy symptoms and testing.

    What should I ask a clinic that is evaluating me for this?

    Ask whether they will check every supplement label for pyridoxine. Ask how they will build the exposure timeline. Ask what testing they will use to measure the nerve involvement. A workup that skips the supplement bottle is not a workup. See how to choose a neuropathy specialist.

    If I stop the supplement, will the symptoms go away?

    It is not that predictable. In the published case report, dizziness resolved one month after the multivitamin was stopped. The numbness and tingling improved slightly. Recovery varies, and no one should promise reversal. See peripheral neuropathy of the feet symptoms.

    Is B6 or B12 better for neuropathy?

    They are not two versions of the same fix. Too much vitamin B6 can itself injure peripheral nerves. Vitamin B12 deficiency is a separate driver of neuropathy. Both can cause the same burning and numbness in the feet, and two drivers in one person is common, so the workup checks for each one instead of adding another supplement on a guess.

    Which supplements contain vitamin B6?

    Look for pyridoxine on the label. It shows up in daily multivitamins, B-complex products, energy formulas and other products. Supplements are the category patients most often leave out of a medication history. Write down every product that lists it, the milligram amount and how long you have taken it. Bring that list to your visit.

    Can too much vitamin B6 cause dizziness?

    It has been reported. In a published case, a 73-year-old man taking a standard multivitamin with 6 mg of B6 had three years of numbness and tingling in both legs. He also had new lightheadedness and dizziness. One month after he stopped the multivitamin, the dizziness resolved. One case is not a rule, and unsteadiness has other causes, so balance testing may be part of the workup.

    Next step

    Did your symptoms start or get worse after you began a B-complex or multivitamin? That timeline is worth taking seriously. Five questions identify which driver is doing the most damage right now.

    Sources

    1. Health Canada. Summary Safety Review – Vitamin B6 Health Products – Assessing the Potential Risk of Peripheral Neuropathy. Drug and Health Products Portal, Government of Canada. Reviews conducted 2024-2025. https://dhpp.hpfb-dgpsa.ca/review-documents/resource/SSR1773147434487
    2. Stewart SL, Thomas S, Höke E, Simpson D, Singleton JR, Höke A. Vitamin B6 levels do not correlate with severity of neuropathy in chronic idiopathic axonal polyneuropathy. Journal of the Peripheral Nervous System. 2022;27(1):31-37. doi:10.1111/jns.12480. https://pubmed.ncbi.nlm.nih.gov/34931740/
    3. Paluszny A, Qiu S. Vitamin B6 toxicity secondary to daily multivitamin use: a case report. Cureus. 2023;15(11):e48792. doi:10.7759/cureus.48792. https://pmc.ncbi.nlm.nih.gov/articles/PMC10720370/
  • Nutritional deficiencies beyond B12 that damage peripheral nerves

    Nutritional deficiencies beyond B12 that damage peripheral nerves

    B12 is not the only nutrient whose absence damages peripheral nerves. A 2026 review in Current Nutrition Reports describes how a thiamine (vitamin B1) shortage causes conditions such as beriberi and Wernicke’s encephalopathy. It concludes that thiamine and B12 shortages are established risk factors for neuropathy. Vitamin B6 behaves differently: too much B6, not too little, is what correlates with nerve effects.1 That is why “it must be B12” is often the wrong starting guess. The practical work is naming which cause is active before anything is prescribed.

    The short version

    • Beyond B12 means B1 and B6 first. Too little thiamine and too much B6 are both known nerve problems.
    • More supplement is not the answer. With B6, more is the mechanism of injury.
    • Nutrition rarely acts alone. It sits alongside metabolic, autoimmune, toxic, and structural causes.
    • Absorption matters as much as intake. Alcohol use, weight-loss surgery, and metformin are all in the picture.
    • Idiopathic is not a stopping point. It usually means the active cause has not been named yet.

    Is B12 deficiency the only vitamin problem that causes neuropathy?

    Vitamin B12 deficiency is a real and important pathway. A cobalamin (B12) shortage impairs DNA building and myelin formation. That is why it causes nerve and brain problems.1 But it is one pathway among several.

    This matters because medicine that quiets the signal does not repair the wiring. If the cause is nutritional, metabolic, toxic, autoimmune, or structural, the nerve stays under stress while the symptom is managed.

    Which B vitamins besides B12 cause neuropathy?

    The common mistake is assuming a low vitamin is always the same vitamin. B-vitamin balance can fail in both directions. The direction changes what you should do next.

    Vitamin B1 (thiamine): shortage with real neurologic consequences

    A thiamine shortage causes conditions including beriberi and Wernicke’s encephalopathy.1 The practical point for nerves is that nutrition causes beyond B12 can be serious. They are not just a slightly abnormal number on a panel.

    Diet, alcohol use, poor absorption, and times of higher nutrient need all belong in the history, because they are what put thiamine at risk in the first place.

    Vitamin B6 (pyridoxine): excess is the nerve problem

    Here the direction flips. The review reports that too much pyridoxine (B6), not too little, correlates with nerve effects. It adds that the B6 link remains uncertain overall, but extra B6 carries a risk of nerve poisoning.1

    This is what a supplement-first approach tends to miss. If you take a high-dose B6 product, the nutrition part of your neuropathy may come from too much, not too little. Then the plan changes right away.

    Absorption and metabolism travel together

    Gut and metabolic problems disrupt how nutrients are absorbed and used. That is why nutrition is treated here as part of the whole workup, not as a one-time supplement fix.

    Who is most at risk for nutritional neuropathy?

    A 2026 review in Neurological Research and Practice describes polyneuropathy as a common nerve disorder that is becoming more frequent, especially among older people. It names B-vitamin deficiencies, prediabetes, diabetes mellitus, obesity, and treatment-induced neuropathies as key risk factors.2 It also notes that these factors often interact, which makes care harder.

    That is the real-world reason behind mapping causes. More than one is usually at work. Naming only the loudest one leaves the rest in place. Several of the causes that get overlooked are covered in our review of the hidden drivers behind peripheral neuropathy.

    What does vitamin deficiency neuropathy feel like?

    Timing and location give useful clues. An even pattern that hits the longest nerves first, toes first and then up the foot, points to a whole-body or metabolic cause, not a single local injury.

    Nutrition causes can also show small-fiber features: burning, hot-coal feelings, and symptoms that are worse at night. When the pattern and the lab results do not line up, that mismatch is itself a clue.

    Why standard testing can look unremarkable

    Standard nerve conduction studies measure the larger fibers. Someone with strong burning and normal-looking studies is not a contradiction. It is a limit of what that test was built to see.

    Medication, surgical, and medical history belong in the evaluation

    Some situations raise nutrition risk directly. The Current Nutrition Reports review notes that these shortages are still common in developing regions. In wealthier nations, alcohol abuse, weight-loss surgery, and metformin use increasingly drive them.1

    So the history has to cover medicines, gut and surgery history, and what you actually eat, not only the nerve symptoms. None of that is a reason to stop a prescribed medicine on your own.

    Chemotherapy and nutritional status together

    Chemotherapy can injure nerves directly, and nutrition levels often change during and after cancer treatment. When both are present, they are treated as two causes, not one.

    How we evaluate a suspected nutritional driver

    Neuropathy is rarely caused by blood sugar alone. It is rarely explained by a single lab value. The workup is built to decide which cause is doing the most damage right now.

    We do electrodiagnostic testing (EMG/NCS) on site. VNG (videonystagmography) is available as a test of inner-ear balance when dizziness or unsteadiness is part of the picture. It is a test, never a treatment. Metabolic and nutrition checks run alongside both.

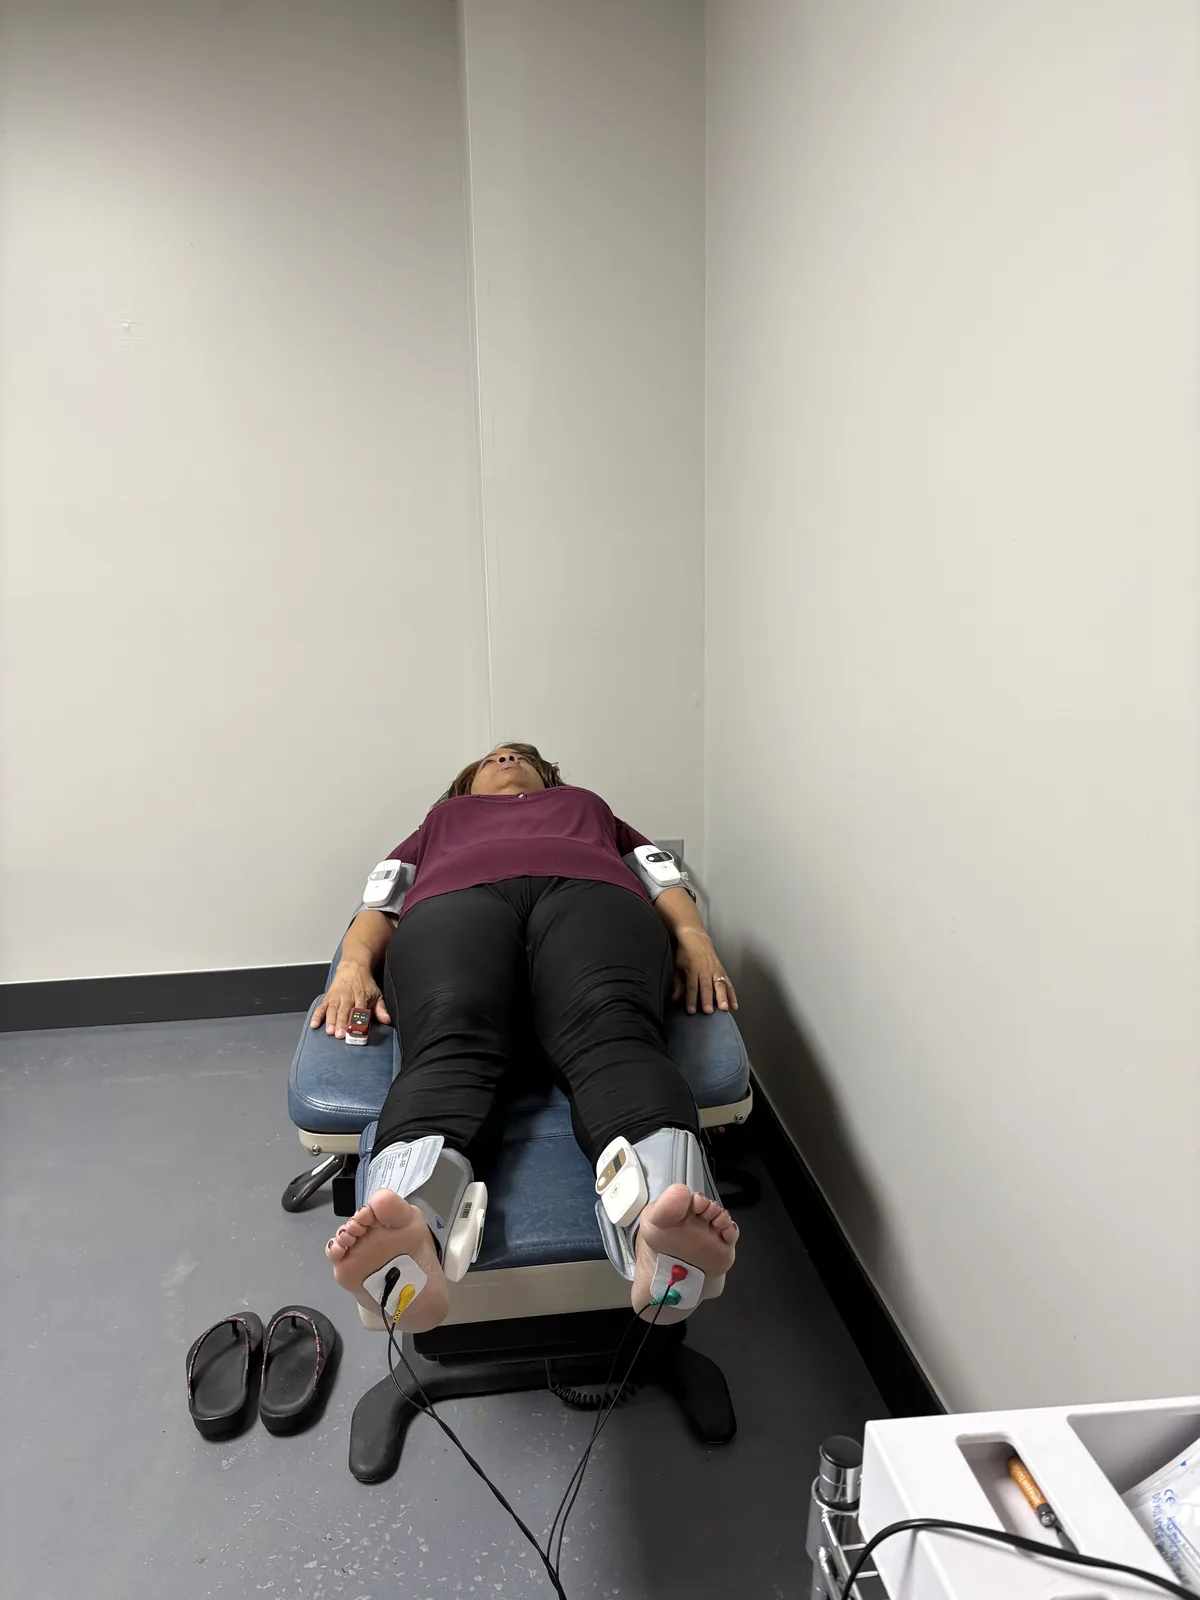
    Patient reclined for small-fiber and autonomic nerve testing, with sensor cuffs on both ankles and wrists, at Regenerve, 4477 Woodson Rd, St. Louis, MO 63134

    How is nutritional neuropathy treated?

    We do not promise nerve regeneration, reversal, or a cure. The work is cutting what is damaging the nerve and supporting the conditions in which function can improve.

    Depending on the cause, the plan may include class 4 photobiomodulation, class 3B cold laser, or whole-body infrared alongside metabolic and nutrition care. Orthobiologic injections (PRP and BMAC) are offered here. No success rate is published for any of it.

    When nutrition is the main cause, the goal comes in three steps, in this order. Find the specific pattern. Avoid a supplement that makes things worse. Then support the conditions for repair.

    Where we are and how to start

    Regenerve is located at 4477 Woodson Rd #104, St. Louis, MO 63134, minutes from St. Louis Lambert International Airport, and we see patients from across the St. Louis region, Missouri and Illinois. You can call (314) 886-5739 or text (314) 886-5902, or email info@regenerve.com.

    The free Nerve Damage Score is a five-question starting point. It will not diagnose a vitamin problem. But it sorts out the cause question, so the first visit can go somewhere useful.

    If B12 is still on your list, read how a stomach that stops absorbing B12 causes burning feet. For a nerve-support nutrient with its own trial record, see alpha-lipoic acid for peripheral neuropathy.

    Frequently asked questions

    Which nutritional deficiencies besides B12 can damage peripheral nerves?

    Thiamine (vitamin B1) is the clearest one. A 2026 review in Current Nutrition Reports describes how a thiamine shortage causes beriberi and Wernicke’s encephalopathy. It lists thiamine and B12 deficiencies as established risk factors for neuropathy.1 Vitamin B6 is the opposite problem, because too much, not too little, is what correlates with nerve injury. See why a “normal” B12 result can still be misleading.

    Can too much vitamin B6 really cause neuropathy?

    That is what the review reports. Too much pyridoxine, not too little, correlates with nerve effects. The B6 link overall remains uncertain, but extra B6 poses a risk of nerve poisoning.1 It is worth reviewing every supplement you take before adding another one. See the drivers that are most often missed.

    Can gluten sensitivity affect nerves even if my celiac test was negative?

    A negative celiac test rules out celiac disease, but not every gluten-related process. Immune and absorption pathways can overlap. We look at the whole picture instead of stopping at one result. See what a negative celiac test does and does not settle.

    Do statins, metformin, or weight-loss surgery matter here?

    The Current Nutrition Reports review notes that alcohol use, weight-loss surgery, and metformin use are increasingly driving B-vitamin shortages in higher-income countries.1 That is a reason to review medicine and surgery history, not a reason to stop a prescribed medicine on your own. See how statins and metformin intersect with nerve health.

    Why do my feet still burn when my labs look normal?

    One normal value does not settle the nutrition question, and mixed causes are common. A nutrient gap can sit alongside a metabolic, autoimmune, or toxic cause. Burning at night in particular often reflects small-fiber damage, which standard nerve conduction studies do not measure. See small fiber neuropathy symptoms and testing.

    What are you lacking if you have neuropathy?

    It may be thiamine (vitamin B1) or B12, since shortages of both are established risk factors for neuropathy. With vitamin B6, the problem can run the other way: too much, not too little, is what correlates with nerve injury. Nutrition also rarely acts alone. It usually sits beside blood sugar, autoimmune, toxic, or structural causes. So we name every active cause before anything is prescribed.

    What vitamin helps stop neuropathy?

    No single vitamin stops neuropathy, and adding supplements blindly can backfire. With vitamin B6, more is what causes the injury, so a high-dose B6 product can be part of the problem. When nutrition is the main cause, the plan is to find the specific pattern and avoid any supplement that makes things worse. Then we support the conditions in which nerve function can improve.

    What are the most common causes of neuropathy?

    A 2026 review in Neurological Research and Practice names B-vitamin deficiencies, prediabetes, diabetes, obesity, and treatment-induced neuropathies as key risk factors. It notes that polyneuropathy is becoming more common, especially in older people.2 These causes often overlap, so more than one is usually at work at the same time. Naming only the loudest one leaves the rest in place.

    Can nerve damage from a vitamin deficiency be reversed?

    We do not promise nerve regeneration, reversal, or a cure, and no success rate is published for any treatment we offer. What we can do is find the cause that is still injuring the nerve, such as a thiamine shortage or too much B6 from a supplement. Then we correct it and support the conditions in which function can improve. Stopping the ongoing damage comes first.

    Sources

    1. B Vitamin Deficiencies and Associated Neuropathies. Current Nutrition Reports. 2026. https://doi.org/10.1007/s13668-025-00723-3 (thiamine shortage producing beriberi and Wernicke’s encephalopathy; cobalamin deficiency impairing DNA synthesis and myelin formation; excess rather than inadequate pyridoxine correlating with neuropathic effects; alcohol abuse, weight-loss surgery, and metformin use increasingly driving these deficiencies in wealthier nations).
    2. Targeting risk factors and strategies for prevention of peripheral neuropathy: focus on B-vitamin deficiencies and metabolic diseases. Neurological Research and Practice. 2026. https://doi.org/10.1186/s42466-026-00466-8 (rising incidence of polyneuropathy, especially among older people; B-vitamin deficiencies, prediabetes, diabetes mellitus, obesity, and treatment-induced neuropathies as key risk factors).
  • Is Your Diet Destroying Your Nerves? The Gluten–Neuropathy Connection

    Is Your Diet Destroying Your Nerves? The Gluten–Neuropathy Connection

    Gluten can injure the nervous system directly. It can cause peripheral neuropathy and balance problems even with no celiac disease at all, and in people whose intestines seem perfectly fine.

    Most people think of gluten as a gut issue, felt as bloating or diarrhea. But some of the most important effects of gluten sensitivity are in the nervous system. This article explains the immune process behind that. It covers why standard celiac testing so often misses it, and what the evidence says about cutting gluten out.

    Can gluten cause neuropathy without celiac disease?

    Celiac disease is an autoimmune reaction to gluten that damages the small intestine. But researchers have spent decades documenting a wider group of gluten-related disorders. The best known is Dr. Marios Hadjivassiliou and colleagues in Sheffield, UK. In these disorders the main target is not the gut but the nervous system. In many of these patients, a gut biopsy is normal or near-normal. Yet the nerve damage is real and keeps getting worse.

    This matters a great deal. A patient with gluten neuropathy may be told “your celiac test is negative, so gluten isn’t your problem” and keep eating the very trigger that is tearing down their nerves.

    How does gluten damage nerves?

    The main mechanism is molecular mimicry, a case of mistaken identity. When the immune system reacts to gluten, it makes antibodies. In some people, some of those antibodies also attack the body’s own tissue. That happens because a structure in nerve tissue looks enough like the gluten fragment to be mistaken for it.

    A key player is an enzyme family called transglutaminase. In celiac disease, the immune attack targets transglutaminase-2, which is concentrated in the gut. In gluten-related nerve disease, antibodies against transglutaminase-6 (TG6), a form found in the nervous system, have been identified as a marker of the nerve attack. Antibodies can also target the myelin that insulates nerves. The result is an immune attack on the nerves of the limbs (neuropathy). In some patients it also hits the cerebellum, causing gluten ataxia, a loss of coordination and balance.

    What are the symptoms of gluten neuropathy?

    Gluten neuropathy most often shows up as a sensory neuropathy that hits the longest nerves first: tingling, numbness, and burning that begin in the feet. It develops slowly and can happen without gut symptoms. So it is often mislabeled as idiopathic. When the cerebellum is involved, patients may notice unsteadiness, a wide-based walk, or clumsiness that they blame on aging. An unexplained sensory neuropathy plus subtle balance problems should raise the question of gluten sensitivity.

    Why doesn’t a celiac test catch gluten neuropathy?

    Standard celiac screening looks for the gut form of the disease. It usually checks tissue transglutaminase-2 (tTG) antibodies and signs of gut damage. It is not built to detect the nerve form. A patient can have a fully negative celiac panel and still be making the TG6 and anti-myelin antibodies that drive nerve injury. That is why a negative celiac test does not rule out gluten as a cause of neuropathy. The companion article on negative celiac testing explores this further.

    Genetic testing (for the HLA-DQ2/DQ8 types that make people prone to gluten sensitivity) and wider antibody panels give a fuller picture than a routine celiac screen alone.

    Can a gluten-free diet reverse gluten neuropathy?

    The damage is driven by an ongoing immune response to gluten. So the logical, evidence-supported step is strict, sustained gluten elimination. Hadjivassiliou’s group has reported that patients who stick rigidly to a gluten-free diet can see their nerve symptoms hold steady and, in some cases, improve. Partial or on-and-off avoidance is often not enough. Nerve tissue recovers slowly, so any improvement takes months. The earlier the trigger is removed, the more function there is to save.

    “Strict” is the key word. This is not a lifestyle choice. Cutting gluten to treat nerve disease means removing cross-contamination and hidden sources, not just eating less bread. It is best done with diet guidance and monitoring.

    Where this fits in a root-cause evaluation

    Gluten is one of several causes that can pass for idiopathic neuropathy. A thorough workup checks it alongside metabolic, toxic, and mechanical causes, because more than one can be present at once. The value of finding a gluten link is that, in principle, it can be removed completely. The trigger is on the plate.

    Frequently asked questions

    Can I have gluten neuropathy if my celiac test is negative?

    Yes. Standard celiac tests detect the gut form of gluten disease, not the nerve form. TG6 and anti-myelin antibodies can be present with a negative celiac panel.

    Do I need digestive symptoms to have gluten neuropathy?

    No. Many patients with gluten-related nerve damage have no major gut symptoms at all.

    Will going gluten-free fix my neuropathy?

    It can help symptoms hold steady and sometimes improve, when done strictly and early. But nerve recovery is slow and varies by person. It works best as part of a physician-guided plan.

    How strict do I need to be?

    For gluten-related nerve disease, strict elimination appears necessary, including hidden and cross-contaminating sources. Avoiding it now and then is generally not enough.

    What are the neurological symptoms of gluten intolerance?

    The most common is a sensory neuropathy that starts in the feet: tingling, numbness, and burning. When the immune attack reaches the cerebellum, the balance center of the brain, it causes gluten ataxia. That means unsteadiness, a wide-based walk, or clumsiness that people often blame on getting older. An unexplained neuropathy plus subtle balance trouble should raise the question of gluten.

    How do you test for gluten neuropathy?

    Go beyond the routine celiac screen, which looks for the gut form of the disease. The nerve form is marked by antibodies against transglutaminase-6 (TG6) and against myelin. These can be present with a negative celiac panel. Genetic testing for the HLA-DQ2 and DQ8 types that make people prone to gluten sensitivity, plus a wider antibody panel, gives a fuller picture.

    How long does gluten neuropathy take to heal?

    Think in months, not weeks. Once gluten is strictly removed, nerve tissue recovers slowly. So holding steady or improving, when it comes, takes months. Partial or on-and-off avoidance is often not enough to get there. The earlier the trigger comes off the plate, the more nerve function there is to save.

    Key takeaways

    • Gluten can injure nerves and the cerebellum directly, apart from celiac disease.
    • The mechanism is immune molecular mimicry. Transglutaminase-6 antibodies mark the nerve attack.
    • Standard celiac tests do not detect the nerve form. A negative result does not clear gluten.
    • Strict, sustained gluten elimination is the evidence-supported step. Slow, partial recovery is possible.
    • Gluten is checked alongside other neuropathy causes, and in principle it can be removed completely.

    This article is educational and is not a substitute for evaluation, diagnosis, or treatment by a physician. Individual results vary. Do not make major dietary or medication changes without consulting your physician. Take the free Nerve Damage Score or call (314) 886-5739 or text (314) 886-5902.

    References

    1. Hadjivassiliou M, Grünewald RA, Davies-Jones GAB. Gluten sensitivity as a neurological illness. J Neurol Neurosurg Psychiatry. 2002;72:560–563.
    2. Hadjivassiliou M, et al. Transglutaminase-6 antibodies in the diagnosis of gluten ataxia. Neurology. 2013;80:1740–1745.
    3. Hadjivassiliou M, et al. Gluten neuropathy. Muscle Nerve / Brain (peripheral neuropathy series).
    4. Hadjivassiliou M, et al. Neurologic deficits in patients with gluten sensitivity — role of strict gluten-free diet.

    Find out what is driving your nerve pain

    The free, five-question Nerve Damage Score takes about two minutes and tells you which terrain failure is most likely behind your symptoms.

    Get My Free Nerve Damage Score Get Info

    Or call or text us.

  • Your “Normal” B12 May Be Lying: The Hidden Deficiency Driving Your Neuropathy

    Your “Normal” B12 May Be Lying: The Hidden Deficiency Driving Your Neuropathy

    Functional B12 deficiency means a serum B12 test can read “normal” while your nerves run short and neuropathy develops. That happens because much of the measured B12 is bound to a protein that cannot deliver it to tissues. Methylmalonic acid (MMA) and homocysteine expose the true shortage inside the cells. So it gets corrected before nerve or spinal-cord damage becomes permanent.

    One of the most treatable causes of peripheral neuropathy is also one of the most often missed. That is not because doctors don’t test for it. It is because the usual test can read “normal” while the shortage does real damage inside the cells. This article explains why a serum B12 result can mislead. It covers which functional markers show what it hides. And it lists the full set of nutrients your nerves need to work and to heal.

    Can you have B12 deficiency with normal B12 levels?

    The standard test measures the total amount of vitamin B12 in your blood. The problem is that this number does not always reflect how much B12 is actually available and working inside your cells. A large share of measured B12 is bound to a protein that cannot deliver it to tissues. So the total can look adequate while the usable supply is low. Normal ranges also vary from lab to lab. Results in the low-normal zone are often reported as fine, even when a patient has symptoms.

    The result is a patient with the classic tingling, numbness, and poor balance of a B12-related neuropathy being told their levels are “normal,” while the shortage quietly gets worse. Untreated, B12 deficiency can damage not only the nerves in the limbs but the spinal cord itself. Early damage is reversible, but advanced damage may not be.

    What tests show B12 deficiency when serum B12 is normal?

    To see what serum B12 hides, clinicians use functional markers. These are substances that build up when B12 is too low inside the cells, no matter what the total blood level says.

    Methylmalonic acid (MMA). B12 is a required helper for the enzyme that processes methylmalonyl-CoA. When cells are short on usable B12, this reaction stalls and MMA builds up. A high MMA is a sensitive and fairly specific sign of true B12 deficiency in the tissues.

    Homocysteine. B12 (along with folate and B6) is needed to turn homocysteine into methionine. When usable B12 is low, homocysteine rises. High homocysteine is less specific than MMA, because it can also reflect low folate or B6. But together the two markers give a far more accurate picture than serum B12 alone.

    Checking MMA and homocysteine can catch a functional shortage that a normal B12 would have hidden. That allows correction before permanent nerve or spinal-cord injury happens.

    What depletes vitamin B12?

    Functional B12 deficiency is especially worth checking in several situations. Metformin, one of the most-prescribed diabetes drugs, interferes with B12 absorption and can cause a shortage over years of use. That is a cruel irony in patients whose diabetes already threatens their nerves. Acid-suppressing drugs (PPIs and H2 blockers) reduce the stomach acid needed to free B12 from food. Age reduces absorption. So can autoimmune (pernicious) causes, stomach or bowel surgery, and strict plant-based diets. Anyone with unexplained neuropathy and any of these risk factors deserves functional testing.

    What other nutrient deficiencies affect the nerves?

    B12 gets the headlines, but nerves depend on a whole team of helper nutrients. A shortage of any one can impair function or healing.

    Thiamine (B1). Thiamine is essential for burning glucose and for energy production in the mitochondria (the cell’s power plants). A thiamine shortage directly causes neuropathy. It often runs low in diabetes and in heavy alcohol use. The work of Dr. Hammes and colleagues pointed to how thiamine-dependent pathways protect against the chemical damage of high blood sugar. That is part of the reason for benfotiamine, a form of thiamine.

    Vitamin B6. B6 is needed for nerve function and for making nerve messengers. But there is an important catch: both too little and too much can cause neuropathy. So B6 supplements should be measured and monitored, not open-ended.

    Magnesium. Magnesium helps run hundreds of enzyme reactions, including those that control nerve firing and mitochondrial energy. A shortage adds to nerve overexcitability and is common in diabetes.

    Omega-3 fatty acids. These are building blocks of nerve membranes, and they calm inflammation. Getting enough supports the membrane strength and the inflammatory balance that healthy nerves need.

    The mitochondrial common thread

    Notice the common thread. Nearly every one of these nutrients feeds into mitochondrial energy production. A nerve uses a lot of energy, and it fails when its power supply falters. This is why fixing shortages is not simply “topping up vitamins” and nothing more. It is restoring the cell’s ability to make energy, repair itself, and keep its signals working. Functional nutrient testing, and correction guided by that testing, is a core part of a root-cause neuropathy plan, not an afterthought.

    How is functional B12 deficiency treated?

    The practical message is to test properly and correct precisely. That means functional markers (MMA, homocysteine), not serum B12 alone. It means checking thiamine and magnesium levels. It means reviewing medicines that drain these nutrients, without stopping needed prescriptions on your own. And it means refilling what the testing shows is low. Some nutrients (like B6) can harm in excess, and absorption problems may require specific forms or routes. That is why this is best done under medical guidance.

    Frequently asked questions

    My B12 came back normal — could it still be my problem?

    Yes. Total serum B12 can read normal while the active supply inside the cells is low. MMA and homocysteine testing can reveal a functional shortage the standard test misses.

    Does metformin cause B12 deficiency?

    It can, over time, by impairing absorption. If you take metformin and have neuropathy symptoms, functional B12 testing makes sense. But do not stop metformin on your own.

    There is more on this in The Cruel Irony: How Statins and Metformin Can Affect Nerve Health.

    Can I just take high-dose B vitamins to be safe?

    Not blindly. B6 in particular can cause neuropathy in excess. Good correction depends on which nutrient is actually low and how well you absorb it. Test, then treat.

    For how too much B6 can itself damage nerves, read Vitamin B6 toxicity as a cause of peripheral neuropathy.

    How quickly does nerve function recover after correction?

    Early damage from a shortage often improves once it is corrected. But recovery is slow, and advanced damage may not fully recover. Earlier detection means better outcomes.

    There is more on this in Can Peripheral Neuropathy Improve? What Is Realistic and What Is Not.

    What are the first signs of B12 deficiency in the nerves?

    The classic signs are tingling, numbness, and poor balance. Many people with these symptoms are told their B12 is normal, because the standard blood test counts B12 their cells cannot use. Left alone, the shortage can damage both the nerves in the limbs and the spinal cord. Early damage is reversible, which is why checking MMA and homocysteine early matters.

    Who is most likely to have a B12 deficiency?

    People who take metformin are at risk. So are people on acid-suppressing drugs such as PPIs and H2 blockers, and older adults, whose absorption falls with age. Autoimmune (pernicious) causes, past stomach or bowel surgery, and strict plant-based diets also raise the risk. Anyone with unexplained neuropathy and one of these risk factors should get functional B12 testing, not just a serum level.

    Why would I suddenly have a B12 deficiency?

    It rarely starts suddenly, even when the symptoms seem to. Metformin can drain B12 slowly over years of use. Acid-suppressing drugs reduce the stomach acid needed to free B12 from food. Aging, autoimmune disease, gut surgery, and a strict plant-based diet all cut the supply further. The shortage builds quietly until the nerves start to complain.

    Key takeaways

    • A “normal” serum B12 can hide a cellular deficiency that damages nerves and even the spinal cord.
    • Functional markers, methylmalonic acid and homocysteine, reveal a true shortage in the tissues.
    • Metformin, acid-suppressing drugs, age, and gut problems are common causes worth screening for.
    • Nerves also depend on thiamine, B6 (in balance), magnesium, and omega-3s, mostly through mitochondrial energy.
    • Test functionally and correct precisely, under guidance. Don’t self-dose blindly.

    This article is educational and is not a substitute for evaluation, diagnosis, or treatment by a physician. Individual results vary. Do not start, stop, or change any medication or supplement without consulting your physician. Take the free Nerve Damage Score or call (314) 886-5739 or text (314) 886-5902.

    References

    1. Stabler SP. Vitamin B12 deficiency. N Engl J Med. 2013;368:149–160.
    2. Aroda VR, et al. Long-term metformin use and vitamin B12 deficiency (Diabetes Prevention Program Outcomes Study). J Clin Endocrinol Metab. 2016.
    3. Hammes HP, et al. Benfotiamine blocks three major pathways of hyperglycemic damage. Nat Med. 2003;9:294–299.
    4. Ghavanini AA, Kimpinski K. Revisiting the evidence for neuropathy caused by pyridoxine (B6) deficiency and excess. J Clin Neuromuscul Dis. 2014.

    Find out what is driving your nerve pain

    The free, five-question Nerve Damage Score takes about two minutes and tells you which terrain failure is most likely behind your symptoms.

    Get My Free Nerve Damage Score Get Info

    Or call or text us.

  • Negative Celiac Test but Burning Feet? The Gluten–Neuropathy Link Doctors Miss

    Negative Celiac Test but Burning Feet? The Gluten–Neuropathy Link Doctors Miss

    Yes, gluten can injure your nerves even when the celiac test is negative. Celiac screening looks for tTG-2 antibodies, which mark an attack on the gut. Gluten neuropathy targets the nerves instead. TG6 antibodies plus HLA-DQ2/DQ8 typing show what the standard panel misses.

    You did the responsible thing. You mentioned your burning feet. Someone ordered a celiac panel, it came back negative, and gluten was crossed off the list. But for a large number of people with gluten-related nerve damage, that negative result is exactly where the diagnosis goes wrong. The celiac test answers a different question than the one your nerves are asking. This article explains why standard celiac screening misses gluten neuropathy, and what testing actually finds it.

    Why does a celiac test miss gluten neuropathy?

    Celiac disease is defined by an immune attack on the small intestine. Its screening tools are built to detect that. Mainly they look for antibodies to tissue transglutaminase-2 (tTG-2), the form of the enzyme concentrated in the gut. A gut biopsy showing damage to the villi confirms it.

    Gluten-related neurological disease is a different form of gluten sensitivity. The immune response targets the nervous system, and the gut may be fully spared. So a patient can have a spotless celiac panel and a normal gut biopsy while making the antibodies that injure their nerves. The test isn’t broken. It is simply looking in the wrong place.

    What does gluten attack in the nerves?

    As covered in the companion article on the gluten–neuropathy link, the mechanism is molecular mimicry, a case of mistaken identity. Two targets matter most for a nerve-focused workup.

    Transglutaminase-6 (TG6). This form of the enzyme is found in nerve tissue. Antibodies against it, described by Dr. Marios Hadjivassiliou’s group, mark the nerve form of gluten sensitivity. TG6 antibodies can be present when the gut-focused tTG-2 antibodies are absent. That is exactly why a celiac screen can miss nerve disease.

    Anti-myelin and related antibodies. The immune response can also target parts of the myelin sheath that insulates nerves. That adds to the sensory neuropathy. When the cerebellum is involved, it adds to the ataxia (loss of balance and coordination) seen in gluten-related nerve disease.

    What does an HLA-DQ2 or HLA-DQ8 gene test tell you?

    Gluten sensitivity has strong genetic roots. The great majority of people who react to gluten, in either the celiac or the nerve form, carry one of two immune-system genetic markers: HLA-DQ2 or HLA-DQ8. Testing for these types tells you something different from antibody testing. A negative HLA-DQ2/DQ8 result makes gluten-driven disease very unlikely and can in effect rule it out. A positive result shows you are prone to it, though not everyone who is prone develops disease. That makes HLA typing a useful gatekeeper test in a workup for unexplained neuropathy.

    How is gluten neuropathy tested?

    Take someone with an unexplained sensory neuropathy, especially with any balance trouble. A fuller workup than a routine celiac screen includes HLA-DQ2/DQ8 genetic typing. It includes a wider gluten-related antibody panel (with TG6 where available, alongside the usual celiac antibodies). And it includes an exam for the sensory pattern that hits the longest nerves first, and for any signs from the cerebellum. The aim is to catch the nerve form that the standard screen is not built to see.

    An important practical catch: antibody testing means the most while gluten is still in the diet. If a patient has already gone gluten-free, antibody levels may fall and give falsely reassuring results. Plan around this with a clinician before testing.

    Can gluten neuropathy improve on a gluten-free diet?

    Tracking down a gluten link is worth it because, unlike many neuropathy causes, it can be fully removed. The trigger is in the diet. When gluten-related nerve disease is confirmed and strict elimination starts early, symptoms can hold steady and sometimes improve. The tragedy of the missed diagnosis is that the person keeps eating the trigger for years. They blame their worsening nerve damage on bad luck or aging, when a change on the plate could have changed the course.

    This is one driver among several

    Gluten sensitivity is one possible cause checked within a broader root-cause search that also weighs metabolic, toxic, and mechanical causes. Several causes often exist together. So ruling gluten in or out is part of building the full picture, not a hunt for a single culprit.

    Frequently asked questions

    My celiac test was negative — can gluten still be damaging my nerves?

    Yes. Celiac screening detects the gut form of gluten disease. The nerve form can happen with a negative celiac panel and a normal gut biopsy, driven by antibodies like TG6.

    What should I ask to be tested for instead?

    Consider HLA-DQ2/DQ8 genetic typing and a wider gluten-related antibody panel, including transglutaminase-6 where available. Ideally do this while still eating gluten.

    If I already went gluten-free, will testing still work?

    Antibody levels can fall after gluten is removed, which may make results falsely negative. Discuss timing with your physician before testing.

    Does a positive HLA-DQ2/DQ8 mean I definitely have gluten neuropathy?

    No. It shows you are prone to it, not that you have the disease. It is most useful the other way around: a negative result makes gluten-driven disease very unlikely.

    What does gluten neuropathy feel like?

    It usually starts as a sensory neuropathy. The feet burn in a length-dependent pattern, meaning the longest nerves go first. When the immune attack reaches the cerebellum, balance suffers too, and walking can feel unsteady. Burning feet plus poor balance, with a negative celiac panel, is the pattern worth a closer look.

    Who should be tested for gluten neuropathy?

    Anyone with an unexplained sensory neuropathy, especially if balance is also off. A routine celiac screen is not enough for this group. The fuller workup adds HLA-DQ2/DQ8 genetic typing and a wider antibody panel that includes TG6 where available. It also adds an exam for the length-dependent sensory pattern and signs from the cerebellum. All of it is done while gluten is still in the diet.

    Could gluten be the only cause of my neuropathy?

    Sometimes, but often it is one cause among several. Metabolic, toxic, and mechanical causes often sit alongside it. So ruling gluten in or out is one piece of a root-cause workup, not a hunt for a single culprit. What makes gluten worth finding is that it can be removed: the trigger is on your plate.

    Key takeaways

    • Standard celiac tests detect gut disease, not the nerve form of gluten sensitivity.
    • Transglutaminase-6 (TG6) antibodies mark the nerve attack. They can be present with a negative celiac panel.
    • HLA-DQ2/DQ8 typing is a useful gatekeeper. A negative result largely rules gluten out.
    • Test while still eating gluten, since cutting it first can make antibody results falsely negative.
    • Confirmed gluten neuropathy is uniquely treatable, because the trigger is removable.

    This article is educational and is not a substitute for evaluation, diagnosis, or treatment by a physician. Individual results vary. Do not make major dietary or medication changes without consulting your physician. Take the free Nerve Damage Score or call (314) 886-5739 or text (314) 886-5902.

    References

    1. Hadjivassiliou M, et al. Transglutaminase-6 antibodies in the diagnosis of gluten ataxia. Neurology. 2013;80:1740–1745.
    2. Hadjivassiliou M, Sanders DS, Grünewald RA, et al. Gluten sensitivity: from gut to brain. Lancet Neurol. 2010;9:318–330.
    3. Hadjivassiliou M, et al. Gluten-related neurological dysfunction and HLA associations.
    4. Volta U, et al. Serological tests in gluten-related disorders. Cell Mol Immunol / review.

    Find out what is driving your nerve pain

    The free, five-question Nerve Damage Score takes about two minutes and tells you which terrain failure is most likely behind your symptoms.

    Get My Free Nerve Damage Score Get Info

    Or call or text us.

  • Neuropathy After Weight-Loss or Gallbladder Surgery? The Deficiency No One Checks

    Neuropathy After Weight-Loss or Gallbladder Surgery? The Deficiency No One Checks

    Weight-loss surgery drains B12, thiamine and copper. Gallbladder removal cuts the fat absorption that vitamin E depends on. Each of those shortages damages nerves. Copper is the one almost no one checks, which is why lifelong nutrient monitoring after surgery is the answer.

    Some neuropathies trace back to an event years earlier. An operation fixed one problem and quietly set up another. Some surgeries change the gut. They include bariatric (weight-loss) surgery and gallbladder removal. These can impair the uptake of nutrients the nerves need. The nerve damage may show up months or years later. By then, no one is thinking about the surgery. That is exactly why the shortage so often goes unchecked. This article explains how it happens, which nutrients are at risk, and why lifelong monitoring is the answer.

    How does weight-loss or gallbladder surgery cause neuropathy?

    Absorbing nutrients is a carefully timed process. It depends on certain parts of the gut and certain stomach juices. Fats and fat-soluble vitamins also need bile. Surgery that changes this setup can disrupt absorption, even when a person eats well.

    Bariatric surgery works partly by cutting how much you eat. Some types also skip past parts of the gut that absorb nutrients. Surgery also lowers stomach acid and intrinsic factor. You need both to absorb vitamin B12. The result is a well-documented, long-term risk of running low on several nutrients.

    Gallbladder removal (cholecystectomy) changes how bile reaches the gut. Bile is key for taking in fat from food. It is also key for the fat-soluble vitamins (A, D, E, and K). Because of that, some people absorb fat poorly afterward. Over time this can affect nutrients like vitamin E. Low vitamin E is tied directly to neurological (nerve and spinal cord) problems.

    The common thread is malabsorption: the food goes in, but the nutrients don’t fully get where they need to go.

    Which vitamin deficiencies cause neuropathy after surgery?

    Several shortages after gut surgery hit nerve health directly.

    Vitamin B12. At high risk after surgery that lowers stomach acid and intrinsic factor. B12 deficiency causes a typical pattern of nerve damage and can harm the spinal cord.

    Thiamine (B1). Can run low fast, especially with vomiting or poor eating after surgery. Low thiamine causes neuropathy. In the short term (acutely), it can also set off a neurological emergency called Wernicke’s encephalopathy. This is one to catch early.

    Copper. Often missed, but important. Low copper can follow bariatric surgery, and too much zinc makes it worse. It causes a myeloneuropathy. That harms both the peripheral nerves and the spinal cord. It can look like B12 deficiency. It is often missed because few clinicians think to check it.

    Fat-soluble vitamins (especially vitamin E). Poor fat absorption matters most after gallbladder changes and surgeries that reduce absorption (malabsorptive procedures). It can lead to low vitamin E. That causes its own neurological syndrome, with neuropathy and balance problems.

    Other B vitamins and minerals. Folate, B6, and others can also run low, adding to the problem.

    Why is neuropathy after surgery so often missed?

    The delay is the problem. Nutrient stores can take months or years to run down. So the nerve damage often shows up well after the surgery. By then, the patient and a new clinician may not link the two. Copper and vitamin E stand out. They are not on most routine panels, so they go unchecked unless someone thinks of them. A patient can end up labeled with idiopathic neuropathy (no known cause). Yet the real cause is a treatable shortage from surgery that simply wasn’t on anyone’s radar.

    How long do you need nutrient checks after bariatric surgery?

    The fix is simple on paper. It takes steady work in real life. Anyone who has had bariatric surgery needs lifelong nutritional monitoring. So do people with malabsorption after other gut surgery. The checks must cover the nutrients routine panels skip. That means regular checks of B12 (functionally, with MMA and homocysteine) and thiamine. It also means checks of copper and the fat-soluble vitamins including vitamin E. Folate and others are checked as needed. Refilling the stores (repletion) is matched to what the tests show.

    Repletion sometimes needs special forms or routes, such as higher-dose or non-oral B12. Here is why. The absorption problem that caused the shortage also affects how supplements are absorbed. So care after surgery is an ongoing medical partnership, not a one-time fix. When nerve damage does appear, checking this full panel can find a cause that is truly fixable.

    Where this fits

    Post-surgical malabsorption is one of the nutrition and metabolic drivers we check in a full neuropathy workup. Its signature is nerve damage with no clear cause plus a history of gut surgery. Tell any clinician checking your nerve symptoms about that history. It points straight at specific shortages that can be tested.

    Frequently asked questions

    I had weight-loss surgery years ago — could that be causing my neuropathy now?

    Yes. Shortages can take months to years to cause symptoms. So nerve damage that shows up well after surgery fits with malabsorption. A targeted nutrient panel can sort it out.

    For which nutrients a post-surgical panel should cover, read Nutritional deficiencies beyond B12 that damage peripheral nerves.

    Which deficiencies get missed the most?

    Copper and vitamin E are often missed because they aren’t on standard panels. Yet both cause neurological damage. B12 and thiamine also need checking.

    For why a normal B12 result can still hide a deficiency, read Your “Normal” B12 May Be Lying: The Hidden Deficiency Driving Your Neuropathy.

    I take a multivitamin — isn’t that enough?

    Not always. Malabsorption can outrun a standard multivitamin. Some nutrients need special forms or doses. Testing shows whether your plan is actually keeping levels where they should be.

    Does gallbladder removal cause neuropathy?

    It can add to the problem in some people. Over time, it can make it harder to absorb fat and the vitamins that need fat. So low vitamin E is worth checking when nerve damage appears.

    What are the symptoms of neuropathy after bariatric surgery?

    They depend on which nutrient is missing. B12 deficiency causes a typical pattern of nerve damage and can harm the spinal cord. Low copper harms the peripheral nerves and the spinal cord. It can look like B12 deficiency. Low vitamin E causes neuropathy with balance problems. Low thiamine causes neuropathy. In the short term (acutely), it can also cause a neurological emergency called Wernicke’s encephalopathy.

    Can vomiting after surgery cause nerve damage?

    It can. Thiamine (vitamin B1) can run low fast after surgery. This is most likely with vomiting or poor eating. Low thiamine causes nerve damage. It can also set off Wernicke’s encephalopathy, a neurological (brain) emergency. Are you vomiting or barely eating after weight-loss surgery? Then thiamine is the shortage to catch early. Tell your surgical team right away.

    Why don’t regular B12 pills always work after gastric bypass?

    The same absorption problem that caused the shortage also limits how well supplements get in. Bariatric surgery lowers stomach acid and intrinsic factor. You need both to absorb B12. That is why repletion sometimes needs higher-dose or non-oral B12. It is also why follow-up tests with MMA and homocysteine are used. They confirm the plan is actually working.

    Can too much zinc cause neuropathy?

    Indirectly, yes. Too much zinc makes low copper worse. Low copper causes a myeloneuropathy that harms both the peripheral nerves and the spinal cord. After bariatric surgery, copper is already at risk, so that combination matters. Copper is not on most routine panels. Ask for it by name if you get nerve damage after surgery.

    Key takeaways

    • Bariatric and gallbladder surgery can impair nutrient uptake and cause neuropathy that shows up later.
    • Key nutrients at risk: B12, thiamine, copper, and fat-soluble vitamins (especially vitamin E).
    • Low copper and low vitamin E are often missed because they aren’t on routine panels.
    • The delay between surgery and symptoms is why the cause is so often missed.
    • Lifelong testing and matched refilling can prevent and reverse these shortages.

    This article is educational and is not a substitute for evaluation, diagnosis, or treatment by a physician. Individual results vary. Do not start, stop, or change supplements or medication without consulting your physician. Take the free Nerve Damage Score or call (314) 886-5739 or text (314) 886-5902.

    References

    1. Kumar N. Neurologic complications of bariatric surgery. Continuum (Minneap Minn). 2014.
    2. Jaiser SR, Winston GP. Copper deficiency myelopathy and neuropathy. J Neurol. 2010;257:869–881.
    3. Becker DA, et al. Neurological complications of nutritional deficiency following bariatric surgery. J Obes. 2012.
    4. Kumar N. Nutritional neuropathies (vitamin E, B12, thiamine, copper). Neurol Clin. 2007.

    Find out what is driving your nerve pain

    The free, five-question Nerve Damage Score takes about two minutes and tells you which terrain failure is most likely behind your symptoms.

    Get My Free Nerve Damage Score Get Info

    Or call or text us.